- Home
- Diabetes Information for Patients Types Symptoms Tests and Treatment
- What Is Diabetes Mellitus Symptoms Causes Diagnosis and Treatment
Diabetes Mellitus Explained: Types, Symptoms, Causes, Diagnosis, and Treatment
Diabetes mellitus is a group of conditions that affect how your body uses glucose, the main source of energy for your cells. This guide explains the different types of diabetes, common symptoms, causes, diagnosis, treatment options, and practical steps to help manage blood sugar and reduce the risk of complications.
If you live with diabetes, it is understandable to want a simple answer to the question, “What blood sugar should I aim for?”
For many adults, there are well-established treatment targets. However, I always remind my patients that these are general goals, not one-size-fits-all rules. Your safest target depends on your age, type and duration of diabetes, medicines, risk of hypoglycemia, pregnancy status, kidney or heart disease, and overall health.
The goal is not to keep glucose at one perfect number all day. It is to remain within a safe range as consistently as possible while avoiding prolonged high blood sugar and unnecessary low blood sugar.
Quick Answer: Common Blood Glucose Targets
For many nonpregnant adults with diabetes, commonly used treatment goals are:
- Before meals: 80–130 mg/dL (4.4–7.2 mmol/L)
- Peak after meals: below 180 mg/dL (below 10.0 mmol/L), measured 1–2 hours after the beginning of the meal
- A1C: below 7% (below 53 mmol/mol), when this can be achieved safely
| Measurement | Common target | What it means |
|---|---|---|
| Before meals | 80–130 mg/dL (4.4–7.2 mmol/L) |
A common premeal target for many nonpregnant adults |
| Peak after meals | Below 180 mg/dL (below 10.0 mmol/L) |
Usually assessed 1–2 hours after the beginning of the meal |
| A1C | Below 7% (below 53 mmol/mol) |
A common longer-term goal when it can be reached safely |
What Does “Acceptable Blood Glucose” Mean?
An acceptable blood glucose level is not necessarily the same as a “normal” glucose level in someone without diabetes.
When we set a diabetes target, we balance two priorities: keeping glucose low enough to reduce the risk of long-term complications while avoiding hypoglycemia and treatment that is too aggressive for the individual patient.
A single blood glucose reading does not provide a complete picture of diabetes control. In clinical practice, I consider the broader pattern, including fasting and premeal glucose levels, post-meal readings when appropriate, A1C, episodes of hypoglycemia, symptoms, current medications, and, when available, continuous glucose monitoring (CGM) data. These measures should also be interpreted in the context of established blood glucose and A1C ranges for normal glucose, prediabetes, and diabetes.
Acceptable Blood Glucose Before Meals
For many nonpregnant adults with diabetes, a common target before meals is 80–130 mg/dL (4.4–7.2 mmol/L).
This gives us useful information about your baseline glucose before food begins to raise it. If most of your premeal readings are within your agreed target, that is encouraging, but they should still be interpreted together with your post-meal pattern, A1C, low-glucose episodes and overall treatment plan.
A reading of 80 mg/dL is not hypoglycemia. It is near the lower end of the usual premeal target. Hypoglycemia is generally defined as glucose below 70 mg/dL.
If fasting or premeal readings are repeatedly above your personal target, possible contributors include overnight glucose production, meal or medication timing, illness, poor sleep, stress and changes in physical activity. A pattern over several days is more informative than one isolated morning reading.
If morning glucose is your main concern, see our guide to fasting blood sugar levels.
Acceptable Blood Glucose After Meals
For many adults with diabetes, a common target is a peak post-meal glucose below 180 mg/dL (10.0 mmol/L).
When post-meal glucose is being assessed, it is generally measured 1–2 hours after the beginning of the meal. The timing matters because this period is intended to capture glucose near its post-meal peak.
One reading slightly above 180 mg/dL does not necessarily mean your treatment is failing. A larger meal, more carbohydrate than usual, illness, stress, poor sleep or reduced activity can all affect the result. More important questions are whether higher readings occur frequently, remain elevated for a long time, or appear alongside an A1C or CGM pattern showing excessive glucose exposure.
Because blood glucose changes throughout the day, the timing of a measurement matters, particularly when interpreting blood sugar levels after eating.
How Does A1C Fit With Daily Blood Sugar Targets?
Daily readings show what your blood sugar is doing at a particular moment. A1C provides a broader view of glucose exposure over the previous two to three months, with more recent weeks contributing more to the result.
For many nonpregnant adults with diabetes, a common A1C goal is below 7% (53 mmol/mol) when it can be achieved safely. Some people may benefit from a lower goal. Others need a less stringent goal because hypoglycemia, frailty, serious comorbidities, cognitive or functional limitations, or treatment burden makes tighter control less safe.
I would not interpret A1C in isolation. Two people can have the same A1C while experiencing very different patterns of highs and lows.
Learn more in A1C vs Blood Sugar, or use our HbA1c to Average Glucose Calculator.
What If I Use a Continuous Glucose Monitor?
A continuous glucose monitor, or CGM, helps us look beyond individual fingerstick readings. It shows how much time glucose spends within, above and below the target range.
| CGM metric | Common goal for many adults |
|---|---|
| Time in range: 70–180 mg/dL | More than 70% of the time |
| Time below 70 mg/dL | Less than 4% of the time |
| Time below 54 mg/dL | Less than 1% of the time |
| Time above 180 mg/dL | Less than 25% of the time |
CGM goals also need to be individualized. Some older adults with complex health problems, for example, may need more permissive goals to reduce the risk of hypoglycemia.
What About Bedtime Blood Sugar?
There is no single bedtime glucose target appropriate for every adult with diabetes. Bedtime goals depend on insulin use, risk of overnight hypoglycemia, age, other medical conditions, recent exercise, meal timing and the treatment plan you follow.
If you use insulin or medicines that can cause hypoglycemia, your clinician may give you a specific bedtime target. Follow that individualized plan rather than relying on a universal bedtime number from the internet.
What Is Considered Low Blood Sugar?
For people with diabetes, glucose below 70 mg/dL (3.9 mmol/L) is considered hypoglycemia and should be taken seriously. A level below 54 mg/dL (3.0 mmol/L) is more clinically significant.
Symptoms may include shakiness, sweating, hunger, palpitations, dizziness, weakness, irritability, confusion or difficulty concentrating. If you have a hypoglycemia treatment plan, follow it promptly. Frequent low readings require medical review because medication dose, meal timing or activity may need adjustment.
Why Your Personal Target May Be Different
I would not give exactly the same glucose goal to every patient. Your targets may need to be individualized if you:
- are pregnant or planning pregnancy;
- are a child or adolescent;
- are an older adult;
- have frequent or severe hypoglycemia;
- have impaired awareness of low blood sugar;
- have significant kidney, heart, liver or other medical disease;
- have cognitive or functional limitations;
- have lived with diabetes for many years; or
- use insulin or medicines that increase hypoglycemia risk.
An older adult who is otherwise healthy may still have relatively tight glucose goals. Someone with frailty, several serious illnesses or recurrent hypoglycemia may need more relaxed targets because preventing low blood sugar becomes the greater priority.

What Can Affect Your Blood Glucose Readings?
Even when your treatment plan has not changed, glucose can vary from day to day. Common influences include:
- meal size and carbohydrate content;
- physical activity;
- stress and sleep;
- infection, illness or pain;
- dehydration or alcohol;
- hormonal changes;
- medication timing;
- missed insulin or diabetes medicine; and
- corticosteroids and some other medicines.
This is why I encourage patients to look for patterns rather than reacting strongly to one unusual result.

How to Keep Blood Glucose Closer to Your Target
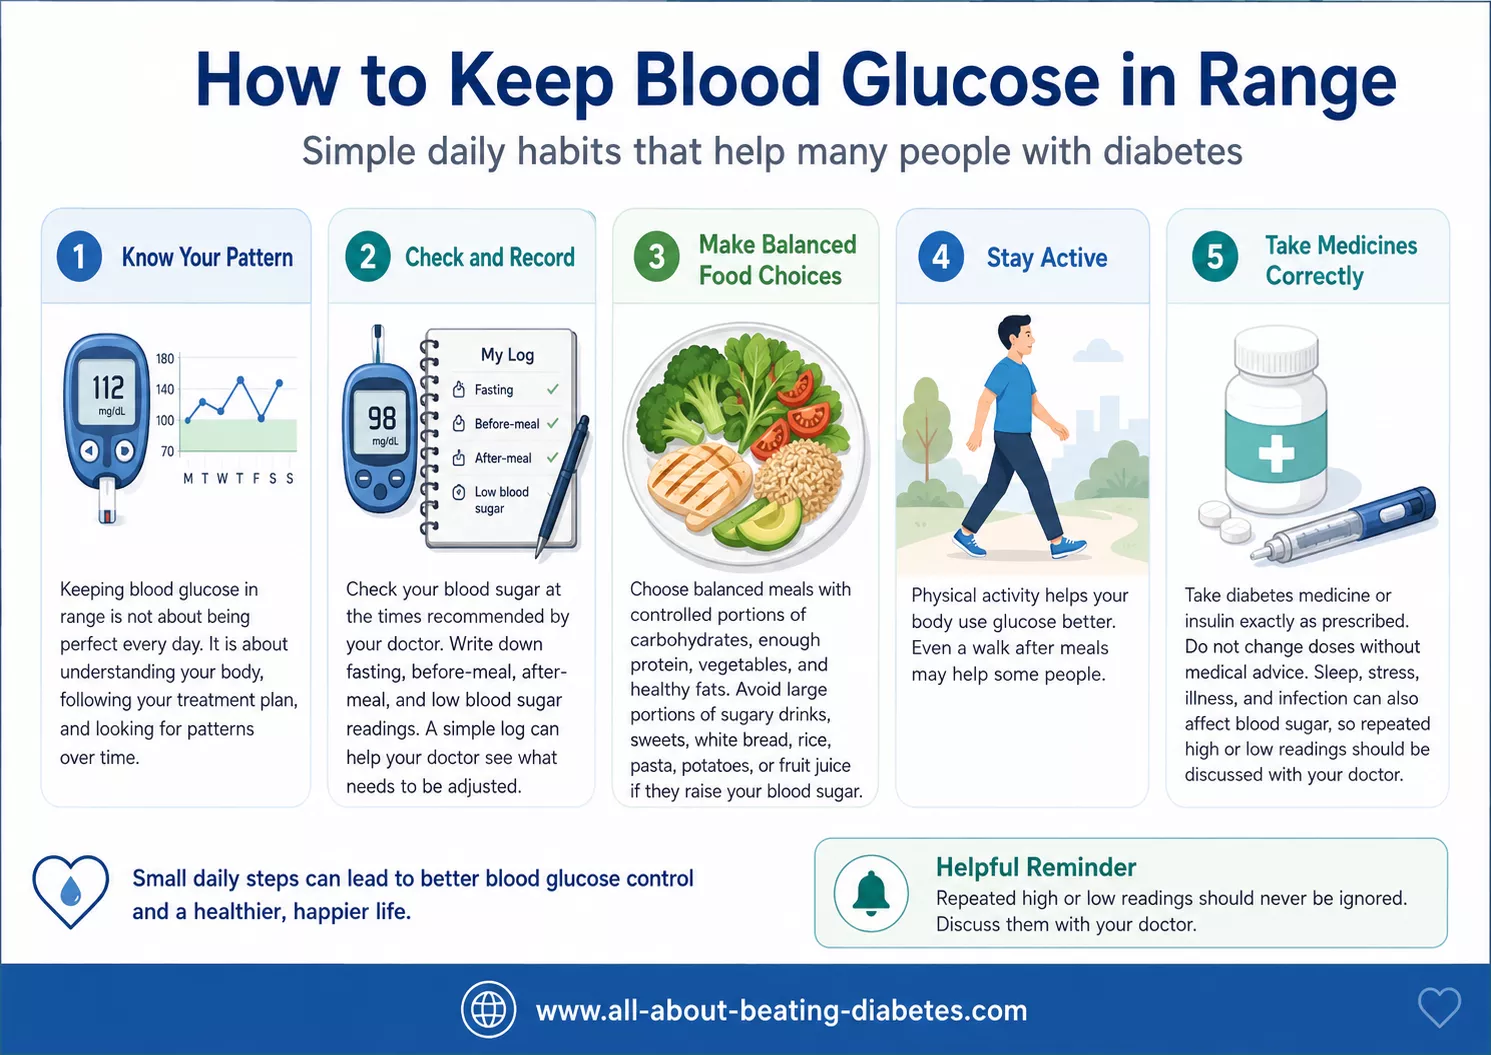
Keeping glucose in range does not require perfect numbers every day. The practical goal is to make the overall pattern safer and more consistent. Depending on your treatment plan, helpful steps may include:
- taking insulin or diabetes medicine exactly as prescribed;
- checking glucose at the times recommended by your healthcare team;
- keeping carbohydrate portions reasonably consistent when this is part of your plan;
- choosing meals with vegetables, protein, fiber and appropriate carbohydrate portions;
- being physically active regularly;
- reviewing repeated highs or lows instead of changing medication on your own;
- paying attention to sleep, illness, stress and hydration; and
- bringing your glucose log or CGM report to medical appointments.
Do not change insulin or medication doses because of one unusual result unless your healthcare professional has given you a specific adjustment plan.
Dr. Albana’s Perspective
When a patient asks whether a blood sugar number is “acceptable,” I first ask when it was measured and what target we agreed on for that person.
A premeal glucose of 125 mg/dL may be within the usual target for many adults with diabetes. The same number means something different if we are discussing a fasting laboratory test used to screen a person who has not been diagnosed with diabetes.
I also do not judge diabetes control from one good reading or one bad reading. I want to know whether most values are reasonably close to target, whether there are repeated highs, whether low glucose is occurring, and whether the A1C or CGM report tells the same story.
The best target is not the lowest number you can achieve. It is the range that offers meaningful long-term protection while remaining safe and realistic for your health and treatment.
When Should You Contact Your Doctor?
Contact your healthcare team if:
- glucose is repeatedly above your agreed target;
- you have repeated readings below 70 mg/dL;
- you experience nighttime hypoglycemia;
- your A1C is rising despite apparently reasonable daily readings;
- your CGM shows frequent highs or lows;
- you are ill and glucose becomes difficult to control;
- you are unsure whether medication or insulin needs adjustment; or
- your target may no longer be appropriate because of pregnancy, aging or a new medical condition.
Related Questions
Is 130 mg/dL acceptable for someone with diabetes?
It depends on when it was measured. For many nonpregnant adults, 130 mg/dL is at the upper end of the common premeal target. After a meal, it may also be within an acceptable range, but your individual target may differ.
Is 180 mg/dL after eating acceptable?
For many adults with diabetes, the common goal is a peak post-meal glucose below 180 mg/dL, assessed 1–2 hours after the beginning of the meal. Frequent readings at or above this level should be reviewed as a pattern.
Is 70 mg/dL acceptable?
Seventy mg/dL is the threshold at which we become concerned about hypoglycemia. A reading below 70 mg/dL should be treated according to your diabetes plan, and repeated lows should be discussed with your healthcare team.
Should everyone with diabetes have the same glucose target?
No. Age, pregnancy, medications, hypoglycemia risk, kidney or heart disease, functional status and other health conditions can all affect the safest goal.
What should my blood sugar be at bedtime?
There is no universal bedtime target for every adult with diabetes. Your bedtime goal should reflect your treatment plan, especially if you use insulin or are at risk of overnight hypoglycemia.
Is A1C below 7% right for everyone?
No. Below 7% is a common goal for many nonpregnant adults, but some people may benefit from a lower goal and others need a less stringent one for safety.
Related Tools and Calculators
Related Resources
Final Key Message
For many nonpregnant adults with diabetes, common treatment goals are 80–130 mg/dL before meals, below 180 mg/dL at the peak after meals, and A1C below 7% when these goals can be achieved safely.
If you use CGM, spending more than 70% of the time between 70 and 180 mg/dL is a common goal for many adults, while time below 70 mg/dL should remain limited.
Most importantly, your target should fit you. A safe plan balances glucose control with your risk of hypoglycemia, medications, age, other medical conditions and daily life. I would rather see a patient follow a realistic, individualized target safely and consistently than chase a “perfect” number that creates unnecessary risk.
References
- American Diabetes Association Professional Practice Committee. Glycemic Goals, Hypoglycemia, and Hyperglycemic Crises: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl. 1).
- American Diabetes Association Professional Practice Committee. Older Adults: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl. 1).
- American Diabetes Association. Checking Your Blood Sugar.
- National Institute of Diabetes and Digestive and Kidney Diseases. Managing Diabetes. National Institutes of Health.
Medical disclaimer: This information is for general education and does not replace professional medical advice, diagnosis or treatment. Follow the glucose targets and treatment plan recommended by your healthcare professional. Do not change insulin or diabetes medication doses without appropriate medical guidance.
Written by: Dr. Albana Greca, MD, MMedSc, Family Physician and Medical Author.
Medically reviewed by: Dr. Ruden Cakoni, MD, Endocrinologist.
Last reviewed: July 2026.
Quick Answer
Diabetes mellitus is a group of conditions in which blood glucose becomes too high because the body does not make enough insulin, cannot use insulin effectively, or both. The main forms are type 1 diabetes, type 2 diabetes, gestational diabetes, and other less common specific types.
Diabetes is diagnosed with laboratory blood tests—not symptoms or one home-meter reading alone. It can be managed through individualized nutrition, physical activity, glucose monitoring, education, and medicines or insulin when needed. Early diagnosis and ongoing care can substantially reduce the risk of complications.
Diabetes can feel confusing at first. You may hear about blood sugar, HbA1c, insulin resistance, carbohydrates, medicines, complications, and many different target numbers. This guide explains the essential information in one place and directs you to more detailed pages when you are ready.
For a step-by-step directory of the website’s blood sugar guides, calculators, medication pages, and patient questions, visit the Diabetes Answers and Tools Learning Center.
What Is Diabetes Mellitus?
Diabetes mellitus is diagnosed when blood glucose is persistently above established laboratory thresholds. It is not defined by one universal number such as 140 mg/dL, and hyperglycemia does not always mean that a person has chronic diabetes. Illness, stress, dehydration, pregnancy, and medicines such as corticosteroids can temporarily affect glucose.
The term mellitus distinguishes diabetes mellitus from the unrelated condition diabetes insipidus. In everyday conversation, “diabetes” usually means diabetes mellitus.
How Glucose and Insulin Normally Work
Glucose is an important fuel for the brain, muscles, and other tissues. It comes mainly from carbohydrate-containing foods and from glucose released or produced by the liver between meals and overnight.
Insulin is a hormone produced by beta cells in the pancreas. After eating, insulin helps glucose move from the bloodstream into many body cells and limits excessive glucose release by the liver.

The Main Types of Diabetes
| Type | What happens | Typical treatment considerations |
|---|---|---|
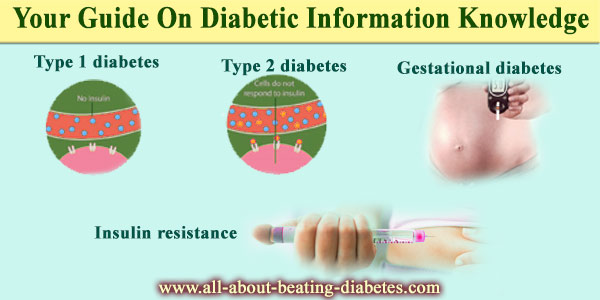
| Type 1 diabetes | An autoimmune process destroys insulin-producing beta cells. It can begin at any age. | Daily insulin is essential. Glucose and ketone monitoring, carbohydrate education, and emergency planning are important. |
| Type 2 diabetes | The body becomes resistant to insulin and may gradually produce too little insulin for its needs. | Nutrition, activity, weight management when appropriate, and individualized medicines; some people also need insulin. |
| Gestational diabetes | Diabetes first diagnosed during pregnancy that was not clearly present before pregnancy. | Pregnancy-specific glucose targets, nutrition therapy, monitoring, and sometimes insulin or another clinician-selected treatment. |
| Other specific types | May result from a genetic condition, pancreatic disease, endocrine disorder, medication, infection, or another identifiable cause. | Treatment depends on the cause and may differ from standard type 1 or type 2 care. |
Type 1 Diabetes
Type 1 diabetes is caused by autoimmune destruction of pancreatic beta cells. The body makes little or no insulin, so insulin treatment is necessary for survival. It is not caused by eating sugar, body weight, or personal failure.
Symptoms may develop quickly and include thirst, frequent urination, weight loss, fatigue, nausea, vomiting, abdominal pain, ketones, or deep breathing. Adults can also develop type 1 diabetes, so age alone should not be used to determine diabetes type.
Type 2 Diabetes
Type 2 diabetes usually develops through a combination of insulin resistance and gradual loss of adequate insulin secretion. Genetics, age, body-fat distribution, physical activity, sleep, medicines, pregnancy history, and social or environmental factors may all contribute.
Type 2 diabetes is not simply caused by eating too much sugar. Sugary drinks and excess calories can contribute to weight gain and metabolic risk, but the condition has multiple interacting causes.
Gestational Diabetes
Gestational diabetes occurs during pregnancy and often causes no symptoms. Testing is therefore essential. It usually resolves after delivery, but it increases the parent’s future risk of type 2 diabetes and requires postpartum follow-up.
Learn more from our guide to controlling gestational diabetes safely.
Other Specific Types
Less common forms include monogenic diabetes, cystic-fibrosis-related diabetes, diabetes after pancreatitis or pancreatic surgery, and diabetes related to certain medicines or endocrine disorders. Correct classification matters because treatment may change.
What Is Prediabetes?
Prediabetes means glucose is above the usual healthy range but below the diagnostic range for diabetes. It is a warning of increased risk rather than a guarantee that type 2 diabetes will develop.
Prediabetes also provides an opportunity for prevention. Structured nutrition, physical activity, weight reduction when appropriate, sleep improvement, and sometimes medication can reduce progression risk.
Insulin resistance often contributes to prediabetes and type 2 diabetes. Read more about what insulin resistance means and how it is assessed.
Common Diabetes Symptoms
Possible symptoms include:
- Frequent urination, including during the night
- Increased thirst or dry mouth
- Increased hunger
- Unexplained weight loss
- Fatigue or weakness
- Blurred vision
- Slow-healing cuts or repeated infections
- Tingling, burning, or numbness in the feet or hands
Type 2 diabetes and gestational diabetes may cause few or no symptoms. Symptoms are also nonspecific and can occur with many other conditions. Testing—not guesswork—is required.
Our detailed guide explains the symptoms of diabetes and when to arrange testing.
What Causes Diabetes?
There is no single cause that applies to every type:
- Type 1: An autoimmune process in a genetically susceptible person, probably influenced by environmental triggers that are still being studied.
- Type 2: A combination of genetic susceptibility, insulin resistance, impaired insulin secretion, aging, body-fat distribution, inactivity, sleep problems, and other metabolic or environmental factors.
- Gestational diabetes: Pregnancy-related hormonal and metabolic changes that increase insulin resistance in a susceptible person.
- Other types: Specific genetic changes, pancreatic damage, medicines, hormonal disorders, or other diseases.
Explore these mechanisms in more detail on our causes of diabetes overview.
Where Does Blood Glucose Come From?
Blood glucose comes from two main sources:
- Food: Carbohydrates are digested into glucose and other simple sugars. The liver converts some of these substances into forms the body can use or store.
- The liver: Between meals and overnight, the liver releases stored glucose and makes new glucose to maintain the body’s energy supply.
Protein and fat can also influence glucose indirectly, especially over several hours. This is why fasting glucose can be high even when a person has not eaten and why food is only one part of diabetes management.
How Is Diabetes Diagnosed?
Diabetes is diagnosed using laboratory blood tests. Common criteria for nonpregnant individuals include:
| Test | Prediabetes | Diabetes |
|---|---|---|
| Fasting plasma glucose | 100–125 mg/dL | 126 mg/dL or higher |
| HbA1c | 5.7–6.4% | 6.5% or higher |
| 2-hour glucose during a 75-g OGTT | 140–199 mg/dL | 200 mg/dL or higher |
| Random plasma glucose | No single prediabetes threshold | 200 mg/dL or higher with classic symptoms or hyperglycemic crisis |
Unless hyperglycemia is unmistakable or a crisis is present, an abnormal result usually needs confirmation. Pregnancy uses different testing pathways and thresholds.
A home glucose meter or continuous glucose monitor can identify concerning patterns, but it cannot independently establish a diabetes diagnosis. See our complete guide to blood tests for diabetes, including fasting glucose, HbA1c, and the OGTT.
How Diabetes Is Managed
Diabetes care should be individualized. The plan may include:
Glucose Monitoring
Finger-stick testing or a continuous glucose monitor can help identify fasting, after-meal, overnight, exercise, illness, and medication-related patterns. The schedule depends on diabetes type, medicines, insulin use, pregnancy, and risk of low glucose.
Balanced Nutrition
A diabetes-friendly eating pattern is not a “sugar-free” diet. Most people benefit from appropriate carbohydrate portions, vegetables, fiber-rich foods, protein, healthy fats, whole fruit rather than juice, and fewer sugar-sweetened drinks and heavily refined foods.
Learn how meals affect glucose in our guide to foods, drinks, and blood sugar.
Physical Activity
Regular activity can improve insulin sensitivity, cardiovascular fitness, mobility, and well-being. The type and amount should reflect age, fitness, heart health, eye disease, neuropathy, medications, and hypoglycemia risk.
Medicines and Insulin
People with type 1 diabetes require insulin. Type 2 diabetes treatment may include metformin, GLP-1 receptor agonists, SGLT2 inhibitors, DPP-4 inhibitors, sulfonylureas, insulin, or other therapies. The choice may consider glucose, heart and kidney disease, weight goals, hypoglycemia risk, cost, and patient preferences.
Read our overview of diabetes medicines, benefits, and side effects.
Weight, Sleep, and Emotional Health
Weight management may improve type 2 diabetes for some people, but advice should avoid blame and preserve nutrition and muscle. Sleep apnea, poor sleep, depression, chronic stress, and diabetes distress also deserve assessment and support.
Routine Preventive Care
Diabetes management also includes blood-pressure and cholesterol care, kidney testing, dilated eye examinations, foot checks, dental care, vaccinations, smoking cessation, and regular review of medicines and treatment goals.


Can Diabetes Be Cured or Reversed?
There is currently no general cure for type 1 diabetes or type 2 diabetes. Some people with type 2 diabetes can achieve remission, often after substantial and sustained weight loss or metabolic surgery. Remission means glucose remains below the diabetes range without glucose-lowering medication for a defined period; it does not guarantee that diabetes will never return.
Herbs, detoxes, vitamins, chromium, cinnamon, bitter melon, and other supplements should not be presented as proven cures. Some products can interact with medicines or cause side effects. Do not replace insulin or prescribed treatment with a supplement.
Possible Complications
Over time, persistent hyperglycemia can damage blood vessels and nerves. Diabetes may increase the risk of:
- Heart disease and stroke
- Chronic kidney disease
- Retinopathy and vision loss
- Peripheral and autonomic neuropathy
- Foot ulcers, infections, and amputation
- Dental and gum disease
- Sexual and bladder problems
- Severe hypoglycemia from some treatments
- Diabetic ketoacidosis or hyperglycemic hyperosmolar state
Complications are not inevitable. Glucose management, blood-pressure and cholesterol care, smoking cessation, appropriate medicines, and regular screening can substantially reduce risk.
Learn how screening and early treatment help in our overview of diabetes complications and prevention.
Can Type 2 Diabetes Be Prevented?
Type 1 diabetes cannot currently be prevented through diet or lifestyle. Type 2 diabetes can often be delayed or prevented in people at high risk through structured lifestyle intervention.
Helpful strategies may include:
- Regular physical activity
- Reducing prolonged sitting
- A balanced, fiber-rich eating pattern
- Weight loss when medically appropriate
- Adequate sleep and treatment of sleep apnea
- Smoking cessation
- Managing blood pressure and cholesterol
- Medication such as metformin for selected high-risk individuals
Prevention advice should be realistic and individualized. Genetics, medication effects, disability, food access, stress, work schedules, and social conditions also affect risk.
When to Arrange Diabetes Testing
Ask about testing when you have symptoms, a previous high result, gestational-diabetes history, polycystic ovary syndrome, cardiovascular disease, overweight or obesity, a close family history, high blood pressure, abnormal cholesterol, or other significant risk factors.
Adults should also receive age-appropriate screening even without symptoms, according to current clinical guidance. Children and adolescents with overweight or obesity and additional risk factors may need screening as well.
When High or Low Blood Sugar Is an Emergency
Seek Urgent Medical Help
Get urgent or emergency care for vomiting, abdominal pain, deep or difficult breathing, fruity-smelling breath, confusion, severe dehydration, fainting, seizures, inability to swallow safely, or moderate or large ketones.
Severe low blood sugar, loss of consciousness, stroke symptoms, or chest pain also requires emergency assistance. Do not give food or drink to an unconscious person.
Very high and very low readings require action based on symptoms, diabetes type, medicines, ketones, and the person’s written plan. Review our guide to determine whether blood sugar may be too high or too low.
Doctor’s Note
Diabetes is not one disease with one treatment. Correct classification, accurate testing, and an individualized plan matter. Ask not only, “What is my glucose?” but also, “What type of diabetes do I have, what are my heart and kidney risks, am I having low glucose, and is my plan practical and safe?”
Most Asked Questions
Is diabetes caused by eating sugar?
No. Eating large amounts of sugary food or drinks can contribute to excess calorie intake and type 2 diabetes risk in some people, but type 1, type 2, gestational, and other forms have different and more complex causes.
Does blood sugar above 140 mg/dL mean diabetes?
Not automatically. Interpretation depends on whether the test was fasting, after a glucose drink, after a meal, or random. Diagnosis uses established laboratory criteria and often needs confirmation.
Can someone have diabetes without symptoms?
Yes. Type 2 and gestational diabetes may cause no obvious symptoms. Screening is important when risk factors are present.
Can type 1 diabetes begin in adulthood?
Yes. Type 1 diabetes can begin at any age. Adults with rapid symptoms, weight loss, ketones, or unexpected insulin deficiency need prompt assessment.
Can people with diabetes eat carbohydrates?
Yes. Carbohydrate type, amount, timing, medicines, and the complete meal affect glucose. Most people need an individualized plan rather than total carbohydrate avoidance.
Can walking lower blood sugar?
Physical activity can improve insulin sensitivity and may lower glucose, but it must be used safely. Do not exercise through severe hyperglycemia, ketones, dehydration, chest pain, or serious illness.
Can supplements control diabetes?
No supplement is a replacement for proven diabetes care. Evidence for many products is limited, and some can interact with medicines or cause liver, kidney, bleeding, or hypoglycemia problems.
Educational safety note: This article provides general diabetes education and does not replace personal medical advice, diagnosis, or treatment. Do not start, stop, or change insulin, diabetes medicines, supplements, carbohydrate targets, weight-loss plans, or exercise without speaking with your healthcare professional.
Related Questions
- Is My Body Showing Signs of Diabetes?
- Is Fasting Blood Sugar of 122 mg/dL a Sign of Diabetes?
- Is Fasting Blood Sugar of 126 mg/dL High?
- What Does HbA1c 6.6% Mean When Home Readings Look Normal?
- At What Blood Sugar Level Should I Go to the Hospital?
Related Resources
- Diabetes Answers and Tools Learning Center
- Blood Tests for Diabetes
- Symptoms of Diabetes
- Causes of Diabetes
- Blood Sugar Levels by Time of Day
- HbA1c Explained
- Blood Sugar Level Control
- Diabetes Complications
References
- American Diabetes Association Professional Practice Committee. Diagnosis and Classification of Diabetes: Standards of Care in Diabetes—2026.
- American Diabetes Association Professional Practice Committee. Standards of Care in Diabetes—2026.
- Centers for Disease Control and Prevention. Diabetes Basics.
- Centers for Disease Control and Prevention. Symptoms of Diabetes.
- National Institute of Diabetes and Digestive and Kidney Diseases. Diabetes Overview.
- National Institute of Diabetes and Digestive and Kidney Diseases. Diabetes Tests and Diagnosis.
- National Institute of Diabetes and Digestive and Kidney Diseases. Managing Diabetes.
- World Health Organization. Diabetes.