- Home
- blood sugar levels
- Blood Sugar over 400 mg/dl
Blood Sugar Over 400 mg/dL: What to Do and When to Seek Emergency Care
A blood sugar level above 400 mg/dL (22.2 mmol/L) is a medical emergency until proven otherwise. It may signal severe hyperglycemia and can lead to life-threatening complications such as diabetic ketoacidosis (DKA) or hyperosmolar hyperglycemic state (HHS). This guide explains the possible causes, warning signs, immediate treatment steps, and when to seek emergency medical care.
Written by: Dr. Albana Greca, MD, MMedSc, Family Physician and Medical Author, IDF Fellow.
Medically reviewed by: Dr. Ruden Cakoni, MD, Endocrinologist.
Last reviewed: July 2026.
⚠ Emergency Quick Answer
Blood sugar over 400 mg/dL (22.2 mmol/L) is severe hyperglycemia that requires immediate medical attention. Wash and dry your hands, repeat the finger-stick test, and check ketones if available. Seek urgent medical assessment without delay.
Go to the emergency department immediately if your glucose remains above 400 mg/dL, you have moderate or large urine ketones, significantly elevated blood ketones, vomiting, abdominal pain, difficulty breathing, confusion, or signs of severe dehydration.
Important: Do not exercise or take extra insulin unless following your prescribed correction plan. If you cannot check ketones, do not delay medical assessment.
A glucose result above 400 mg/dL is not simply “a little high.” It may occur with previously undiagnosed diabetes or with diabetes that is not receiving enough effective insulin or medication. It can progress to life-threatening dehydration, diabetic ketoacidosis (DKA), or hyperglycemic hyperosmolar state (HHS).
The reading needs attention whether it was measured fasting, after eating, after medication, or during illness. The cause may differ, but the immediate safety steps are similar.
What Does Blood Sugar Over 400 mg/dL Mean?
A reading above 400 mg/dL means there is a very high concentration of glucose in the bloodstream. At this level, the kidneys try to remove excess glucose through the urine, which pulls water and electrolytes from the body and can cause serious dehydration.
Blood sugar above 400 mg/dL does not by itself tell us whether a person has type 1 diabetes, type 2 diabetes, DKA, or HHS. Ketones, symptoms, hydration, blood chemistry, medical history, and laboratory tests are needed to determine the cause and severity.
| Finding | What it may mean | Recommended action |
|---|---|---|
| One meter reading over 400 mg/dL | Severe hyperglycemia or, less commonly, a testing error | Wash and dry hands, repeat once, check ketones, and seek urgent medical advice. |
| Persistent reading over 400 mg/dL | Insufficient effective insulin, illness, medication effect, or another urgent problem | Go to the emergency department if the reading remains this high. |
| High glucose with ketones or serious symptoms | Possible DKA or another hyperglycemic emergency | Go to the emergency department immediately. |
What to Do Immediately
- Wash and dry your hands, then test again. Sugar, fruit, or food residue can falsely raise a finger-stick result. Use an unexpired strip stored correctly.
- Check blood or urine ketones. Follow your personal sick-day plan. Moderate or large ketones require urgent medical advice and often emergency assessment.
- Use only your written correction plan. Do not guess an extra insulin dose, double a dose, or borrow another person’s insulin.
- Drink water if you can do so safely. Take small, frequent sips unless you have been told to restrict fluids because of heart or kidney disease.
- Do not exercise. Exercise can worsen hyperglycemia and ketone production when there is not enough effective insulin.
- Contact your diabetes team or urgent-care service now. Give them the glucose result, ketone level, symptoms, insulin or medication details, and any recent illness.
Important: Blood beta-hydroxybutyrate testing is preferred when available. A result of 3.0 mmol/L or higher, or moderate to large urine ketones, requires emergency evaluation. Lower ketone levels do not rule out a serious problem, particularly if symptoms are present. Do not delay emergency care while trying to obtain a ketone test.
Do not stop insulin, diabetes medicine, antibiotics, steroids, heart medicine, or blood-pressure medicine without the prescriber’s instructions.
Why Can Fasting Blood Sugar Be Over 400 mg/dL?
During fasting, the liver normally releases glucose to supply the brain and other organs. Insulin limits this release. When the body lacks enough effective insulin, the liver may release too much glucose while the muscles and other tissues cannot use it properly.
Possible causes include:
- Previously undiagnosed diabetes
- Missed, delayed, or insufficient insulin or medication
- Insulin pump, infusion-set, pen, syringe, or injection-site problems
- Expired, frozen, overheated, or damaged insulin
- Infection, fever, inflammation, surgery, pain, or another illness
- Steroid treatment or another medication that raises glucose
- Severe dehydration
- A treatment plan that no longer meets the person’s needs
A late meal or the dawn phenomenon can contribute to high morning glucose, but they should not be used to dismiss a fasting level above 400 mg/dL.
Why Can Blood Sugar Rise Over 400 mg/dL After Eating?
Carbohydrates are broken down into glucose. In people without diabetes, insulin usually limits the after-meal rise. In diabetes, a very large meal, insufficient mealtime insulin, delayed insulin, incorrect carbohydrate counting, or a medication problem may cause glucose to remain dangerously high.
However, food is not always the main cause. Infection, dehydration, steroid use, pump failure, or severe insulin deficiency can produce high readings even when a person has eaten little.
For context, a common after-meal target for many nonpregnant adults with diabetes is below 180 mg/dL one to two hours after the start of a meal, although targets are individualized. A result above 400 mg/dL is far above an ordinary treatment target.
Can Medicines Cause Blood Sugar Over 400 mg/dL?
Some medicines can raise glucose or make diabetes more difficult to control. Corticosteroids are a common example. Certain antipsychotics, immunosuppressants, and other medicines may also contribute.
Do not stop a prescribed medicine suddenly. Some drugs, especially steroids, can be dangerous to stop without a supervised taper. Contact the prescribing clinician so the benefits, risks, glucose pattern, and possible treatment adjustments can be reviewed safely.
Symptoms of Blood Sugar Over 400 mg/dL
Symptoms may include:
- Extreme thirst and dry mouth
- Frequent urination
- Blurred vision
- Fatigue, weakness, or drowsiness
- Headache
- Nausea or vomiting
- Abdominal pain
- Rapid or deep breathing
- Fruity-smelling breath
- Confusion or reduced alertness
- Very dry skin or other signs of dehydration
Some people, especially those with long-standing type 2 diabetes, may have fewer symptoms than expected. The absence of dramatic symptoms does not make a persistent reading above 400 mg/dL safe.
Diabetic Ketoacidosis and HHS
Diabetic ketoacidosis
DKA develops when the body does not have enough effective insulin and begins breaking down fat rapidly, producing acidic ketones. It is more common in type 1 diabetes, but it can also occur in type 2 diabetes, during pregnancy, and with certain diabetes medicines.
Warning signs include ketones, vomiting, abdominal pain, dehydration, fruity breath, rapid or deep breathing, and confusion. DKA can occur at glucose levels below 400 mg/dL, so the glucose number alone cannot rule it in or out.
Hyperglycemic hyperosmolar state
Hyperglycemic hyperosmolar state (HHS) is a life-threatening complication, most often seen in people with type 2 diabetes. Diagnostic criteria typically include plasma glucose of 600 mg/dL (33.3 mmol/L) or higher, increased blood osmolality, and laboratory evidence distinguishing HHS from DKA. HHS cannot be diagnosed from a home glucose reading alone.
How Is Severe Hyperglycemia Treated?
Treatment depends on the cause, symptoms, ketones, hydration, and laboratory findings. DKA and HHS are treated in a monitored medical setting with intravenous fluids, insulin, electrolyte replacement, frequent laboratory testing, and treatment of the trigger, such as infection or insulin interruption.
Do not attempt to reproduce hospital treatment at home. Potassium and other electrolytes may shift dangerously during treatment, which is one reason close monitoring is required.
Information to Prepare Before You Call
- Current glucose result and recent readings
- Whether the readings were fasting or after meals
- Blood or urine ketone result
- Symptoms and when they began
- Insulin names, doses, and injection times
- Diabetes medicines and any missed doses
- Recent meals and fluid intake
- Fever, infection, vomiting, diarrhea, surgery, injury, or pain
- New medicines, especially steroids
- Whether you use a pump or continuous glucose monitor
- Pregnancy, kidney disease, heart disease, or fluid restrictions
A written blood sugar log helps the care team see whether the problem is new, repeated, meal-related, or associated with missed medication or illness.
How to Reduce the Risk of Another Reading Over 400 mg/dL
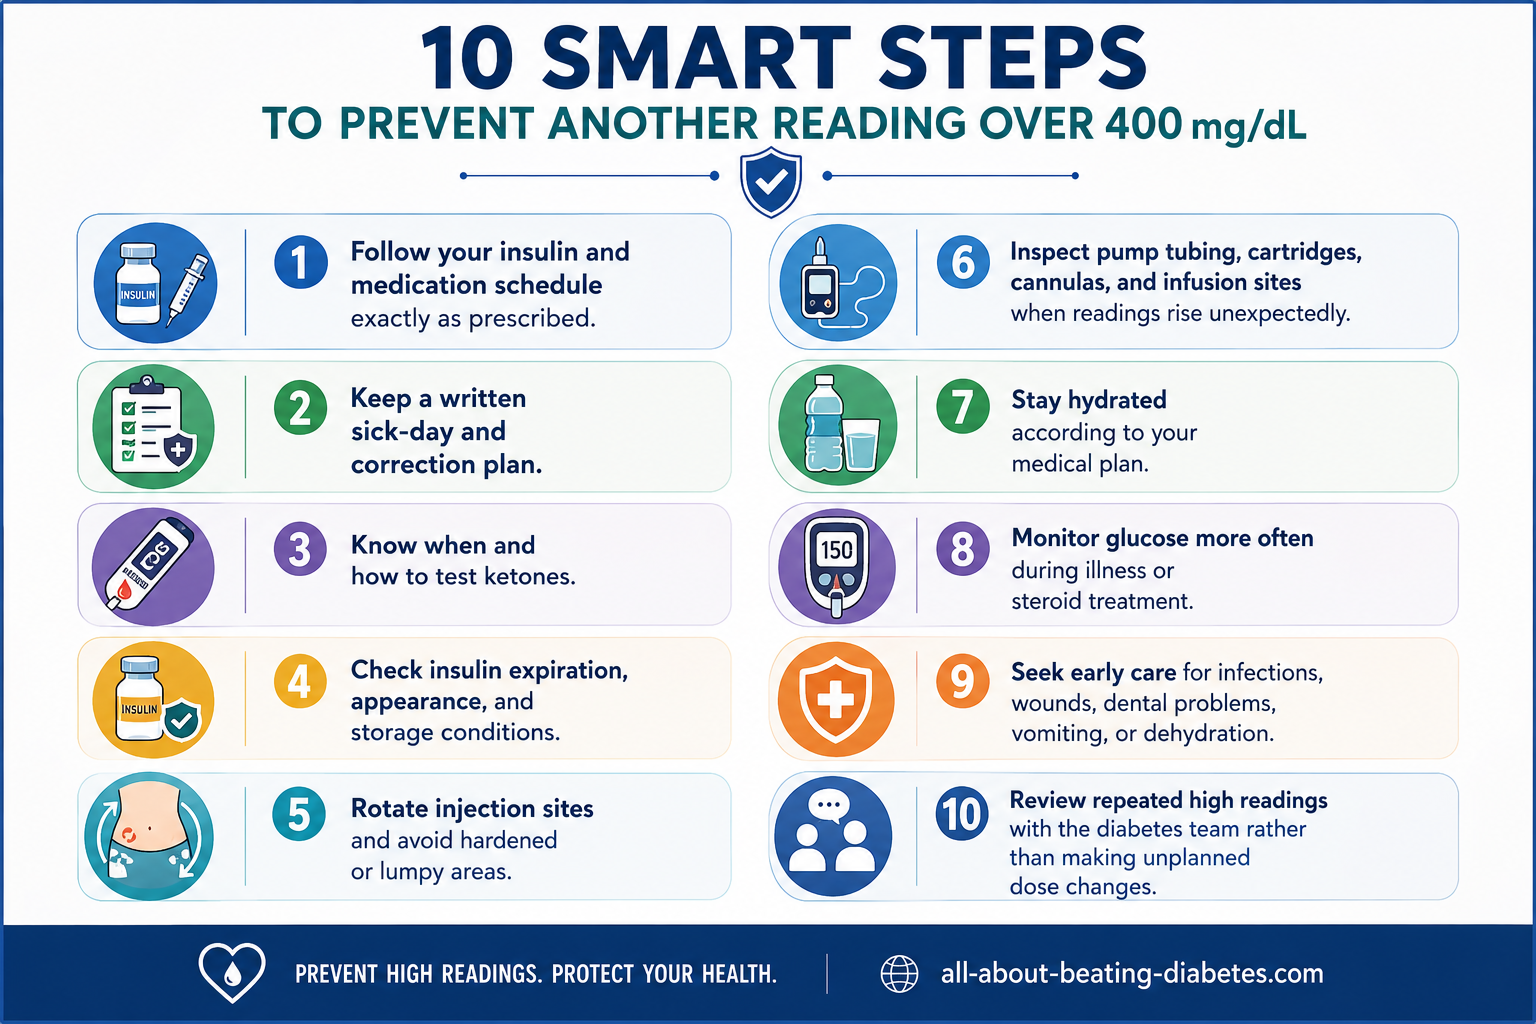
A blood sugar reading above 400 mg/dL often indicates that your diabetes management plan needs immediate attention. While emergency treatment focuses on lowering the current glucose level safely, preventing future episodes is equally important. The infographic below outlines practical steps that can reduce the risk of another severe high blood sugar episode and help you respond promptly if one occurs.

Balanced eating, weight management, smoking cessation, and regular activity support long-term diabetes care. They are not substitutes for urgent treatment during severe hyperglycemia. Do not exercise while glucose is extremely high with possible ketones or dehydration.
Important Safety Note: Who Needs Extra Caution?
Some people face additional risks when blood sugar rises above 400 mg/dL (22.2 mmol/L). Children, pregnant people, individuals with type 1 diabetes, insulin-pump users, frail older adults, and people with kidney or heart disease require especially prompt medical assessment.
Why this matters: Children and people with type 1 diabetes may develop diabetic ketoacidosis rapidly. Insulin-pump interruption can also cause dangerous insulin deficiency within hours. Older adults may be especially vulnerable to dehydration, while kidney or heart disease can complicate fluid management. Pregnancy requires particular caution because ketoacidosis can develop at lower glucose levels.
Key Medical Takeaways
- Blood sugar above 400 mg/dL (22.2 mmol/L) needs immediate medical attention, even if symptoms seem mild.
- If you have no emergency symptoms, wash and dry your hands, repeat the test with a new strip, and check ketones if available. Contact your diabetes team immediately. Do not delay emergency care to repeat testing or find ketone supplies.
- Go to the emergency department if glucose remains this high, or you have high ketones, vomiting, trouble breathing, fruity-smelling breath, confusion, or cannot keep fluids down. Call your local emergency number for severe symptoms.
- Use only your prescribed insulin correction plan. Do not guess extra doses, repeat insulin too soon, or exercise to lower this reading.
- Sip water if you can swallow safely and have no prescribed fluid restriction. Water does not replace insulin or emergency treatment.
Source: CDC: Diabetic Ketoacidosis . CDC advises emergency care when blood sugar stays at 300 mg/dL or above.
Most Asked Questions
Is blood sugar over 400 mg/dL always an emergency?
Blood sugar over 400 mg/dL (22.2 mmol/L) always requires urgent medical attention, but it does not automatically mean diabetic ketoacidosis (DKA) or hyperosmolar hyperglycemic state (HHS). If a repeat reading remains above 400 mg/dL, seek emergency medical assessment. Do not wait for symptoms to develop.
DKA and HHS are diagnosed using symptoms and laboratory findings, including ketones, blood acidity, electrolytes, and hydration status, not glucose alone.
Should I take extra insulin?
Use only the correction dose already prescribed for you. Do not guess a dose or repeat insulin too soon because insulin stacking can cause delayed severe hypoglycemia.
Should I drink water?
Small, frequent sips may help reduce dehydration if you can swallow safely and have no fluid restriction. Water does not replace insulin or emergency treatment.
Can I exercise to lower a reading over 400 mg/dL?
No. Exercise is not a safe home treatment at this level when ketones, dehydration, or insulin deficiency may be present.
Can DKA happen in type 2 diabetes?
Yes. DKA is more common in type 1 diabetes, but it can occur in type 2 diabetes, pregnancy, severe illness, and in association with some diabetes medicines.
Should I stop the medicine that may have caused the high glucose?
No. Contact the prescriber promptly. Stopping steroids or other prescribed medicines suddenly may be harmful.
Educational safety note: This article provides general diabetes education and does not replace emergency assessment, diagnosis, or personal treatment instructions. Do not start, stop, or change insulin, diabetes medicines, steroids, other prescriptions, diet, supplements, or exercise without guidance from your healthcare professional.
Related Questions
- Why Is Blood Sugar Still 400–500 mg/dL After Insulin?
- At What Blood Sugar Level Should I Go to the Hospital?
- Why Is Blood Sugar Very High Even While Using Insulin?
- What Can Cause Blood Sugar as High as 656 mg/dL?
- Why Isn’t My Blood Sugar Going Down?
Related Resources
- Dangerous Blood Sugar Levels and Warning Signs
- Blood Sugar Between 250 and 400 mg/dL
- Is My Blood Sugar Too High or Too Low?
- Understanding Insulin Treatment
- Convert Blood Sugar Between mmol/L and mg/dL
References
- American Diabetes Association Professional Practice Committee. Glycemic Goals, Hypoglycemia, and Hyperglycemic Crises: Standards of Care in Diabetes—2026.
- American Diabetes Association Professional Practice Committee. Diabetes Care in the Hospital: Standards of Care in Diabetes—2026.
- Umpierrez GE, et al. Hyperglycemic Crises in Adults With Diabetes: A Consensus Report.
- Centers for Disease Control and Prevention. Diabetic Ketoacidosis.
- Centers for Disease Control and Prevention. Managing Sick Days.
- American Diabetes Association. Hyperglycemia (High Blood Glucose).