- Home
- Diabetes Complications
- Diabetic Kidney Disease Symptoms and Treatment
Diabetic Kidney Disease: Symptoms, Tests, Stages, Treatment, and Prevention
If you live with diabetes, it is understandable to want a simple answer to the question, “What blood sugar should I aim for?”
For many adults, there are well-established treatment targets. However, I always remind my patients that these are general goals, not one-size-fits-all rules. Your safest target depends on your age, type and duration of diabetes, medicines, risk of hypoglycemia, pregnancy status, kidney or heart disease, and overall health.
The goal is not to keep glucose at one perfect number all day. It is to remain within a safe range as consistently as possible while avoiding prolonged high blood sugar and unnecessary low blood sugar.
Quick Answer: Common Blood Glucose Targets
For many nonpregnant adults with diabetes, commonly used treatment goals are:
- Before meals: 80–130 mg/dL (4.4–7.2 mmol/L)
- Peak after meals: below 180 mg/dL (below 10.0 mmol/L), measured 1–2 hours after the beginning of the meal
- A1C: below 7% (below 53 mmol/mol), when this can be achieved safely
| Measurement | Common target | What it means |
|---|---|---|
| Before meals | 80–130 mg/dL (4.4–7.2 mmol/L) |
A common premeal target for many nonpregnant adults |
| Peak after meals | Below 180 mg/dL (below 10.0 mmol/L) |
Usually assessed 1–2 hours after the beginning of the meal |
| A1C | Below 7% (below 53 mmol/mol) |
A common longer-term goal when it can be reached safely |
What Does “Acceptable Blood Glucose” Mean?
An acceptable blood glucose level is not necessarily the same as a “normal” glucose level in someone without diabetes.
When we set a diabetes target, we balance two priorities: keeping glucose low enough to reduce the risk of long-term complications while avoiding hypoglycemia and treatment that is too aggressive for the individual patient.
A single blood glucose reading does not provide a complete picture of diabetes control. In clinical practice, I consider the broader pattern, including fasting and premeal glucose levels, post-meal readings when appropriate, A1C, episodes of hypoglycemia, symptoms, current medications, and, when available, continuous glucose monitoring (CGM) data. These measures should also be interpreted in the context of established blood glucose and A1C ranges for normal glucose, prediabetes, and diabetes.
Acceptable Blood Glucose Before Meals
For many nonpregnant adults with diabetes, a common target before meals is 80–130 mg/dL (4.4–7.2 mmol/L).
This gives us useful information about your baseline glucose before food begins to raise it. If most of your premeal readings are within your agreed target, that is encouraging, but they should still be interpreted together with your post-meal pattern, A1C, low-glucose episodes and overall treatment plan.
A reading of 80 mg/dL is not hypoglycemia. It is near the lower end of the usual premeal target. Hypoglycemia is generally defined as glucose below 70 mg/dL.
If fasting or premeal readings are repeatedly above your personal target, possible contributors include overnight glucose production, meal or medication timing, illness, poor sleep, stress and changes in physical activity. A pattern over several days is more informative than one isolated morning reading.
If morning glucose is your main concern, see our guide to fasting blood sugar levels.
Acceptable Blood Glucose After Meals
For many adults with diabetes, a common target is a peak post-meal glucose below 180 mg/dL (10.0 mmol/L).
When post-meal glucose is being assessed, it is generally measured 1–2 hours after the beginning of the meal. The timing matters because this period is intended to capture glucose near its post-meal peak.
One reading slightly above 180 mg/dL does not necessarily mean your treatment is failing. A larger meal, more carbohydrate than usual, illness, stress, poor sleep or reduced activity can all affect the result. More important questions are whether higher readings occur frequently, remain elevated for a long time, or appear alongside an A1C or CGM pattern showing excessive glucose exposure.
Because blood glucose changes throughout the day, the timing of a measurement matters, particularly when interpreting blood sugar levels after eating.
How Does A1C Fit With Daily Blood Sugar Targets?
Daily readings show what your blood sugar is doing at a particular moment. A1C provides a broader view of glucose exposure over the previous two to three months, with more recent weeks contributing more to the result.
For many nonpregnant adults with diabetes, a common A1C goal is below 7% (53 mmol/mol) when it can be achieved safely. Some people may benefit from a lower goal. Others need a less stringent goal because hypoglycemia, frailty, serious comorbidities, cognitive or functional limitations, or treatment burden makes tighter control less safe.
I would not interpret A1C in isolation. Two people can have the same A1C while experiencing very different patterns of highs and lows.
Learn more in A1C vs Blood Sugar, or use our HbA1c to Average Glucose Calculator.
What If I Use a Continuous Glucose Monitor?
A continuous glucose monitor, or CGM, helps us look beyond individual fingerstick readings. It shows how much time glucose spends within, above and below the target range.
| CGM metric | Common goal for many adults |
|---|---|
| Time in range: 70–180 mg/dL | More than 70% of the time |
| Time below 70 mg/dL | Less than 4% of the time |
| Time below 54 mg/dL | Less than 1% of the time |
| Time above 180 mg/dL | Less than 25% of the time |
CGM goals also need to be individualized. Some older adults with complex health problems, for example, may need more permissive goals to reduce the risk of hypoglycemia.
What About Bedtime Blood Sugar?
There is no single bedtime glucose target appropriate for every adult with diabetes. Bedtime goals depend on insulin use, risk of overnight hypoglycemia, age, other medical conditions, recent exercise, meal timing and the treatment plan you follow.
If you use insulin or medicines that can cause hypoglycemia, your clinician may give you a specific bedtime target. Follow that individualized plan rather than relying on a universal bedtime number from the internet.
What Is Considered Low Blood Sugar?
For people with diabetes, glucose below 70 mg/dL (3.9 mmol/L) is considered hypoglycemia and should be taken seriously. A level below 54 mg/dL (3.0 mmol/L) is more clinically significant.
Symptoms may include shakiness, sweating, hunger, palpitations, dizziness, weakness, irritability, confusion or difficulty concentrating. If you have a hypoglycemia treatment plan, follow it promptly. Frequent low readings require medical review because medication dose, meal timing or activity may need adjustment.
Why Your Personal Target May Be Different
I would not give exactly the same glucose goal to every patient. Your targets may need to be individualized if you:
- are pregnant or planning pregnancy;
- are a child or adolescent;
- are an older adult;
- have frequent or severe hypoglycemia;
- have impaired awareness of low blood sugar;
- have significant kidney, heart, liver or other medical disease;
- have cognitive or functional limitations;
- have lived with diabetes for many years; or
- use insulin or medicines that increase hypoglycemia risk.
An older adult who is otherwise healthy may still have relatively tight glucose goals. Someone with frailty, several serious illnesses or recurrent hypoglycemia may need more relaxed targets because preventing low blood sugar becomes the greater priority.

What Can Affect Your Blood Glucose Readings?
Even when your treatment plan has not changed, glucose can vary from day to day. Common influences include:
- meal size and carbohydrate content;
- physical activity;
- stress and sleep;
- infection, illness or pain;
- dehydration or alcohol;
- hormonal changes;
- medication timing;
- missed insulin or diabetes medicine; and
- corticosteroids and some other medicines.
This is why I encourage patients to look for patterns rather than reacting strongly to one unusual result.

How to Keep Blood Glucose Closer to Your Target
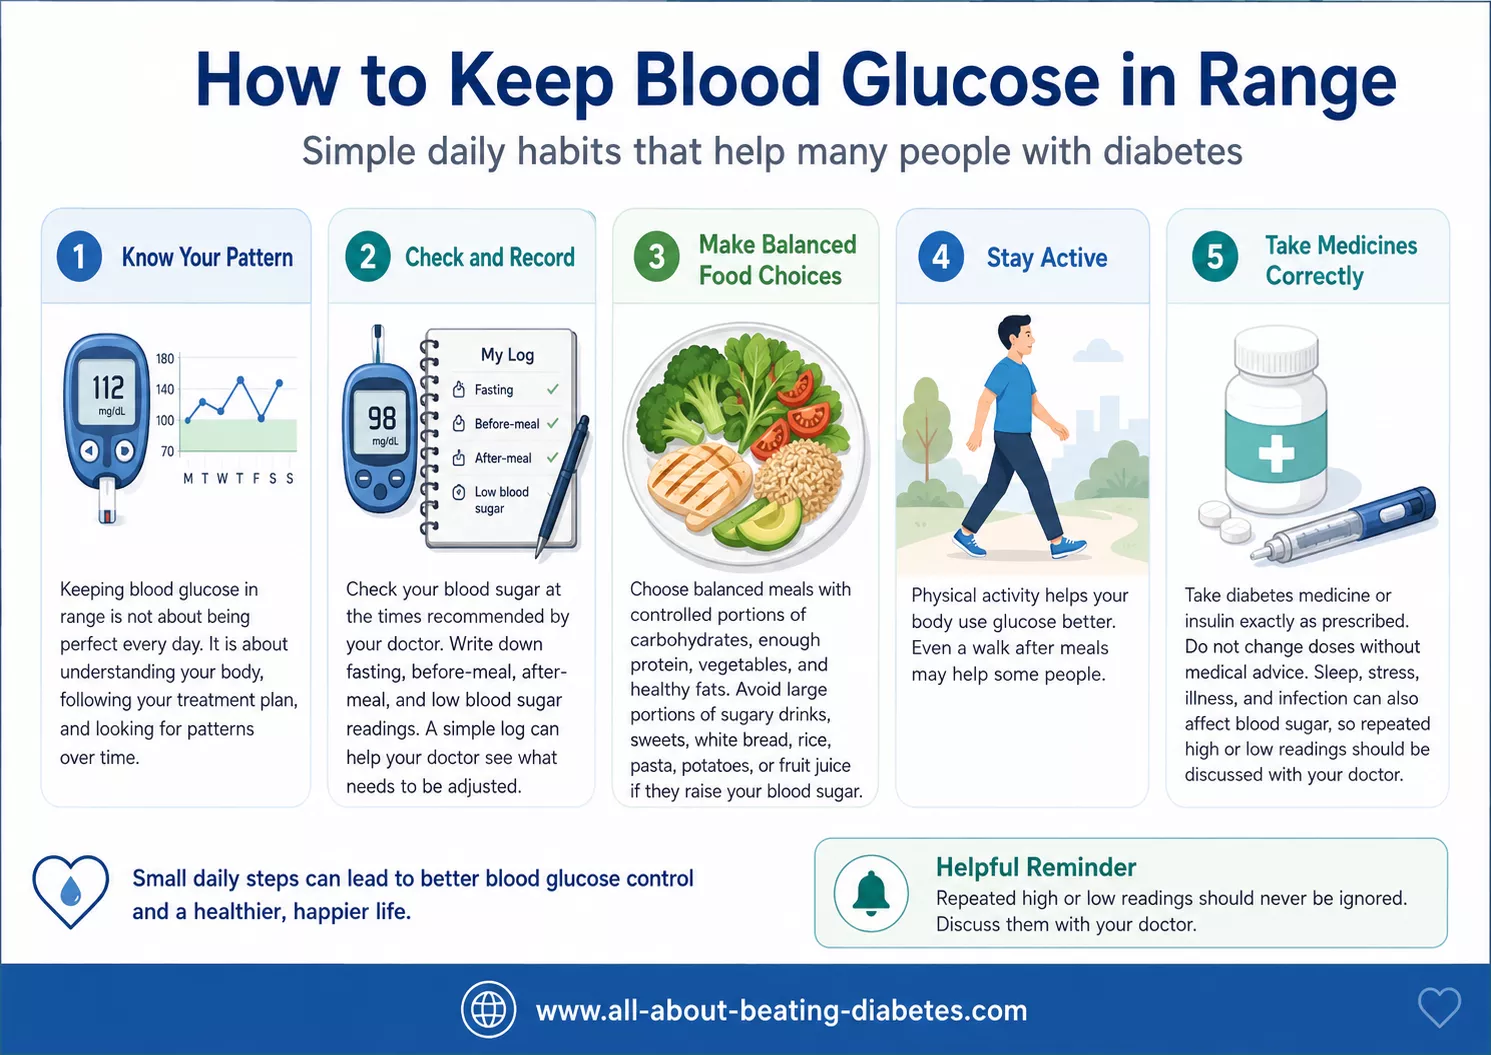
Keeping glucose in range does not require perfect numbers every day. The practical goal is to make the overall pattern safer and more consistent. Depending on your treatment plan, helpful steps may include:
- taking insulin or diabetes medicine exactly as prescribed;
- checking glucose at the times recommended by your healthcare team;
- keeping carbohydrate portions reasonably consistent when this is part of your plan;
- choosing meals with vegetables, protein, fiber and appropriate carbohydrate portions;
- being physically active regularly;
- reviewing repeated highs or lows instead of changing medication on your own;
- paying attention to sleep, illness, stress and hydration; and
- bringing your glucose log or CGM report to medical appointments.
Do not change insulin or medication doses because of one unusual result unless your healthcare professional has given you a specific adjustment plan.
Dr. Albana’s Perspective
When a patient asks whether a blood sugar number is “acceptable,” I first ask when it was measured and what target we agreed on for that person.
A premeal glucose of 125 mg/dL may be within the usual target for many adults with diabetes. The same number means something different if we are discussing a fasting laboratory test used to screen a person who has not been diagnosed with diabetes.
I also do not judge diabetes control from one good reading or one bad reading. I want to know whether most values are reasonably close to target, whether there are repeated highs, whether low glucose is occurring, and whether the A1C or CGM report tells the same story.
The best target is not the lowest number you can achieve. It is the range that offers meaningful long-term protection while remaining safe and realistic for your health and treatment.
When Should You Contact Your Doctor?
Contact your healthcare team if:
- glucose is repeatedly above your agreed target;
- you have repeated readings below 70 mg/dL;
- you experience nighttime hypoglycemia;
- your A1C is rising despite apparently reasonable daily readings;
- your CGM shows frequent highs or lows;
- you are ill and glucose becomes difficult to control;
- you are unsure whether medication or insulin needs adjustment; or
- your target may no longer be appropriate because of pregnancy, aging or a new medical condition.
Related Questions
Is 130 mg/dL acceptable for someone with diabetes?
It depends on when it was measured. For many nonpregnant adults, 130 mg/dL is at the upper end of the common premeal target. After a meal, it may also be within an acceptable range, but your individual target may differ.
Is 180 mg/dL after eating acceptable?
For many adults with diabetes, the common goal is a peak post-meal glucose below 180 mg/dL, assessed 1–2 hours after the beginning of the meal. Frequent readings at or above this level should be reviewed as a pattern.
Is 70 mg/dL acceptable?
Seventy mg/dL is the threshold at which we become concerned about hypoglycemia. A reading below 70 mg/dL should be treated according to your diabetes plan, and repeated lows should be discussed with your healthcare team.
Should everyone with diabetes have the same glucose target?
No. Age, pregnancy, medications, hypoglycemia risk, kidney or heart disease, functional status and other health conditions can all affect the safest goal.
What should my blood sugar be at bedtime?
There is no universal bedtime target for every adult with diabetes. Your bedtime goal should reflect your treatment plan, especially if you use insulin or are at risk of overnight hypoglycemia.
Is A1C below 7% right for everyone?
No. Below 7% is a common goal for many nonpregnant adults, but some people may benefit from a lower goal and others need a less stringent one for safety.
Related Tools and Calculators
Related Resources
Final Key Message
For many nonpregnant adults with diabetes, common treatment goals are 80–130 mg/dL before meals, below 180 mg/dL at the peak after meals, and A1C below 7% when these goals can be achieved safely.
If you use CGM, spending more than 70% of the time between 70 and 180 mg/dL is a common goal for many adults, while time below 70 mg/dL should remain limited.
Most importantly, your target should fit you. A safe plan balances glucose control with your risk of hypoglycemia, medications, age, other medical conditions and daily life. I would rather see a patient follow a realistic, individualized target safely and consistently than chase a “perfect” number that creates unnecessary risk.
References
- American Diabetes Association Professional Practice Committee. Glycemic Goals, Hypoglycemia, and Hyperglycemic Crises: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl. 1).
- American Diabetes Association Professional Practice Committee. Older Adults: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl. 1).
- American Diabetes Association. Checking Your Blood Sugar.
- National Institute of Diabetes and Digestive and Kidney Diseases. Managing Diabetes. National Institutes of Health.
Medical disclaimer: This information is for general education and does not replace professional medical advice, diagnosis or treatment. Follow the glucose targets and treatment plan recommended by your healthcare professional. Do not change insulin or diabetes medication doses without appropriate medical guidance.
Diabetic kidney disease is a common complication of diabetes that develops when persistently high blood sugar damages the kidneys’ filtering system. It often causes no symptoms in the early stages, which is why regular urine and blood tests are essential. Early diagnosis, good glucose and blood pressure control, kidney-protective medicines, and healthy lifestyle habits can help slow progression and reduce the risk of kidney failure.
Written by Dr. Albana Greca, MD, MMedSc, Family Physician
Medically reviewed by Dr. Ruden Cakoni, MD, Endocrinologist
Last reviewed: July 2026
Quick Answer
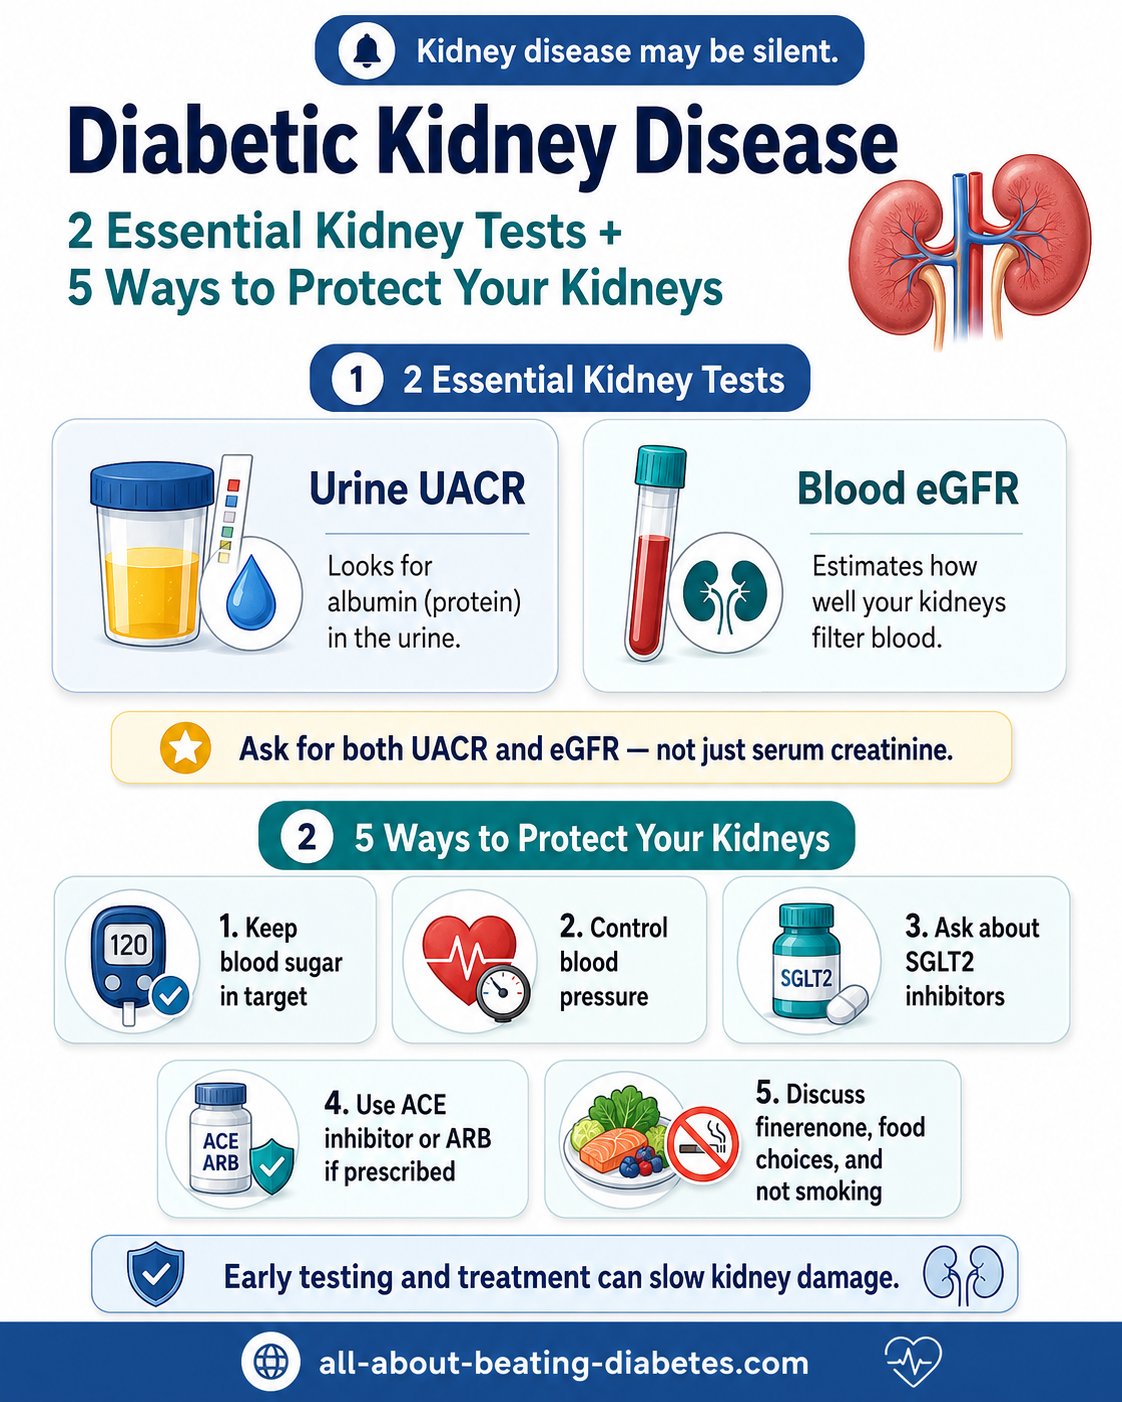
Diabetic kidney disease is chronic kidney damage associated with diabetes. It often causes no symptoms at first, so regular testing is essential. The two key tests are a urine albumin-to-creatinine ratio, called UACR, and a blood estimated glomerular filtration rate, called eGFR.
Treatment can substantially slow progression. Important measures include individualized glucose control, blood-pressure management, an ACE inhibitor or ARB when indicated, an SGLT2 inhibitor for many adults with type 2 diabetes and chronic kidney disease, finerenone or GLP-1–based therapy for selected patients, smoking cessation, appropriate nutrition, and avoidance of kidney-harming medicines. Kidney biopsy, dialysis, and transplantation are not automatically required.
Diabetes-related kidney disease is also called diabetic kidney disease, diabetic nephropathy, or diabetes-associated chronic kidney disease. It develops when diabetes and related conditions damage the kidneys’ filtering system over time.
The condition is important because kidney disease increases the risks of cardiovascular disease, medication-related hypoglycemia, anemia, fluid overload, and kidney failure. However, progression is not inevitable. Earlier diagnosis and treatment can preserve kidney function for many years.

What Is Diabetic Kidney Disease?
The kidneys contain approximately one million filtering units called nephrons. Inside each nephron, a cluster of tiny blood vessels called the glomerulus filters water and waste products while normally retaining most blood cells and proteins.
Diabetic kidney disease is diagnosed when abnormalities of kidney structure or function persist for at least three months and are attributed to diabetes. The most common findings are:
- Albumin leaking into the urine
- A reduced eGFR
- Both albuminuria and reduced filtration
Kidney disease can be present even when the eGFR is above 60 if albuminuria or another marker of kidney damage is persistent. Conversely, some people with diabetes develop a reduced eGFR without substantial albuminuria.
How Does Diabetes Damage the Kidneys?
The process is more complex than simple “thickening” of the glomerulus. Important mechanisms include:
- Glomerular hyperfiltration: early diabetes can increase pressure and blood flow inside the glomerulus.
- Damage to the filtration barrier: injury to endothelial cells, the basement membrane, and podocytes allows albumin to leak into the urine.
- Activation of hormonal pathways: the renin-angiotensin-aldosterone system can increase pressure within the glomerulus.
- Inflammation and fibrosis: persistent metabolic and hemodynamic stress can lead to scarring in glomeruli and the tubulointerstitial tissue.
- Blood-vessel disease: hypertension, smoking, and atherosclerosis can further reduce kidney health.
High glucose contributes to kidney damage, but glucose is not the only factor. Blood pressure, genetics, duration of diabetes, cardiovascular disease, smoking, obesity, kidney-toxic medicines, recurrent acute kidney injury, and social barriers to care also influence risk.
Who Is at Higher Risk?
- Longer duration of type 1 or type 2 diabetes
- Persistent glucose levels above the individualized target
- High blood pressure
- Albuminuria
- Cardiovascular disease or heart failure
- Smoking
- Obesity
- Family history of kidney failure
- Previous acute kidney injury
- Older age
- Diabetic retinopathy or neuropathy
- Use of medicines that can injure the kidneys
The old claim that nephropathy develops approximately 15 years after every diabetes diagnosis was inaccurate. It can appear at different times. Kidney disease may already be present when type 2 diabetes is first diagnosed, while screening for type 1 diabetes generally begins after five years unless there is another clinical reason to test earlier.
Symptoms of Diabetic Kidney Disease
Early diabetic kidney disease usually causes no symptoms. A person may feel well while urine albumin rises or eGFR falls. Waiting for swelling, nausea, or fatigue can delay diagnosis.
Possible symptoms in more advanced disease include:
- Swelling in the feet, ankles, legs, hands, or around the eyes
- Foamy urine caused by substantial protein loss
- Fatigue, weakness, reduced exercise tolerance, or shortness of breath from anemia
- Reduced appetite, nausea, vomiting, metallic taste, or unintentional weight loss
- Itching
- Muscle cramps
- Sleep problems
- Changes in urination
- Difficulty controlling blood pressure
- Confusion or drowsiness in severe kidney failure
These symptoms are not specific to kidney disease. Swelling may also be caused by heart failure, liver disease, venous problems, medication effects, or a blood clot. New swelling therefore needs medical assessment rather than self-treatment.
Emergency Warning
Seek urgent medical care for severe shortness of breath, chest pain, confusion, fainting, inability to keep fluids down, very little urine, rapidly worsening swelling, severe weakness, or suspected dangerously high potassium.
Call emergency services for collapse, severe breathing difficulty, seizure, new paralysis, or loss of consciousness.
The Two Essential Kidney Tests
1. Urine albumin-to-creatinine ratio
The UACR measures the amount of albumin in a spot urine sample relative to creatinine. It is more useful than relying only on a urine dipstick because it corrects partly for urine concentration.
| UACR | KDIGO Category | Interpretation |
|---|---|---|
| Below 30 mg/g | A1 | Normal to mildly increased |
| 30–300 mg/g | A2 | Moderately increased |
| Above 300 mg/g | A3 | Severely increased |
A single abnormal UACR does not always prove chronic kidney disease. Exercise, fever, urinary infection, menstruation, marked hyperglycemia, severe hypertension, and acute illness can temporarily increase albumin. The test is commonly repeated to confirm persistence.
2. Estimated glomerular filtration rate
The eGFR is calculated from a blood creatinine measurement and patient factors. It estimates how well the kidneys filter blood. A serum creatinine result alone can be misleading because age, muscle mass, diet, amputation, and other factors affect creatinine.
In some patients, clinicians may add cystatin C to improve eGFR accuracy—particularly when creatinine may not reflect muscle mass reliably or when a more accurate estimate would change treatment.
How often should testing be done?
- Type 2 diabetes: assess UACR and eGFR at least annually, beginning at diagnosis.
- Type 1 diabetes: assess at least annually after five years of diabetes, or earlier when clinically indicated.
- Established chronic kidney disease: monitor from one to four or more times per year depending on eGFR, albuminuria, rate of change, medicines, and clinical risk.
Understanding eGFR Stages
| Stage | eGFR, mL/min/1.73 m² | Description |
|---|---|---|
| G1 | 90 or higher | Normal or high filtration; CKD requires another persistent marker of kidney damage |
| G2 | 60–89 | Mildly decreased; not CKD by itself without another marker |
| G3a | 45–59 | Mildly to moderately decreased |
| G3b | 30–44 | Moderately to severely decreased |
| G4 | 15–29 | Severely decreased |
| G5 | Below 15 | Kidney failure |
The stage is not interpreted from eGFR alone. Risk is determined by the combination of eGFR, UACR, cause of kidney disease, rate of decline, cardiovascular disease, and other clinical factors.
Does Albumin in the Urine Always Mean Diabetic Kidney Disease?
No. Diabetes is a common cause, but urinary albumin can result from other kidney diseases, severe hypertension, infection, heart failure, exercise, fever, or temporary illness.
Features that may suggest a non-diabetic or additional kidney disease include:
- Blood or active sediment in the urine
- Rapidly rising albuminuria
- Sudden nephrotic syndrome
- Rapid eGFR decline
- Very short diabetes duration
- Systemic symptoms suggesting autoimmune or inflammatory disease
- Kidney findings that do not fit the overall diabetes history
Is a kidney biopsy routinely required?
No. A kidney biopsy is not routinely used to confirm typical diabetic kidney disease. It may be considered when the diagnosis is uncertain or another kidney disorder is suspected. The decision belongs to a nephrologist after reviewing blood tests, urine findings, imaging, diabetes duration, retinopathy, and the rate of change.
Treatment of Diabetic Kidney Disease
Modern treatment is not limited to “strict glucose control” or vasodilators. It combines several kidney- and cardiovascular-protective strategies.
1. Individualized glucose management
Improving glucose control helps prevent or slow diabetic kidney disease, but the safest goal depends on age, diabetes duration, CKD stage, cardiovascular disease, treatment burden, and hypoglycemia risk.
An HbA1c target below 7% is common for many nonpregnant adults when it can be achieved safely, but some people need a less stringent target. As kidney function falls, insulin and certain medicines may remain in the body longer, increasing hypoglycemia risk. Medication doses and glucose targets may need adjustment.
Learn more from our diabetes blood sugar guide and diabetes medication comparison.
2. Blood-pressure treatment
Blood-pressure control is one of the strongest ways to slow CKD progression and reduce cardiovascular events. ADA 2026 recommends a general target below 130/80 mmHg for people with diabetes and CKD when it can be reached safely. A lower systolic target may be considered for selected patients with high kidney or cardiovascular risk, but treatment must account for dizziness, falls, frailty, and medication side effects.
3. ACE inhibitors or ARBs
An ACE inhibitor or angiotensin receptor blocker is recommended for many nonpregnant people who have diabetes, hypertension, and albuminuria. These medicines lower systemic and intraglomerular pressure and can reduce albuminuria and CKD progression.
Examples of ACE inhibitors include lisinopril, ramipril, and enalapril. Examples of ARBs include losartan, valsartan, and irbesartan. “Sartans” are ARBs—not ACE inhibitors.
Important safety points:
- Do not combine an ACE inhibitor with an ARB.
- Check creatinine and potassium after starting or increasing the dose.
- A mild creatinine rise can occur and does not automatically require stopping treatment.
- These medicines are generally avoided during pregnancy.
- Persistent cough can occur with ACE inhibitors; angioedema is rare but urgent.
4. SGLT2 inhibitors
For many adults with type 2 diabetes and CKD, an SGLT2 inhibitor with proven benefit is recommended to reduce kidney-disease progression and cardiovascular events when eGFR is at least 20 mL/min/1.73 m².
Examples include empagliflozin, dapagliflozin, and canagliflozin. Their kidney and heart benefits are not explained only by glucose lowering.
Possible risks include genital yeast infection, dehydration, low blood pressure, and rare ketoacidosis that may occur without extremely high glucose. Patients need sick-day and perioperative instructions. These medicines are not used as a substitute for insulin in type 1 diabetes.
5. Finerenone
Finerenone is a nonsteroidal mineralocorticoid receptor antagonist. In adults with type 2 diabetes and CKD, it can reduce the risks of sustained eGFR decline, kidney failure, and cardiovascular events when used in appropriate patients.
It is generally considered for persistent albuminuria despite standard care, with adequate eGFR and acceptable potassium. Potassium and eGFR must be checked before treatment and monitored afterward because hyperkalemia can occur.
6. GLP-1 receptor agonists
GLP-1 receptor agonists can improve glucose control, support weight loss, and reduce cardiovascular risk with selected agents. They are useful when individualized glucose goals are not met with metformin and an SGLT2 inhibitor, when those medicines cannot be used, or when cardiovascular and weight-related benefits are priorities.
Some GLP-1–based therapies also have evidence of kidney benefit, especially through reductions in albuminuria and cardiovascular events.
7. Lipids, smoking, and cardiovascular risk
Chronic kidney disease greatly increases cardiovascular risk. Statin therapy, smoking cessation, physical activity when safe, weight management, and treatment of heart failure or vascular disease may be as important as glucose lowering.
8. Nutrition for diabetic kidney disease
There is no single kidney diet for every patient. Needs change with eGFR, UACR, potassium, phosphorus, blood pressure, edema, dialysis status, appetite, and malnutrition risk.
General principles may include:
- Use a moderate protein intake rather than a high-protein diet when not on dialysis.
- Reduce excessive sodium, especially with hypertension or swelling.
- Choose minimally processed foods more often.
- Adjust potassium or phosphorus only when blood tests and the clinical situation require it.
- Avoid unregulated herbal “kidney cleanses.”
- Work with a renal dietitian when CKD is moderate, advanced, or nutritionally complex.
A blanket very-low-carbohydrate or high-protein diet may be unsafe in some people with CKD. Meal planning should balance glucose management with kidney protection. See our diabetes foods guide.
9. Avoid preventable kidney injury
Ask before using nonsteroidal anti-inflammatory drugs such as ibuprofen, naproxen, or diclofenac—especially during dehydration or while taking a diuretic, ACE inhibitor, or ARB. Review contrast imaging, supplements, proton-pump inhibitors, antibiotics, and over-the-counter products with the healthcare team.
Do not stop an indicated medicine merely because it is cleared by the kidneys. Many medicines can be used safely with the correct dose and monitoring.
Anemia and Other CKD Complications
The kidneys produce erythropoietin, a hormone that helps the bone marrow make red blood cells. As CKD advances, reduced erythropoietin can contribute to anemia. However, iron deficiency, blood loss, inflammation, vitamin B12 deficiency, and other causes must also be assessed.
Advanced CKD may also cause:
- High potassium
- Metabolic acidosis
- Mineral and bone disorder
- Fluid overload
- Malnutrition
- Medication accumulation
- Higher hypoglycemia risk
These complications require laboratory monitoring and individualized treatment. Erythropoiesis-stimulating therapy is not started simply because a patient feels tired.
When Should a Nephrologist Be Involved?
Referral or co-management may be appropriate when there is:
- Continuously rising UACR
- Continuously falling eGFR
- eGFR below 30 mL/min/1.73 m²
- Uncertain cause of kidney disease
- Rapid progression
- Resistant hypertension
- Persistent high potassium
- Severe albuminuria or nephrotic syndrome
- Anemia, acidosis, or mineral-bone complications that are difficult to manage
- Need for kidney-failure education, dialysis planning, or transplant evaluation
Does Diabetic Kidney Disease Always Lead to Dialysis?
No. Most people with diabetes and kidney disease do not progress to kidney failure. Modern treatment can slow or sometimes stabilize the decline.
Dialysis or transplantation is considered when kidney function becomes severely reduced and symptoms, fluid overload, potassium, acidosis, nutrition, or other complications can no longer be managed safely. Decisions are not based on one creatinine or eGFR result alone.
Dialysis is not merely a temporary bridge for every patient. Some people remain on dialysis long term, some receive a kidney transplant, and some choose conservative kidney management based on health status and personal goals.
Does Having One Kidney Cause a False Diabetes Reading?
Having one functioning kidney does not by itself create a false fasting glucose, random glucose, or home glucose-meter result. Diabetes is still diagnosed using standard laboratory criteria.
However, advanced kidney disease can affect the interpretation of HbA1c. Anemia, shortened red-cell lifespan, erythropoietin treatment, blood transfusion, iron therapy, and hemodialysis can make HbA1c less reliable. When HbA1c does not match finger-stick or CGM readings, the clinician may use glucose data, fructosamine, glycated albumin, or another approach.
A solitary kidney also does not automatically mean kidney failure. Many people live normally with one healthy kidney, but they should monitor blood pressure, eGFR, urine albumin, and avoid preventable kidney injury.
Important: The old fasting range of 64.8–104.4 mg/dL was not an appropriate general recommendation. For adults without diabetes, fasting plasma glucose is generally considered normal at 70–99 mg/dL. People who already have diabetes need individualized targets, especially when CKD or hypoglycemia risk is present.
Doctor’s Note
The most important practical message is that diabetic kidney disease is usually found through testing, not symptoms. I ask patients to know both kidney numbers: UACR and eGFR. Then I review glucose, blood pressure, potassium, medicines, cardiovascular risk, smoking, nutrition, and the trend over time. One abnormal result is important, but the direction of repeated results is even more useful.
Most Asked Questions
Can diabetic kidney disease be reversed?
Established scarring may not fully reverse, but albuminuria can decrease and progression can slow substantially. Early treatment offers the best opportunity to preserve kidney function.
What is the earliest sign?
Persistent albumin in the urine is a common early finding, but some patients first show a falling eGFR. This is why both tests are required.
Can I have kidney disease with normal creatinine?
Yes. Serum creatinine can remain within the laboratory reference range despite early kidney damage. eGFR and UACR provide more useful information.
Should everyone with diabetes take an ACE inhibitor?
No. ACE inhibitors and ARBs are particularly important for people with hypertension and albuminuria or reduced eGFR, but treatment depends on blood pressure, pregnancy, potassium, kidney function, and tolerance.
Do SGLT2 inhibitors protect the kidneys even if glucose is controlled?
In appropriate adults with type 2 diabetes and CKD, kidney and cardiovascular benefits can occur independently of a large glucose-lowering effect.
Does foamy urine mean kidney disease?
Persistent foam may suggest protein in the urine, but dehydration, urine speed, and cleaning products can also cause bubbles. A UACR test is needed.
Can herbs improve kidney blood flow?
No herbal product should be used as a substitute for ACE inhibitors, ARBs, SGLT2 inhibitors, finerenone, or other prescribed treatment. Some herbs can worsen kidney function or alter potassium.
Educational safety note: This page provides general education and does not diagnose kidney disease or select a medicine, dose, protein intake, potassium limit, or dialysis plan for an individual. Do not stop diabetes or blood-pressure medicine without medical advice.
Related Questions
- What Is the Link Between Lisinopril, Diabetes, and Kidney Protection?
- Will Lowering Blood Sugar Reduce Swelling?
- Why Can HbA1c and Finger-Prick Results Disagree?
Related Resources
- Diabetes Complications and Prevention
- Diabetes Medicines: Benefits and Side Effects
- Type 2 Diabetes Information
- Diabetes Blood Sugar Levels
- HbA1c Explained
- Diabetes Foods and Meal Planning
References
- American Diabetes Association. Chronic Kidney Disease and Risk Management: Standards of Care in Diabetes—2026.
- KDIGO. Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease—2024.
- NIDDK. Diabetic Kidney Disease.
- NIDDK. Quick Reference on UACR and GFR.
- U.S. FDA. Finerenone Prescribing Information.
- NIDDK. The A1C Test and Conditions That Affect Accuracy.