- Home
- Diabetes Complications
- What to Do If a Person With Diabetes Has a Seizure
Diabetic Seizures
A seizure in a person with diabetes is an emergency. Severe low blood sugar is one possible cause, but I do not want you to assume that every seizure is “just diabetes.” Stroke, infection, head injury, epilepsy, medicines, alcohol or drugs, and abnormal sodium or other electrolytes can also cause a seizure and require urgent assessment.
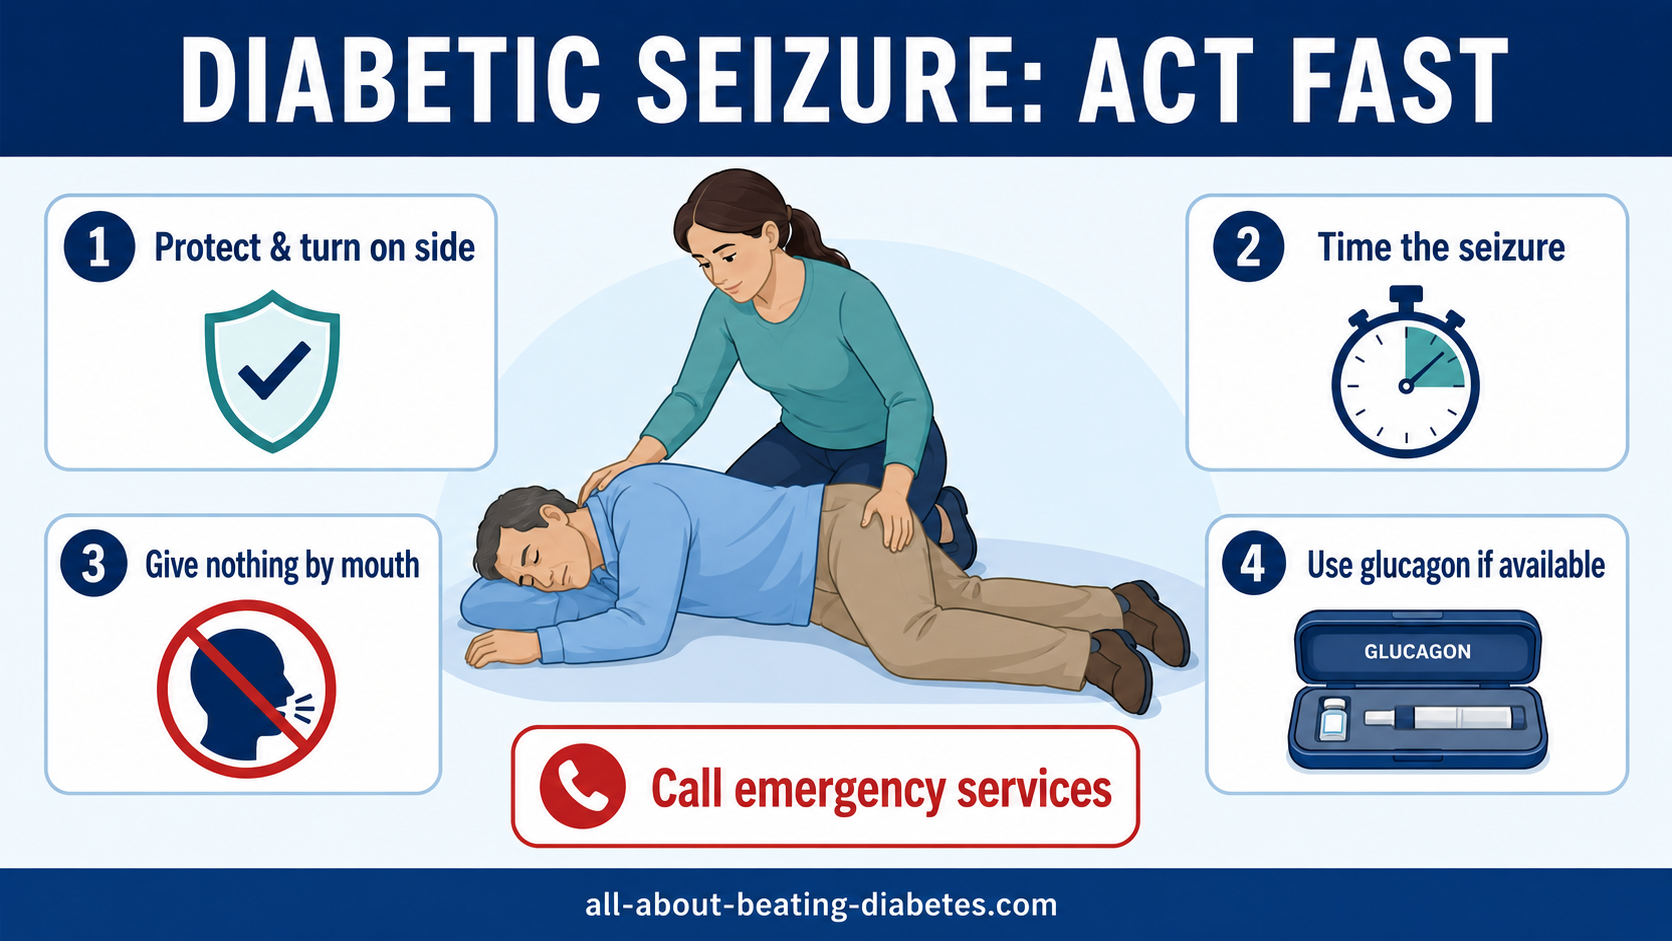
A diabetes-related seizure is most often associated with severe hypoglycemia, especially in someone using insulin or a medicine that can cause low glucose. Severe hyperglycemic emergencies can also affect the brain. If someone is seizing, protect them from injury, turn them gently onto their side when possible, time the seizure, give nothing by mouth, use prescribed glucagon if severe hypoglycemia is suspected and it is available, and call emergency services. Do not restrain the person and never rub honey, syrup, frosting, glucose gel, or any other substance inside the mouth.
Emergency: What to Do During a Seizure
- Call your local emergency number—especially for a first seizure, loss of consciousness in a person with diabetes, a seizure lasting 5 minutes or more, repeated seizures, injury, pregnancy, trouble breathing, or failure to wake normally.
- Keep the person safe. Ease them to the floor if needed, remove hard or sharp objects, cushion the head, loosen tight clothing around the neck, and remove eyeglasses.
- Turn them gently onto one side with the mouth pointing downward when you can do so safely. This helps keep the airway clear.
- Time the seizure. Tell the emergency team when it started and what you observed.
- Give nothing by mouth. Do not give food, drink, tablets, gel, honey, syrup, or frosting until the person is fully awake and can swallow safely.
- Use prescribed glucagon if available and severe low glucose is suspected. Follow the product instructions or the person’s emergency plan. Do not delay the emergency call.
- Stay with the person until emergency help arrives and they are breathing and responding normally.
Do not hold the person down, stop the movements, or put fingers or objects between the teeth. A person cannot swallow their tongue.

What Is a Diabetic Seizure?
A seizure is a temporary episode of abnormal electrical activity in the brain. It can change awareness, behavior, sensation, muscle tone, or movement. Some seizures cause loss of consciousness, stiffness, and rhythmic jerking. Others may cause staring, confusion, repeated automatic movements, or abnormal sensations.
“Diabetic seizure” is not a separate medical diagnosis. It usually means that a person with diabetes has a seizure during a serious glucose disturbance. Doctors call a seizure caused by an immediate metabolic problem an acute symptomatic seizure. One event does not automatically mean the person has epilepsy, but the cause still must be investigated.
Can Low or High Blood Sugar Cause a Seizure?
Severe hypoglycemia
For many people with diabetes, glucose below 70 mg/dL (3.9 mmol/L) is low, and below 54 mg/dL (3.0 mmol/L) is clinically significant. Level 3 severe hypoglycemia is defined by altered mental or physical functioning that requires help from another person; it is not defined by one exact meter number.
As glucose available to the brain falls, confusion, unusual behavior, inability to swallow, loss of consciousness, seizure, coma, or death may occur.
Severe hyperglycemic emergencies
Ordinary high glucose does not usually cause a seizure by itself. Seizures may occur during a diabetic ketoacidosis (DKA) or hyperosmolar hyperglycemic state (HHS), particularly when there is profound dehydration, very high blood concentration, electrolyte disturbance, or another neurological problem.
These are hospital emergencies—not conditions to correct rapidly at home with extra insulin unless a clinician-directed plan specifically tells you what to do.
Common reasons severe hypoglycemia happens
- Too much insulin, the wrong insulin, or a dosing or timing error
- Insulin taken for carbohydrate that was not eaten or was vomited
- A delayed or missed meal
- More physical activity than expected, including delayed lows after exercise
- Alcohol, especially without enough food
- Kidney or liver disease that changes how medicine is cleared
- Recent weight loss or reduced food intake without medicine adjustment
- Sulfonylureas or meglitinides, alone or combined with other glucose-lowering treatment
- Reduced awareness of early hypoglycemia symptoms
Review the guide to blood sugar 45–69 mg/dL and the emergency guide to blood sugar below 54 mg/dL for treatment details when the person is conscious.
What Can a Seizure Look Like?
Seizures do not all look the same. Possible signs include:
Convulsive signs
- Sudden loss of awareness or collapse
- Body stiffening
- Repeated jerking of the arms or legs
- Abnormal breathing or bluish color
- Saliva, tongue injury, or loss of bladder control
Less obvious signs
- Staring and not responding
- Sudden confusion or unusual behavior
- Lip smacking, picking at clothes, or repeated movements
- Abnormal smell, taste, fear, visual change, or déjà vu
- Twitching or altered sensation on one side
Afterward, the person may be sleepy, confused, weak, sore, or have a headache. This recovery period can last minutes or longer. New one-sided weakness, speech difficulty, severe headache, persistent confusion, chest pain, or breathing trouble must be treated as an emergency because they may indicate stroke, injury, or another serious condition.
First Aid: What You Should and Should Not Do
| Do | Do not | Why |
|---|---|---|
| Clear the area, protect the head, loosen neckwear, and remove eyeglasses. | Do not restrain the person or try to stop the movements. | Restraint can cause injury to the person and helper. |
| Turn the person onto one side when safe. | Do not leave them flat on the back if you can safely reposition them. | Side positioning helps secretions or vomit drain and supports the airway. |
| Time the seizure and observe what happens. | Do not rely on memory alone or assume it “was only a low.” | Duration and observed features help emergency clinicians assess the event. |
| Use prescribed glucagon when severe hypoglycemia is suspected and follow the instructions. | Do not put honey, syrup, frosting, glucose gel, food, drink, pills, fingers, or objects in the mouth. | An unresponsive or seizing person can choke or inhale material into the lungs. |
| Call emergency services and stay with the person. | Do not send a confused person home alone or allow them to drive. | A seizure may recur, and the underlying cause may still be dangerous. |
Should you check blood glucose during the seizure?
If another helper can use a meter or read the CGM without restraining the person or delaying safety steps, the result may be useful. However, CGM values can lag behind blood glucose, and a reading does not replace emergency care. Treat suspected severe hypoglycemia with prescribed glucagon if available, and give the reading and recent trend to the emergency team.
The home diabetes testing-supplies guide explains how to keep a backup meter available when CGM symptoms and readings do not match.
When and How Is Glucagon Used?
Glucagon is an emergency medicine that raises glucose by signaling the liver to release stored glucose. Depending on the country and prescription, it may be available as a nasal powder, autoinjector, prefilled syringe, or kit that must be mixed before injection.
- Use it for suspected severe hypoglycemia when the person cannot safely swallow, is unconscious, or is having a seizure, according to the product label and emergency plan.
- A caregiver—not the affected person—usually gives glucagon during severe hypoglycemia.
- Call emergency services after giving it. Turn the person onto one side because vomiting can occur.
- Do not force food or drink. Once the person is fully awake and can swallow safely, follow the emergency plan for fast carbohydrate and a longer-acting snack or meal.
- Check the expiration date and teach family, coworkers, teachers, or caregivers where it is and how to use it before an emergency happens.
Current ADA guidance recommends glucagon for people taking insulin or at high risk of hypoglycemia, with education for the people likely to help them. Ask your clinician which ready-to-use option is available and appropriate for you.
What Happens After the Seizure?
A first seizure, a seizure with loss of consciousness in a person with diabetes, or a suspected severe hypoglycemic seizure needs urgent medical assessment. The emergency team may check glucose, electrolytes, kidney and liver function, oxygen, infection markers, heart rhythm, medicines, toxic exposures, and signs of injury or stroke. Brain imaging, an EEG, or neurological review may be needed depending on the situation.
Hospital treatment depends on the cause. Intravenous glucose may be needed for hypoglycemia. DKA or HHS requires carefully monitored fluids, insulin, electrolytes, and treatment of the trigger. Antiseizure medication may or may not be needed; it is unsafe to promise that every glucose-related seizure requires—or never requires—this treatment.
After a seizure, do not drive, swim alone, work at height, operate dangerous machinery, or resume another high-risk activity until a clinician has assessed the event and advised you according to local rules.
Information to record for the medical team
- Start time and approximate duration
- Glucose reading and CGM trend, if available
- Whether awareness was lost and which body parts moved
- Recent insulin or medicine doses and timing
- Food, alcohol, exercise, illness, vomiting, or missed meals
- Any fall, head injury, pregnancy, or recent medicine change
- How and when glucagon or another treatment was given
Can a Diabetes-Related Seizure Happen During Sleep?
Severe hypoglycemia can occur overnight, especially after late exercise, alcohol, missed food, an excessive evening insulin dose, or a change in kidney function or insulin needs. Some people sleep through early warning symptoms.
Possible clues such as damp sheets, nightmares, headache, unusual fatigue, confusion on waking, or unexplained CGM data are not specific enough to diagnose a seizure. If you suspect overnight severe hypoglycemia, contact your diabetes team promptly. Recurrent lows require treatment review rather than simply adding a bedtime snack for everyone.
Helpful prevention tools
- CGM low alerts set to a useful, audible level
- Urgent-low and share/follow alerts when appropriate
- Automated insulin-suspension or hybrid closed-loop features, if available
- A charged receiver or phone placed where alerts can be heard
Plan review
- Evening basal or long-acting insulin
- Dinner and bedtime insulin timing
- Late activity and alcohol
- Kidney function, weight change, or reduced appetite
How Can Severe Hypoglycemia and Seizures Be Prevented?
Not every seizure is preventable, but severe hypoglycemia risk can often be reduced. After any level 2 low below 54 mg/dL or a level 3 event requiring help, the diabetes plan should be reviewed.
- Identify the cause. Review insulin, tablets, meals, activity, alcohol, illness, kidney function, and recent weight change with your clinician.
- Use technology appropriately. CGM with urgent-low alerts and automated insulin-delivery features can reduce risk for suitable users, but alarms and backup plans still matter.
- Keep both kinds of rescue treatment. Carry fast carbohydrate for an awake person and prescribed glucagon for a person who cannot self-treat.
- Train the people around you. They should know where glucagon is, how to give it, when to call emergency services, and why nothing goes in the mouth during a seizure.
- Wear medical identification. A bracelet, necklace, wallet card, or phone medical ID can help responders recognize diabetes and medicines.
- Address reduced awareness. If you no longer feel early low-glucose symptoms, tell your diabetes team. Temporary relaxation of targets and structured education may help restore awareness.
- Follow sick-day and ketone plans. Severe high-glucose emergencies also require prevention, especially in type 1 diabetes and during vomiting or illness.
Learn the wider warning signs in What Blood Sugar Level Is Dangerous?, and see how loss of consciousness can occur in the guide to diabetic coma.
Doctor’s Note
Frequently Asked Questions About Diabetic Seizures
At what blood sugar level can a seizure happen?
There is no single glucose number at which every person will have a seizure. Glucose below 54 mg/dL (3.0 mmol/L) is clinically significant, but severe hypoglycemia is defined by needing help because thinking or physical function is impaired. Treat the symptoms and situation, not only the number.
Should I put honey or syrup in the mouth during a seizure?
No. Never put honey, syrup, frosting, gel, food, drink, fingers, or an object in the mouth of someone who is seizing or unable to swallow. They may choke or inhale it. Use prescribed glucagon if available and call emergency services.
Can high blood sugar cause a seizure?
Seizures can occur during severe hyperglycemic emergencies, particularly HHS, when dehydration, hyperosmolality, electrolyte disturbance, or another neurological problem affects the brain. A routine high reading alone does not usually cause a seizure. Seizure with high glucose needs emergency evaluation.
Is a glucose-related seizure the same as epilepsy?
Not necessarily. A seizure caused by an immediate metabolic disturbance may be an acute symptomatic seizure. Epilepsy involves a tendency toward recurrent unprovoked seizures. A clinician must evaluate the event before deciding the diagnosis.
Can I use glucagon while the person is convulsing?
If severe hypoglycemia is suspected and prescribed glucagon is available, a trained helper can give it according to the product instructions and emergency plan. Do not restrain the person, put anything in the mouth, or delay calling emergency services.
Should I use the 15–15 rule after a seizure?
Only when the person is fully awake, cooperative, and able to swallow safely. During seizure, unconsciousness, or unsafe swallowing, use glucagon if available and seek emergency help. Follow the emergency team’s instructions afterward.
Does every diabetic seizure require an ambulance?
A seizure with loss of consciousness in a person with diabetes warrants emergency help, especially if it is the first seizure, lasts 5 minutes or more, repeats, causes injury, occurs during pregnancy or in water, or the person has trouble breathing or waking. If someone has a known seizure disorder and a clinician-written plan, follow that plan—but suspected severe hypoglycemia still requires immediate treatment.
Can someone have a seizure overnight without knowing?
It is possible, but morning headache, sweating, nightmares, or fatigue do not prove it. Review meter or CGM data and seek medical assessment, especially after an unexplained injury, confusion, tongue injury, or suspected severe low.
Will I need antiseizure medicine after a hypoglycemic seizure?
Not always, but the decision depends on the cause, examination, recurrence risk, EEG or imaging findings, and whether another seizure disorder is present. Do not start or stop antiseizure medicine without medical guidance.
Can a person drive after a diabetes-related seizure?
Do not drive until a clinician has assessed the event and cleared you according to local licensing rules. Severe hypoglycemia and seizures can recur, and driving restrictions differ by country and cause.
Related Questions
- What complications can occur with blood sugar of 455 mg/dL?
- What do high and low sugar levels mean with high blood pressure?
- Is blood sugar 190 mg/dL after eating dangerous?
Related Resources
- Dangerous blood sugar levels
- Blood sugar 45–69 mg/dL
- Blood sugar under 54 mg/dL: severe hypoglycemia
- Diabetic coma
- Diabetic ketoacidosis
- Short- and long-term diabetes complications
References
- American Diabetes Association. Glycemic Goals, Hypoglycemia, and Hyperglycemic Crises: Standards of Care in Diabetes—2026.
- Centers for Disease Control and Prevention. First Aid for Seizures.
- National Institute of Diabetes and Digestive and Kidney Diseases. Low Blood Glucose (Hypoglycemia).
- Umpierrez GE, et al. Hyperglycemic Crises in Adults With Diabetes: A Consensus Report. Diabetes Care. 2024.
- Centers for Disease Control and Prevention. Types of Seizures.