Quick answer
Diabetes-related foot symptoms may include tingling, burning, numbness, pain, dry or cracked skin, swelling, color or temperature changes, calluses, blisters, slow-healing wounds, and changes in foot shape. Some serious problems cause little or no pain because nerve damage reduces sensation. Check both feet every day and seek prompt medical care for any wound, spreading redness, drainage, dark skin, or a red, hot, swollen foot.
What can happen to your feet when you have diabetes?
Diabetes can affect the nerves, blood vessels, skin, immune response, and shape of your feet. These changes do not happen only after 20 years. Risk generally increases with longer diabetes duration and glucose levels that remain above your target, but foot problems can occur earlier—especially when neuropathy, poor circulation, kidney disease, smoking, previous ulcers, or foot deformities are present.
Peripheral neuropathy can reduce your ability to feel pain, heat, cold, or pressure. A stone in your shoe, blister, burn, or ingrown nail may therefore go unnoticed. Peripheral artery disease can reduce blood flow and make wounds more difficult to heal. Pressure from calluses or poorly fitting footwear can then contribute to skin breakdown and an ulcer.
A small injury does not automatically become an ulcer, gangrene, or amputation. Early recognition and appropriate treatment can prevent many serious outcomes. Gangrene means tissue has died because of severely reduced blood flow, infection, or both; it requires urgent specialist care, but amputation is not automatically the only treatment for every diabetic foot problem.
Common diabetes foot symptoms
1. Tingling or burning
“Pins and needles,” burning, stabbing, or electric-shock sensations may suggest peripheral neuropathy. Symptoms may be worse at night.
2. Numbness
Reduced sensation may make it difficult to notice pressure, temperature, cuts, or blisters. Numbness can be dangerous even when it is not painful.
3. Foot or leg pain
Nerve damage can cause burning or shooting pain. Cramping in the calf, thigh, or buttock during walking may suggest reduced circulation. Arthritis, injuries, and other conditions can also cause pain.
4. Swelling
Swelling is not always caused directly by diabetes. Possible causes include infection, injury, vein problems, heart or kidney disease, medication effects, or Charcot foot. Sudden or one-sided swelling needs assessment.
5. Skin and temperature changes
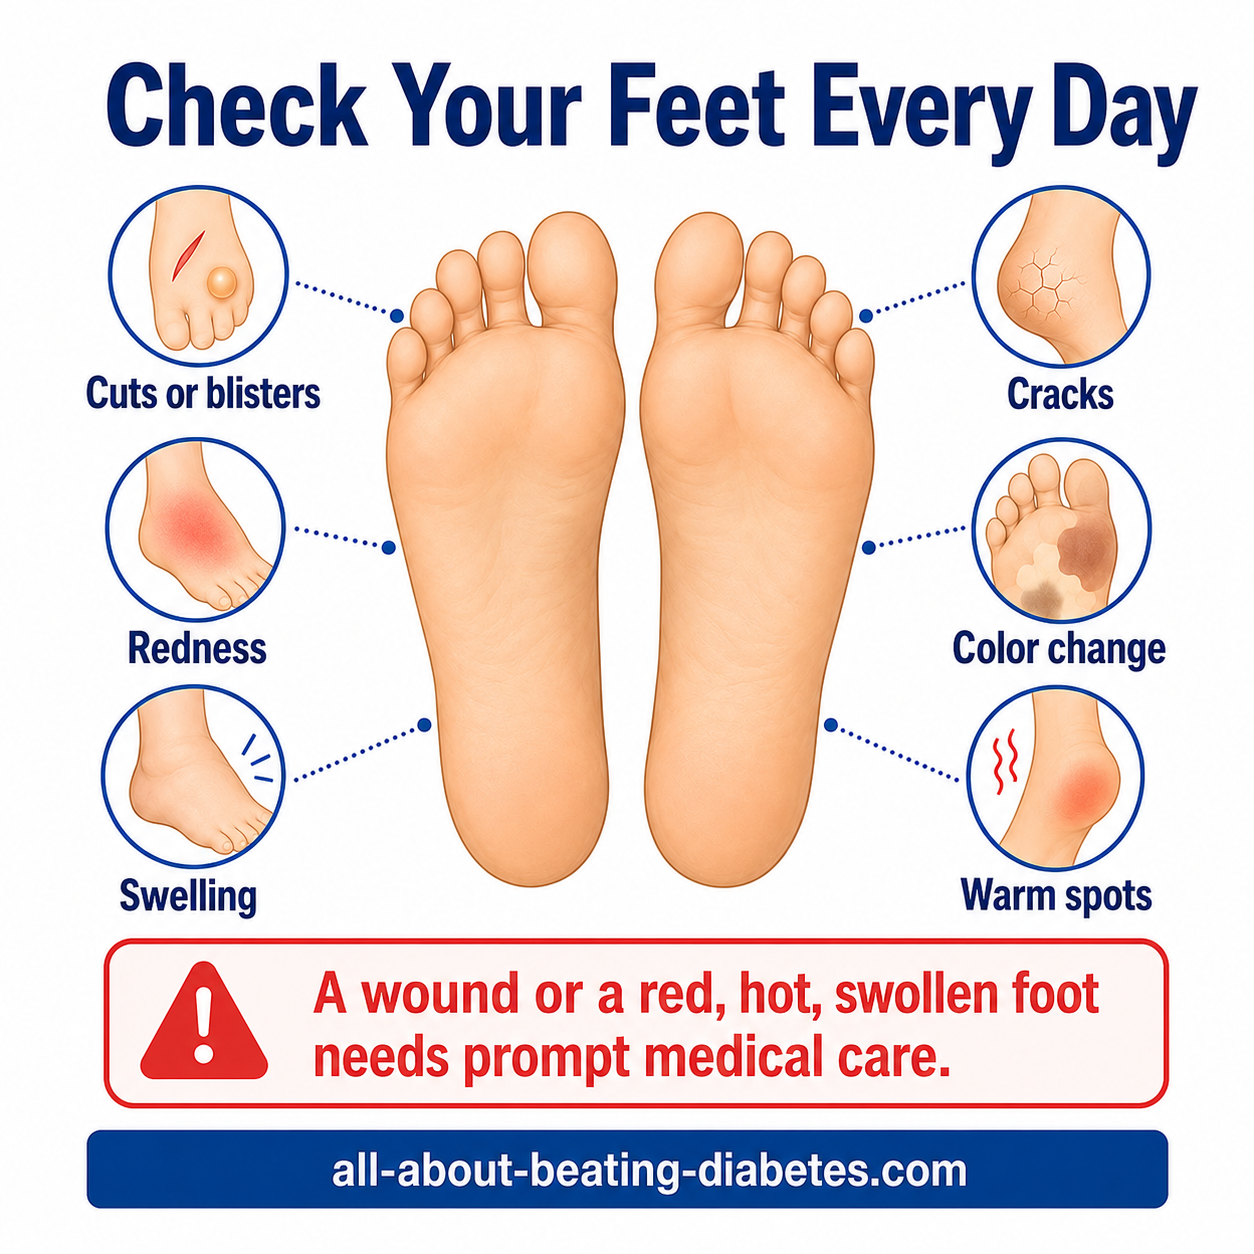
Watch for redness, unusual warmth, a cold foot, pale or blue skin, darkening, shiny skin, hair loss, dryness, and cracks. Compare one foot with the other.
6. Calluses and corns
Thickened skin can identify areas of repeated pressure. Do not cut a callus or use medicated corn removers yourself, particularly if sensation or circulation is reduced.
7. Blisters, cuts, and ulcers
A foot ulcer is an open sore or break in the skin. It may not hurt. Drainage on a sock, odor, redness, or swelling may be the first warning.
8. Nail and fungal problems
Thick or discolored nails, an ingrown toenail, athlete’s foot, itching, peeling, or cracked skin between the toes should be treated appropriately before the skin barrier worsens.
9. Slow healing or infection
A wound that is not improving, spreading redness, pus, drainage, odor, warmth, or fever may indicate infection and needs prompt medical attention.
10. Change in foot shape
New flattening, a prominent bone, toe deformity, or a red, warm, swollen foot may indicate Charcot neuroarthropathy or another structural problem.

When diabetes foot symptoms need urgent care
Contact a clinician or foot-care service promptly for:
- any open wound, ulcer, worsening blister, or drainage
- spreading redness, warmth, swelling, pus, odor, fever, or chills
- a red, hot, swollen foot—even when there is little pain or no wound
- black, blue, very pale, or suddenly cold skin
- a new change in foot shape or inability to bear weight
- sudden one-sided leg or foot swelling
A red, hot, swollen foot may represent infection or acute Charcot neuroarthropathy. Reduce weight-bearing and obtain urgent assessment. Sudden swelling accompanied by chest pain or shortness of breath requires emergency care.
What happens during a diabetic foot examination?
Everyone with diabetes should receive a comprehensive foot evaluation at least once a year. Your clinician should inspect the skin and nails, look for deformities and pressure areas, check pulses and circulation, and assess sensation. A 10-gram monofilament test is commonly combined with another test such as vibration, pinprick, or temperature sensation.
If you have loss of protective sensation, a previous ulcer or amputation, poor circulation, kidney disease, or a foot deformity, you may need examination at every visit and ongoing podiatry or specialist care. Vascular studies, X-rays, blood tests, wound cultures, or other investigations are ordered according to the findings—not automatically for every symptom.
How to protect your feet every day
- Inspect both feet daily. Use a mirror or ask someone you trust for help if you cannot see the soles.
- Wash gently. Use warm—not hot—water. Do not soak your feet. Dry carefully, especially between the toes.
- Moisturize dry skin. Apply lotion to the tops and bottoms, but not between the toes where excess moisture can encourage infection.
- Protect your feet. Never walk barefoot, even indoors. Check inside your shoes for stones, rough seams, or other objects.
- Choose well-fitting shoes and clean socks. Specialized footwear is usually reserved for people with higher ulcer risk, deformity, calluses, poor circulation, or previous ulcers—not automatically for everyone with diabetes.
- Do not treat nails, corns, or calluses aggressively. Ask a clinician or podiatrist for help if vision, circulation, sensation, or flexibility is reduced.
- Avoid burns and cold injury. Do not use heating pads, hot-water bottles, or ice directly on feet with reduced sensation.
- Manage your overall risk. Follow your individualized plan for glucose, blood pressure, cholesterol, physical activity, medication, and smoking cessation.
Physical activity is valuable, but do not force yourself to walk on an open wound or a red, hot, swollen foot. Ask your healthcare team about safe non-weight-bearing activity until the problem has been evaluated.
For a practical routine, read Diabetic Feet Care: Practical Tips. If you have burning, tingling, electric-shock pain, or numbness, see Diabetic Nerve Pain.
Related questions
Can reducing blood sugar make foot swelling go away?
It depends on the cause. Glucose management protects your feet over time, but swelling may come from infection, injury, circulation, veins, heart or kidney disease, medication, or Charcot foot. Read the full answer: Does reducing blood sugar reduce foot swelling?
Can diabetic foot problems occur without pain?
Yes. Neuropathy may reduce protective sensation, so a blister, ulcer, infection, or Charcot foot may cause surprisingly little pain.
Does every person with diabetes need diabetic shoes?
No. Shoes should fit well and protect your feet. Therapeutic footwear is especially important for people at high risk because of sensory loss, deformity, calluses, poor circulation, previous ulcers, or amputation.
Should I wait to see whether a small wound heals?
No. If you have diabetes—particularly neuropathy or poor circulation—contact your clinician promptly about a foot wound rather than relying on home treatment.