- Home
- Diabetes Answers and Tools: Doctor-Reviewed Learning Center
- normal adult levels
Normal Blood Sugar Levels for Adults: What Changes With Age?
If you have checked your blood sugar and wondered whether the number is normal, the first thing I would ask is not only “What was the number?” I would also ask when you tested, whether you had eaten, whether the result came from a laboratory or a home glucose meter, and whether you already have diabetes.
One source of confusion is age. Many people search for a different “normal blood sugar” for adults in their 40s, 50s, 60s or 70s. However, the laboratory thresholds used to identify normal glucose, prediabetes and diabetes do not simply increase because you get older.
What can change with age is the treatment target for someone who already has diabetes. An older adult who is healthy and independent may have a different treatment goal from someone of the same age who has frailty, several serious medical conditions or frequent low blood sugar.
Quick Answer: Normal Adult Blood Sugar Levels
For a nonpregnant adult who has not been diagnosed with diabetes, commonly used laboratory diagnostic ranges include:
- Fasting plasma glucose: 99 mg/dL or below is within the normal diagnostic range.
- HbA1c: below 5.7% is within the normal diagnostic range.
- 2-hour 75-g oral glucose tolerance test: 139 mg/dL or below is within the normal diagnostic range.
These are diagnostic laboratory thresholds. They should not be confused with the blood sugar targets used by people who already have diabetes.
Do Normal Blood Sugar Levels Change With Age?
This is one of the most common questions I receive.
Aging can affect insulin sensitivity, muscle mass, physical activity, kidney function, medication use and the risk of both high and low blood sugar. However, this does not mean that prediabetes or diabetes diagnostic thresholds are simply raised for an older person.
| Adult Group | How Blood Sugar Should Be Interpreted |
|---|---|
| Adults 18–64 without diabetes | Standard laboratory criteria are used for fasting glucose, HbA1c and the 2-hour OGTT. |
| Adults 65+ without diabetes | The diagnostic thresholds for prediabetes and diabetes do not automatically become higher because of age. |
| Healthy older adults with diabetes | Treatment targets can often remain relatively close to those used in younger adults when this can be achieved safely. |
| Older adults with several illnesses, frailty or functional limitations | Treatment goals may be less stringent, especially when tighter control would increase the risk of hypoglycemia or treatment burden. |
| Older adults with very complex or poor health | Avoiding hypoglycemia and symptomatic high blood sugar may be more important than trying to reach a strict HbA1c number. |
Normal, Prediabetes and Diabetes Blood Sugar Ranges
Doctors use specific laboratory tests to diagnose prediabetes and diabetes. The meaning of the result depends on which test was performed.
| Test | Normal Range | Prediabetes Range | Diabetes Range |
|---|---|---|---|
| Fasting plasma glucose | 99 mg/dL or below | 100–125 mg/dL | 126 mg/dL or higher |
| HbA1c | Below 5.7% | 5.7–6.4% | 6.5% or higher |
| 2-hour 75-g OGTT | 139 mg/dL or below | 140–199 mg/dL | 200 mg/dL or higher |
| Random plasma glucose | Not used to define a normal screening range | Not used to diagnose prediabetes | 200 mg/dL or higher with classic symptoms of hyperglycemia or hyperglycemic crisis |
Diagnostic thresholds shown above apply to nonpregnant adults. In the absence of unequivocal hyperglycemia, a result in the diabetes range generally requires confirmation with repeat testing or another appropriate diagnostic test.
If you would like a fuller explanation of the different diagnostic tests, read: Blood Tests for Diabetes: What Each Test Means .
Age matters when I think about the safest treatment target. It does not mean that a fasting laboratory glucose of 126 mg/dL becomes “normal” simply because a person is 70 or 80 years old.
Blood Sugar Targets for Adults Who Already Have Diabetes
Once diabetes has been diagnosed, the question changes. We are no longer asking only whether a laboratory result meets a diagnostic threshold. We are deciding what glucose range is safe and realistic for that particular person.
For many nonpregnant adults with diabetes, commonly used targets include:
| Measurement | Common Target for Many Adults With Diabetes |
|---|---|
| Before meals | 80–130 mg/dL (4.4–7.2 mmol/L) |
| Peak post-meal glucose | Less than 180 mg/dL (10.0 mmol/L), generally measured 1–2 hours after the beginning of the meal |
| HbA1c | Often below 7% when appropriate and safely achievable |
| Low blood sugar alert level | Below 70 mg/dL (3.9 mmol/L) |
These are general treatment goals, not personal prescriptions. Your doctor may recommend different targets depending on your medications, risk of hypoglycemia, diabetes duration, kidney disease, heart disease, pregnancy, cognitive function or other health conditions.
For a more detailed explanation of treatment goals, see: Acceptable Blood Glucose Levels for People With Diabetes .
Blood Sugar Targets After Age 65
For adults over 65 who have diabetes, I do not recommend choosing an HbA1c target from age alone. Two people who are both 75 years old may have completely different health situations.
According to the 2026 Standards of Care in Diabetes, many otherwise healthy older adults with good cognitive and functional status may have an HbA1c goal of approximately 7.0–7.5%, depending on individual health and treatment considerations.
For older adults with more complex health, significant functional or cognitive limitations, frailty or severe comorbidities, a less stringent goal such as below 8.0% may sometimes be appropriate.
In people with very complex or poor health, the priority may shift away from relying heavily on HbA1c and toward preventing hypoglycemia and symptomatic hyperglycemia.
A Home Glucose Reading Is Not the Same as a Diagnostic Laboratory Test
This distinction is very important.
A finger-stick glucose meter is useful for monitoring blood sugar at home. It can help you see patterns, detect possible low blood sugar and understand how meals, exercise, medicines, illness and stress affect your readings.
However, a home glucose meter by itself is not the standard method used to diagnose diabetes.
If your home readings repeatedly appear high, your doctor may recommend laboratory testing such as:
- fasting plasma glucose;
- HbA1c;
- a 75-g oral glucose tolerance test; or
- random plasma glucose in an appropriate clinical situation.
Learn more in our guide to diabetes blood tests .
What About Blood Sugar After an Ordinary Meal?
After you eat, glucose naturally rises. The size and timing of the increase depend on the meal, especially the amount and type of carbohydrate, but also on activity, insulin sensitivity, medications and several other factors.
This is where readers can easily confuse two completely different situations:
| Situation | What It Means |
|---|---|
| 2-hour 75-g OGTT | A standardized medical diagnostic test using a measured glucose drink. The 140–199 mg/dL range is used to identify impaired glucose tolerance. |
| Glucose after your normal meal | A real-world monitoring reading affected by the meal, timing, activity, medicines and individual metabolism. It should not automatically be interpreted using the OGTT diagnostic thresholds. |
For people who already have diabetes, a common treatment goal is a peak post-meal glucose of less than 180 mg/dL, measured approximately 1–2 hours after the beginning of the meal. Your personal target may be different.
What Do Common Adult Blood Sugar Numbers Mean?
My fasting blood sugar is 102 mg/dL. Is that normal?
If 102 mg/dL came from a properly performed fasting laboratory test, it falls within the 100–125 mg/dL prediabetes range.
One result does not by itself prove that you have prediabetes. Your doctor may repeat the fasting glucose or compare it with HbA1c or another appropriate test.
My blood sugar is 135 mg/dL after eating. Is that high?
A glucose reading of 135 mg/dL after an ordinary meal cannot be interpreted correctly without knowing when you tested, what you ate, whether you have diabetes and what your usual readings look like.
It should not be labeled as normal, prediabetes or diabetes solely by comparing it with the diagnostic OGTT table.
My blood sugar is 180 mg/dL after eating. Is that dangerous?
For many adults who already have diabetes, the usual post-meal treatment target is less than 180 mg/dL approximately 1–2 hours after the beginning of a meal.
A single value around 180 mg/dL is therefore not automatically an emergency. However, repeated elevated readings deserve attention, particularly if you have not been diagnosed with diabetes or you have symptoms such as excessive thirst, frequent urination, blurry vision or unexplained weight loss.
For significantly higher readings and warning signs, see: What Blood Sugar Level Is Dangerous?
My blood sugar is 70 mg/dL. Is that too low?
A reading of 70 mg/dL (3.9 mmol/L) is at the low-glucose alert threshold. A reading below 70 mg/dL is classified as low blood glucose. If you have diabetes and your meter shows 70 mg/dL or below, follow your personal hypoglycemia treatment plan, especially if you have symptoms or use insulin or a medicine that can cause lows.
My fasting blood sugar is 126 mg/dL. Does that mean diabetes?
A properly performed fasting laboratory plasma glucose of 126 mg/dL or higher is within the diabetes diagnostic range.
However, when there is no unequivocal hyperglycemia or hyperglycemic crisis, the diagnosis generally needs confirmation with another abnormal test or a repeat measurement.
A reading of 126 mg/dL on a home glucose meter should therefore prompt appropriate medical assessment rather than self-diagnosis.
One Number Is Useful — A Pattern Tells Us More
I often tell patients that a single glucose result gives us a snapshot. Repeated measurements, taken in the right context, help us understand the pattern.

One reading gives information. Repeated readings can reveal a pattern.
If you monitor glucose at home, record more than just the number. It can be useful to note:
- the date and time;
- whether the reading was fasting, before food or after food;
- what you ate;
- your medicines or insulin;
- exercise;
- illness;
- poor sleep;
- stress; and
- any symptoms you experienced.
This information can make a discussion with your doctor much more useful than presenting a list of glucose numbers without context.
Why Blood Sugar Changes During the Day
Blood glucose is not supposed to remain at exactly one number throughout the day.
It can change because of food, physical activity, hormones, illness, stress, sleep, medication, alcohol, pain and your body's insulin sensitivity.
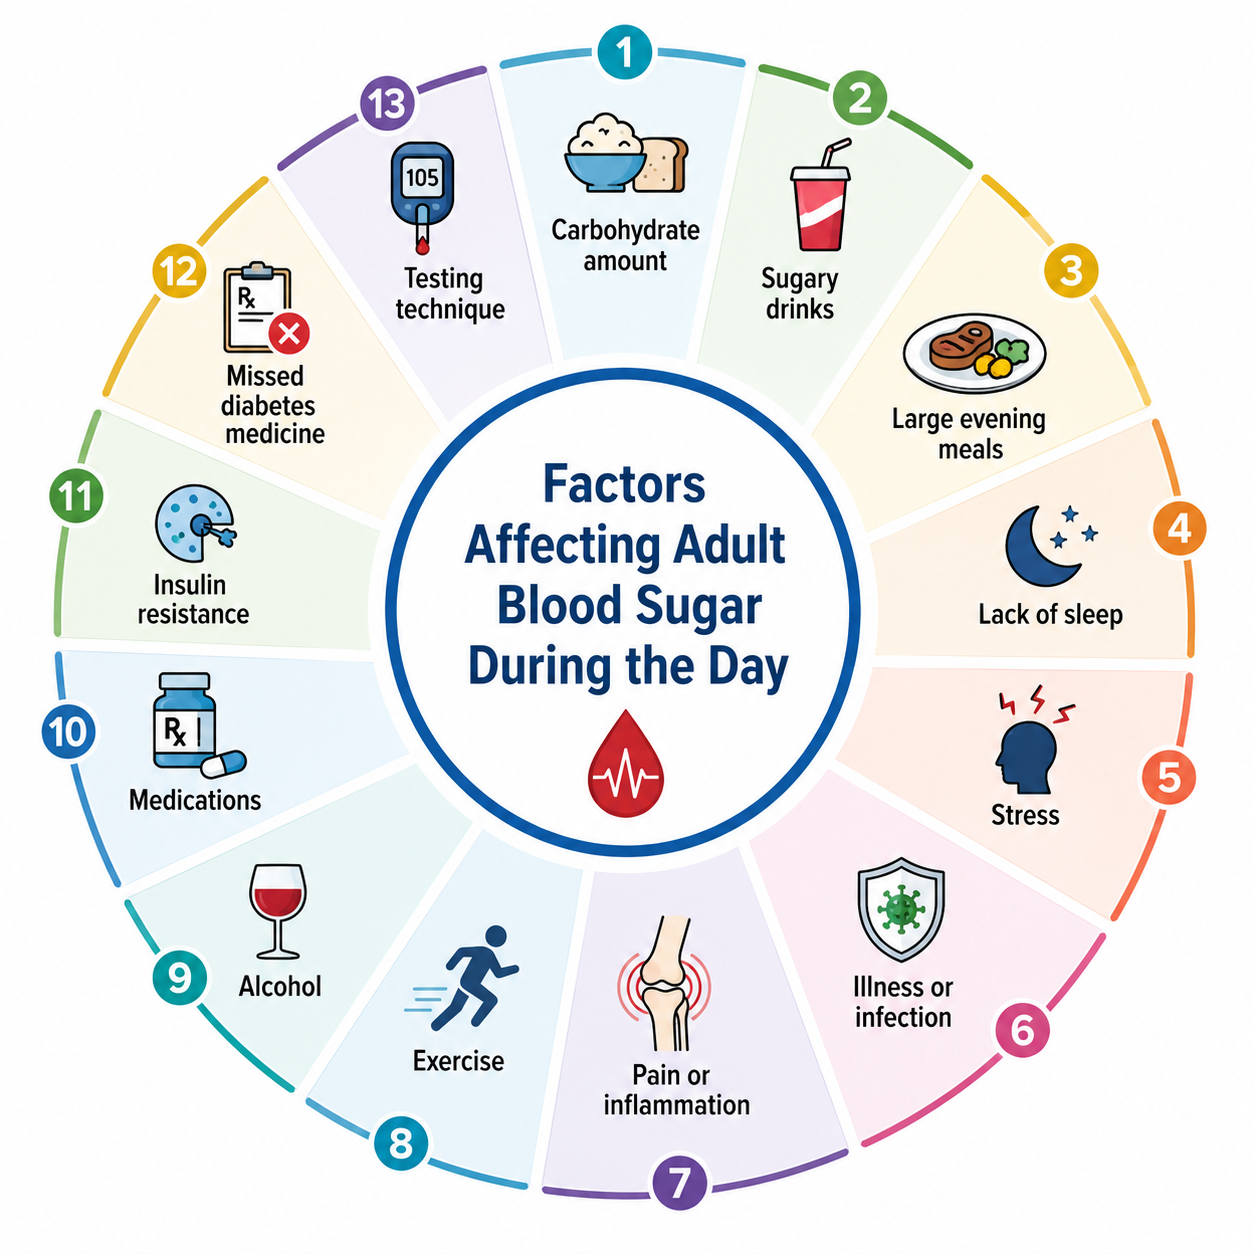
Common factors that can change blood sugar during the day.
mg/dL or mmol/L?
Blood glucose may be reported in mg/dL or mmol/L, depending on the country and laboratory.
Common examples include:
| mg/dL | Approximate mmol/L |
|---|---|
| 70 | 3.9 |
| 90 | 5.0 |
| 100 | 5.6 |
| 126 | 7.0 |
| 140 | 7.8 |
| 180 | 10.0 |
| 200 | 11.1 |
You can convert your result instantly using our Blood Sugar mg/dL ↔ mmol/L Converter .
How HbA1c Fits Into the Picture
A finger-stick glucose reading tells you what your blood sugar is doing at one point in time. HbA1c provides different information: it reflects longer-term glucose exposure over approximately the previous two to three months.
For diagnostic purposes:
- Below 5.7% is within the normal range.
- 5.7–6.4% is within the prediabetes range.
- 6.5% or higher is within the diabetes range when diagnostic requirements are met.
If you already have an HbA1c result, you can use our HbA1c to Estimated Average Glucose Calculator to see the approximate corresponding average glucose in both mg/dL and mmol/L.
When Should You Speak With Your Doctor?
Arrange medical review if:
- your fasting readings are repeatedly above the expected range;
- a laboratory fasting plasma glucose is 126 mg/dL or higher;
- your glucose repeatedly exceeds the target your diabetes team has set for you;
- you repeatedly experience glucose below 70 mg/dL;
- you develop excessive thirst or frequent urination;
- you have unexplained weight loss, unusual fatigue or blurry vision;
- your HbA1c and home glucose readings do not seem to agree; or
- you are unsure how to interpret a repeated pattern of abnormal readings.
What About Pregnancy?
Pregnancy uses different glucose targets and diagnostic pathways. Do not use the nonpregnancy tables on this page to diagnose gestational diabetes or decide whether a pregnancy glucose result is normal.
If you are pregnant, follow the testing schedule and glucose targets provided by your obstetric and diabetes care team.
Dr. Albana's Perspective
When a patient shows me a blood sugar number, I try not to label it immediately as “good” or “bad.”
First I want to know the context.
Was the person truly fasting? Was the result measured in a laboratory or on a home meter? Was it taken before a meal, 30 minutes after eating or two hours later? Does the person already have diabetes? Are they taking insulin or another medicine that could cause hypoglycemia?
Age is also part of that context, but it should be used correctly.
I would not tell an otherwise healthy 70-year-old that a fasting glucose in the diabetes range has become normal because of age. On the other hand, I would not automatically push every older person with diabetes toward the same aggressive treatment goal if doing so increases falls, hypoglycemia, confusion or treatment burden.
The safest interpretation comes from combining the number with the test type, timing, symptoms, repeated pattern and the person's overall health.
— Dr. Albana Greca
Related Questions
Related Resources and Tools
- Normal Blood Sugar Level Chart
- Normal Blood Glucose Levels: Fasting, After Meals and HbA1c
- Acceptable Blood Glucose Levels for People With Diabetes
- Blood Tests for Diabetes
- Blood Sugar mg/dL ↔ mmol/L Converter
- HbA1c to Average Glucose Calculator
- All Diabetes Calculators and Tools
- Dangerous Blood Sugar Levels: When to Seek Help
References
- American Diabetes Association. Diagnosis and Classification of Diabetes: Standards of Care in Diabetes—2026.
- American Diabetes Association. Glycemic Goals, Hypoglycemia, and Hyperglycemic Crises: Standards of Care in Diabetes—2026.
- American Diabetes Association. Older Adults: Standards of Care in Diabetes—2026.
- National Institute of Diabetes and Digestive and Kidney Diseases. Diabetes Tests & Diagnosis.
- Centers for Disease Control and Prevention. Manage Blood Sugar.
The Take-Home Message
For adults without diabetes, the laboratory thresholds used to identify normal glucose, prediabetes and diabetes do not automatically change simply because a person becomes older.
What may change with age is the treatment goal after diabetes has already been diagnosed.
The most useful questions to ask about a glucose result are:
- Was I fasting?
- Was this a laboratory result or a home meter reading?
- Was it before or after eating?
- Do I already have diabetes?
- Is this one unusual number or a repeated pattern?
Understanding those details is much safer than trying to judge your health from one glucose number alone.
Medical disclaimer: This page provides general medical education and does not replace individualized medical advice, diagnosis or treatment. Do not change insulin, diabetes medication or another prescribed treatment based only on an online article or calculator.