- Home
- New Diabetes Medications and Side Effects
- How to Manage Glucophage Side Effects
How to Manage Glucophage Side Effects?
Glucophage (metformin) commonly causes digestive side effects such as nausea, diarrhea, stomach discomfort, and reduced appetite, especially when treatment begins or the dose increases. Taking it with food, adjusting the dose gradually, or using an extended-release form may help, but persistent or severe symptoms should be discussed with your doctor.
Written by: Dr. Albana Greca Sejdini, MD, MMedSc
Medically reviewed by: Dr. Ruden Cakoni, MD, Endocrinologist
Last medically reviewed: July 2026
Glucophage is a brand name for metformin, a widely used medicine for type 2 diabetes. The most common side effects involve the stomach and intestines, especially when treatment begins or the dose increases. Many improve with time, food, slower dose adjustment, or a change to extended-release metformin.
What Is Glucophage and How Does It Work?
Metformin lowers the amount of glucose released by the liver and helps the body respond better to insulin. It has a low risk of causing hypoglycemia when used alone and usually does not cause weight gain.
Metformin remains an important treatment, but diabetes care is now individualized. Depending on heart disease, kidney disease, heart failure, weight goals, cost, and other priorities, your clinician may recommend metformin alone or combine it with another medicine. Read our guide to diabetes medicines, benefits, and side effects.
Common Glucophage Side Effects
Digestive side effects commonly appear during the first days or weeks of treatment or after a dose increase.
| Side effect | What may help | When to seek advice |
|---|---|---|
| Nausea or reduced appetite | Take the prescribed dose with or immediately after food. Smaller meals may be easier while your body adjusts. | Contact your clinician if you cannot eat, lose weight unintentionally, or symptoms remain troublesome. |
| Diarrhea | Drink enough fluid. Ask whether slower dose titration or extended-release metformin is suitable. | Seek advice for persistent diarrhea, dehydration, blood in the stool, fever, or severe pain. |
| Abdominal discomfort, bloating, or gas | Take metformin with food, eat slowly, and use smaller meals. | Urgent review is needed for severe pain, repeated vomiting, abdominal swelling, or inability to drink. |
| Metallic taste | Good oral hygiene, sugar-free gum, or chilled foods may help. It often improves with time. | Discuss persistent taste changes, mouth sores, or reduced food intake. |
| Weakness or headache | Hydrate normally and check glucose if advised. | Persistent symptoms may reflect dehydration, anemia, vitamin B12 deficiency, illness, or abnormal glucose. |
How to Manage Glucophage Stomach Side Effects
Glucophage (metformin) can cause nausea, diarrhea, bloating, or stomach discomfort, especially when you first start treatment or after a dose increase. These symptoms often improve with time, and simple changes such as taking it with food, increasing the dose gradually, or discussing an extended-release version with your doctor may help.
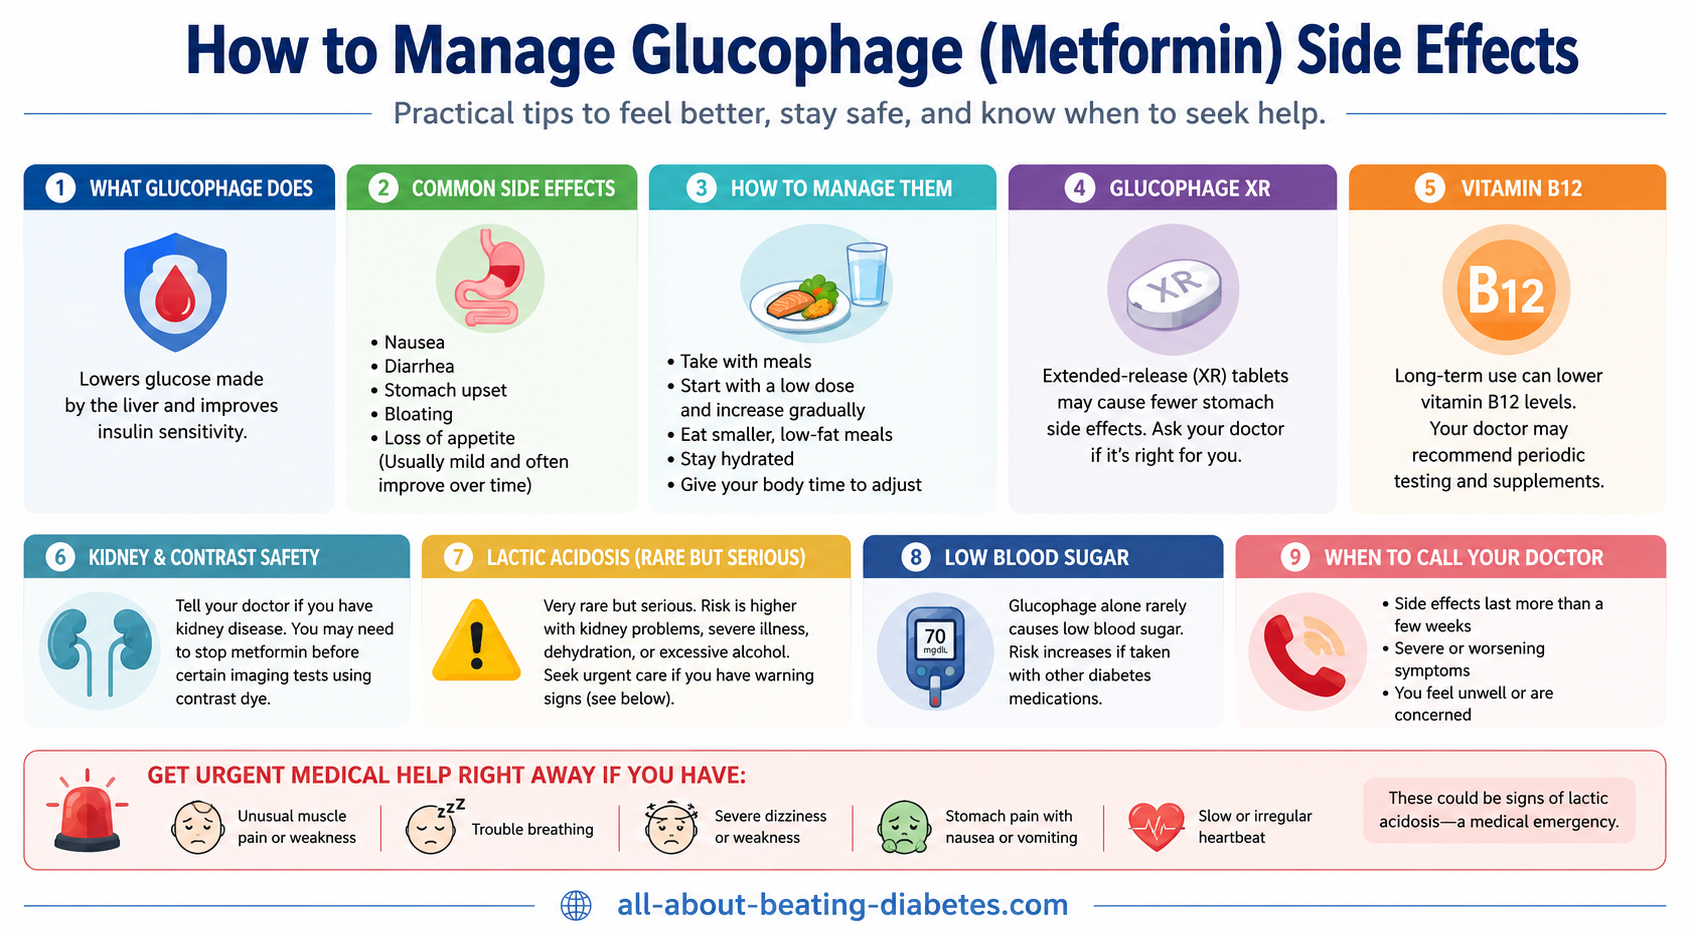

Take it with food
Immediate-release metformin is commonly taken with meals. Extended-release products are often taken with the evening meal, although instructions vary by formulation. Follow the label supplied with your medicine.
Increase the dose gradually
Starting with a lower dose and increasing it slowly can reduce digestive side effects. Do not divide, skip, combine, or change doses without your prescriber. Our metformin dosage guide explains why dosing must be individualized.
Prevent dehydration
Repeated vomiting or diarrhea can cause dehydration and temporarily reduce kidney function. This may increase metformin accumulation. Contact your healthcare team if you cannot keep fluids down or develop signs of dehydration such as dizziness, very dark urine, or reduced urination.
Do not blame every digestive symptom on metformin
New diarrhea after months or years of stable treatment, blood in the stool, fever, severe abdominal pain, nighttime symptoms, or unexplained weight loss may have another cause and should be investigated.
Would Glucophage XR Reduce Side Effects?
Glucophage XR is an extended-release form of metformin. It releases the medicine more slowly and may cause fewer gastrointestinal symptoms for some people. It is not guaranteed to remove every side effect.
Extended-release tablets should usually be swallowed whole. Some products leave an empty-looking shell in the stool after the medicine has been released; this does not necessarily mean the dose was not absorbed.
Ask your prescriber whether extended-release metformin, a slower dose increase, or a lower dose would be appropriate. Do not switch formulations by yourself because strengths and dosing schedules may differ.
Metformin and Vitamin B12 Deficiency
Long-term metformin use can reduce vitamin B12 levels. Risk may increase with higher doses, longer treatment duration, older age, reduced dietary intake, previous stomach or intestinal surgery, and medicines that reduce stomach acid.
Possible symptoms include:
- fatigue, weakness, pallor, or shortness of breath;
- numbness, tingling, burning, or reduced sensation;
- a sore or smooth tongue;
- balance problems, memory changes, or poor concentration;
- anemia found on blood testing.
These symptoms may be confused with diabetic peripheral neuropathy. Ask for vitamin B12 testing if you develop anemia or nerve symptoms. Periodic testing is also appropriate for long-term users, particularly when additional risk factors are present.
Kidney Function, Illness, Surgery, and Contrast Dye
Metformin is cleared mainly through the kidneys. Kidney function should be checked before treatment and periodically afterward.
- Metformin is contraindicated when eGFR is below 30 mL/min/1.73 m².
- Starting metformin is generally not recommended when eGFR is 30–45 mL/min/1.73 m².
- If eGFR later falls below 45, the clinician should reassess benefits, dose, risk, and monitoring.
Learn more about protecting kidney health in our diabetes and kidney guide.
Severe illness or dehydration
Vomiting, diarrhea, fever, poor fluid intake, severe infection, or another acute illness may require temporary medicine changes. Ask your diabetes team for written sick-day instructions rather than deciding alone which medicines to continue or stop.
Surgery and prolonged fasting
Tell the surgical and anesthesia teams that you take metformin. It may need to be paused when eating, drinking, oxygen levels, or kidney function may be affected. Your healthcare team should tell you when to stop and restart it.
Iodinated contrast scans
Metformin does not need to be stopped for every scan. Under U.S. prescribing information, it is withheld around iodinated contrast in certain higher-risk situations, including eGFR 30–60, liver disease, alcoholism, heart failure, or intra-arterial contrast. Kidney function may be rechecked after 48 hours before restarting.
Lactic Acidosis: Rare but Serious
Metformin-associated lactic acidosis is rare, but it is a medical emergency. Risk increases when metformin accumulates or when a serious illness causes low oxygen, kidney dysfunction, dehydration, shock, or organ failure.
Possible warning symptoms include:
- severe or unusual weakness;
- muscle pain;
- rapid, difficult, or shallow breathing;
- increasing drowsiness or confusion;
- persistent nausea, vomiting, or abdominal discomfort;
- feeling unusually cold, dizzy, or faint.
Can Glucophage Cause Low Blood Sugar?
Metformin by itself usually does not cause hypoglycemia. The risk rises when it is combined with insulin, sulfonylureas, or meglitinides, or when someone eats too little, drinks excessive alcohol, exercises more than usual, or develops significant kidney or liver disease.
Symptoms such as shaking, sweating, hunger, a fast heartbeat, irritability, confusion, or dizziness should be checked with a glucose meter when possible and managed according to your prescribed hypoglycemia plan. See our guide to high and low blood sugar readings.
When Should You Contact Your Doctor?
Arrange a medication review if:
- digestive symptoms last more than a few weeks;
- side effects interfere with eating, drinking, sleep, or daily activities;
- diarrhea or abdominal pain begins after months of stable treatment;
- you develop fatigue, anemia, numbness, tingling, or balance problems;
- you lose weight unintentionally;
- you frequently miss doses because of side effects;
- you want to change to extended-release metformin;
- you experience repeated hypoglycemia while using other diabetes medicines.
Seek urgent or emergency care for severe abdominal pain, persistent vomiting, inability to keep fluids down, facial or throat swelling, breathing difficulty, confusion, fainting, marked drowsiness, or suspected lactic acidosis.
Related Questions
- Can Metformin Cause Weakness or Kidney Failure?
- Can Metformin Cause Hair Loss?
- Can Metformin Cause a Yeast Infection?
- Can Metformin Cause Lichen Planus?
Related Resources
- Diabetes Medicines: Benefits and Side Effects
- Benefits of Metformin
- Metformin Dosage and Safe Use
- Glucophage and Weight Loss
- Diabetes and Kidney Protection
Medical disclaimer: This page provides general education and does not replace advice from your prescriber or pharmacist. Do not start, stop, or change metformin, insulin, or another medicine without individualized medical guidance.