- Home
- Diabetes Information for Patients Types Symptoms Tests and Treatment
- Diabetes Urine Test Results
Interpreting Diabetes Urine Test Results
Quick Answer
A urine test can provide useful clues, but it cannot diagnose or monitor diabetes by itself. Urine glucose may appear when blood glucose rises above the kidney’s reabsorption capacity, during pregnancy, with renal glycosuria, or as an expected effect of SGLT2 inhibitor medicines. It does not show the current blood glucose accurately.
The most important routine urine test for diabetic kidney disease is the urine albumin-to-creatinine ratio (UACR), interpreted together with a blood creatinine/eGFR test. Urine or blood ketones are safety tests for people at risk of diabetic ketoacidosis. Blood, leukocyte esterase, nitrites, pH, and specific gravity may help evaluate other urinary or medical problems but are not diabetes-control scores.
Seek urgent care for moderate or large ketones or possible DKA symptoms such as vomiting, abdominal pain, dehydration, deep or difficult breathing, fruity-smelling breath, confusion, or unusual drowsiness.
When a patient brings me a urine report, I do not interpret one colored square in isolation. I ask why the test was ordered, review symptoms and medicines, compare it with blood glucose and kidney tests, and decide whether a result needs confirmation. The same urine finding can have very different meanings in different patients.
What Can a Diabetes Urine Test Tell You?
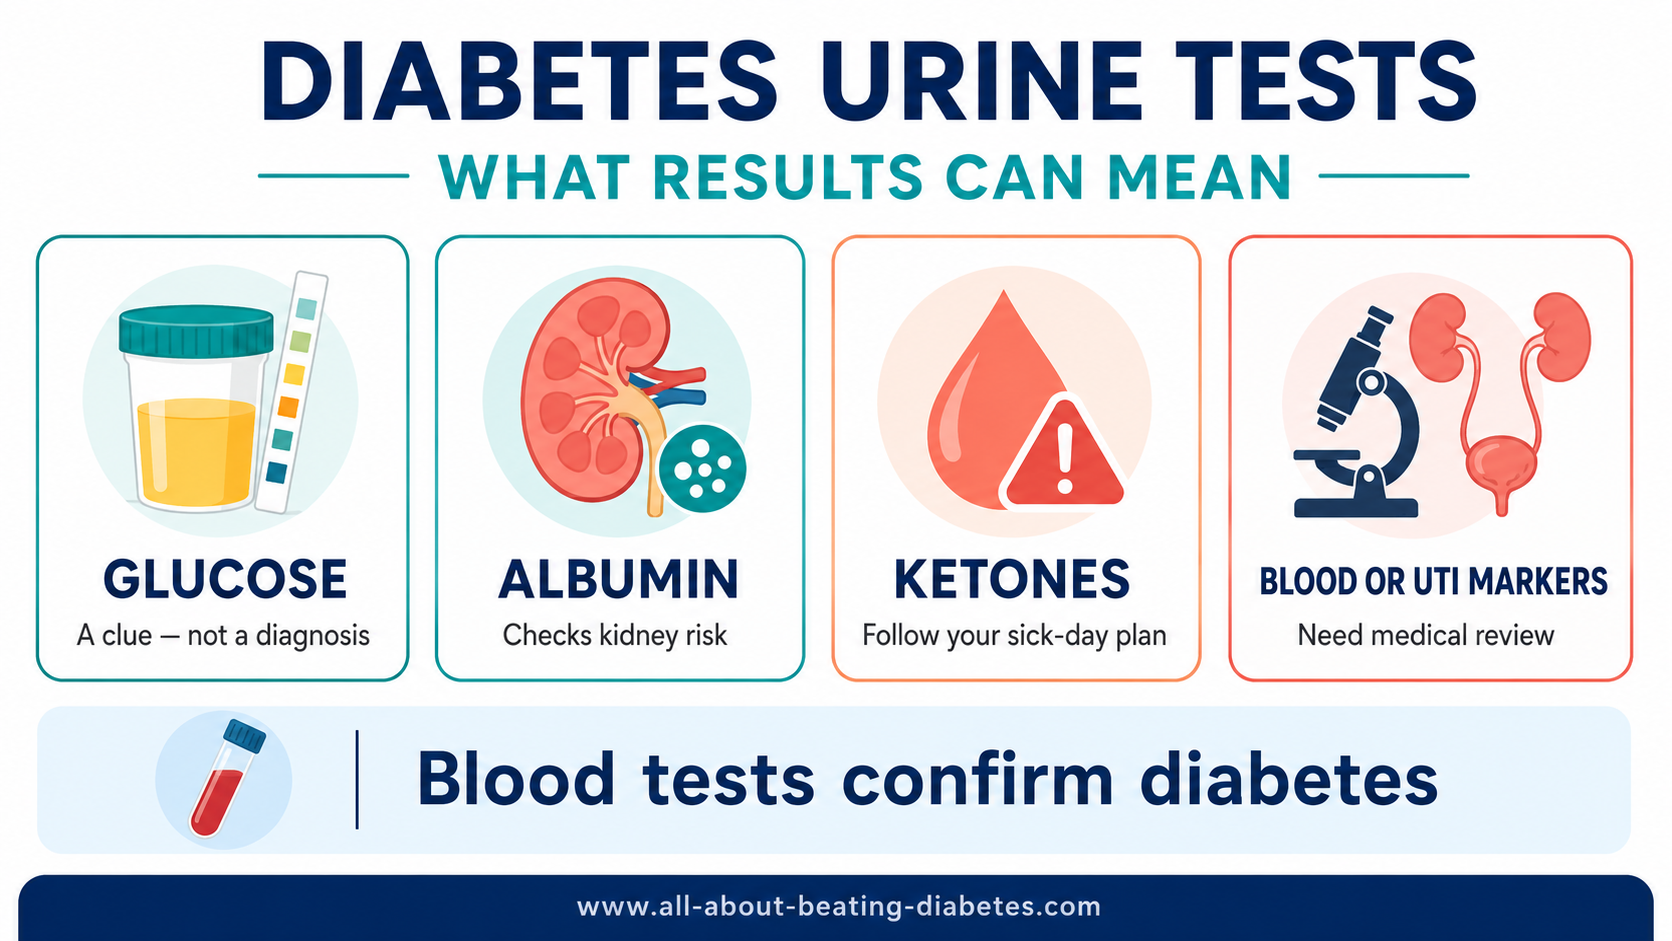
“Diabetes urine test” can refer to several different tests: a routine urinalysis, a urine glucose or ketone strip, a laboratory UACR, urine microscopy, or a urine culture. Each answers a different question.
| Result | What it may suggest | What it cannot prove |
|---|---|---|
| Glucose | Blood glucose may have been high; SGLT2 medicine effect; pregnancy; or renal glycosuria | It cannot diagnose diabetes, show the exact blood glucose, or prove kidney damage. |
| Albumin or protein | Possible kidney stress or damage; can also rise temporarily with exercise, infection, fever, marked hyperglycemia, menstruation, or other illness | A single result does not by itself establish chronic diabetic kidney disease. |
| Ketones | Fat is being used for energy; may occur with insulin deficiency, illness, fasting, vomiting, pregnancy, or a very-low-carbohydrate diet | A urine strip alone cannot confirm or measure the severity of DKA. |
| Blood / red cells | Infection, stone, inflammation, exercise, trauma, kidney disease, prostate disease, menstrual contamination, or another urinary problem | It does not identify the source without further evaluation. |
| Leukocyte esterase / white cells | Inflammation or possible urinary infection | It does not prove a bacterial UTI; contamination and other inflammation are possible. |
| Nitrites | Some nitrate-converting bacteria may be present | A negative result does not rule out a UTI because not all bacteria produce nitrites. |
| Specific gravity | How concentrated or dilute the sample is | It is not a stand-alone kidney-function test and may be altered by glucose or protein. |
| pH | Urine acidity or alkalinity, influenced by diet, medicines, specimen storage, infection, and metabolism | It cannot diagnose blood acidosis or DKA. |

What Does Glucose in Urine Mean?
The kidneys filter glucose from the blood and normally reabsorb most of it. If blood glucose rises above an individual kidney threshold, some glucose may spill into the urine. This is called glycosuria. It can happen even when the kidneys are not damaged.
Urine glucose is an imperfect reflection of what happened since the bladder last emptied. The kidney threshold varies among people and can change with age, pregnancy, kidney conditions, and medicines. A negative strip cannot rule out diabetes, and a positive strip cannot show the exact current blood glucose.
Why can urine glucose be positive when blood glucose looks normal?
- Blood glucose may have been higher earlier and returned to normal before the blood sample was taken.
- SGLT2 inhibitor medicines intentionally cause glucose to leave through the urine.
- Pregnancy may lower the kidney threshold for glucose.
- Renal glycosuria or a kidney-tubule disorder can cause urine glucose despite normal blood glucose.
- Testing technique, strip storage, timing, or an interfering substance may affect the result.
If glucose appears unexpectedly, confirm the finding with appropriate laboratory blood testing and a medication review. Our blood tests for diabetes guide explains fasting glucose, A1C, random glucose, and the OGTT.
Albumin, Protein, and Diabetic Kidney Screening
Healthy kidneys keep most albumin in the bloodstream. Persistent albumin in urine may be an early sign of kidney damage and is also associated with cardiovascular risk. A routine protein dipstick can detect larger amounts, but the recommended screening test is a laboratory spot UACR, because it corrects for how concentrated the urine is.
| UACR result | Albuminuria category | General interpretation |
|---|---|---|
| Below 30 mg/g | A1 | Normal to mildly increased. Kidney assessment still includes eGFR and clinical context. |
| 30–299 mg/g | A2 | Moderately increased. Usually repeat to confirm persistence and review blood pressure, glucose, medicines, and other causes. |
| 300 mg/g or higher | A3 | Severely increased. Requires prompt clinical assessment and a kidney-protection plan. |
A single high UACR may be temporary. Recent vigorous exercise, fever, urinary infection, marked hyperglycemia, menstruation, high blood pressure, or heart failure can affect the result. Clinicians commonly confirm albuminuria with repeat specimens rather than diagnosing chronic kidney disease from one sample.
The ADA recommends UACR and eGFR at least annually for everyone with type 2 diabetes and for people with type 1 diabetes for five years or longer. People with established chronic kidney disease need more frequent monitoring according to stage and treatment.
Read more about diabetes and kidney disease. Remember that early kidney disease is often silent, so normal-looking urine does not replace UACR and eGFR screening.
What Do Ketones in Urine Mean?
Ketones are produced when the body uses fat for energy. A positive result can occur with insufficient insulin, illness, fasting, prolonged vomiting, dehydration, pregnancy, or a ketogenic diet. Therefore, ketones do not always mean DKA—but in someone with diabetes who is sick, they must be taken seriously.
Urine ketone strips mainly detect acetoacetate. They do not measure beta-hydroxybutyrate, the predominant ketone in severe DKA, and urine reflects what accumulated in the bladder over time. For this reason, a blood beta-hydroxybutyrate test can provide more direct information when available. Neither type of home test replaces medical assessment when DKA is suspected.
When to check ketones
Follow your personal sick-day plan. Testing is often advised during illness, vomiting, unexplained high glucose, missed insulin, suspected pump failure, pregnancy with diabetes, or DKA symptoms. People taking an SGLT2 inhibitor may need testing even when glucose is not very high.
When to get urgent help
Moderate or large ketones, repeated vomiting, inability to drink, abdominal pain, deep or rapid breathing, fruity breath, severe weakness, confusion, or drowsiness require urgent medical advice or emergency care.
For a broader explanation, see diabetic ketoacidosis and other diabetes complications and our guide to dangerous blood sugar levels.
How to Interpret Other Urinalysis Results
Blood or red blood cells
Blood in urine is called hematuria. It can result from infection, a stone, kidney inflammation, prostate disease, trauma, strenuous exercise, menstrual contamination, or a urinary-tract tumor, among other causes. Visible red, pink, or cola-colored urine—or a confirmed microscopic finding—deserves medical review. Blood thinners do not make evaluation unnecessary.
Leukocytes, nitrites, and bacteria
Leukocyte esterase suggests white blood cells; nitrites suggest certain bacteria. Neither result should be interpreted alone. Symptoms such as burning, urgency, frequent urination, lower abdominal pain, fever, or flank pain help determine whether a culture and treatment are needed.
People with diabetes have a higher UTI risk, but routine screening and antibiotic treatment for bacteria in urine without symptoms are not recommended for most nonpregnant adults. Pregnancy is an important exception, because screening is recommended with a urine culture. Other special situations require individual advice.
Specific gravity
Specific gravity estimates how concentrated the urine is. A high value can occur with dehydration, glucose, protein, or other dissolved substances. A low value can occur after high fluid intake or when the kidneys cannot concentrate urine normally. One result does not measure kidney filtration and cannot replace blood creatinine/eGFR.
Urine pH
Urine pH normally varies and may be affected by diet, medicines, infection, kidney handling of acid, and how long the sample stood before testing. Urine pH does not tell us whether the blood is acidic and cannot diagnose DKA. Suspected DKA is assessed with symptoms, glucose, blood beta-hydroxybutyrate, electrolytes, bicarbonate, and blood pH or other appropriate hospital testing.
Are Dipsticks Still Used?
Yes. Modern reagent dipsticks remain widely used for screening urine glucose, ketones, blood, protein, leukocyte esterase, nitrites, pH, and specific gravity. Their value depends on using the correct strip, reading it at the specified time, storing it properly, and confirming important findings.
Benedict’s solution is a historical reducing-sugar test. It is not specific for glucose and is no longer the standard method for diagnosing or monitoring diabetes. Modern urine glucose strips are more specific, but routine urine glucose monitoring has largely been replaced by blood glucose meters and continuous glucose monitors because these give information closer to the current glucose level.
Can a Urine Test Measure Insulin Production or Diagnose MODY?
A specialized laboratory test called the urine C-peptide-to-creatinine ratio (UCPCR) can estimate the body’s own insulin secretion. It measures C-peptide—not insulin directly—in a carefully timed urine sample, often after a meal.
Research has shown that UCPCR can help distinguish long-duration type 1 diabetes from some forms of MODY and can identify who may benefit from genetic testing. It is not an ordinary home color strip, has limited availability, may be unreliable with severe kidney impairment, and cannot diagnose every diabetes type by itself.
Never stop insulin because C-peptide is detectable
Residual insulin production does not automatically mean insulin treatment is unnecessary. Diabetes classification and treatment changes require an endocrinology review, the complete clinical history, blood or urine C-peptide interpreted with glucose, diabetes autoantibodies when appropriate, kidney function, and sometimes genetic testing.
How to Collect a More Reliable Urine Sample
- Follow the laboratory or product instructions; some tests require a first-morning sample or specific timing.
- Wash your hands and use a clean, labeled container.
- For a clean-catch sample, begin urinating into the toilet, then collect the middle part of the stream without touching the inside of the cup.
- Tell the clinician about menstruation, pregnancy, recent exercise, fever, urinary symptoms, high glucose, and all medicines—including SGLT2 inhibitors and vitamin C.
- Deliver the sample promptly or store it exactly as instructed. Delays can alter bacteria, cells, pH, glucose, and ketones.
- Check home-strip expiration dates, keep the container tightly closed, and read each pad at its manufacturer-specified time.
When to Seek Urgent Medical Care
Seek emergency care now for moderate or large ketones with vomiting, inability to keep fluids down, abdominal pain, deep or difficult breathing, fruity-smelling breath, severe dehydration, confusion, fainting, or unusual drowsiness. DKA can occur in type 1 or type 2 diabetes and may occur at lower-than-expected glucose in people taking SGLT2 inhibitors.
Arrange prompt medical assessment for visible blood or clots in urine, fever with back or side pain, inability to urinate, severe urinary pain, pregnancy with UTI symptoms, rapidly increasing swelling, or a new markedly abnormal urine result.
Doctor’s Note
I use urine testing to answer a specific question: Is there albumin suggesting kidney risk? Are ketones appearing during illness? Do the symptoms suggest a urinary infection? Is unexplained blood present? I do not use urine glucose to diagnose diabetes, and I do not use urine pH to diagnose ketoacidosis. When a result is abnormal, the safest next step is to confirm it with the correct blood, laboratory urine, culture, or imaging test rather than treating the strip color alone.
Frequently Asked Questions
Can a urine test diagnose diabetes?
Not in routine modern care. Urine glucose can provide a clue, but diabetes is diagnosed with appropriate blood tests such as fasting plasma glucose, A1C, an OGTT, or random plasma glucose with classic symptoms or a hyperglycemic crisis.
Does glucose in urine mean my kidneys are damaged?
No. Glucose usually spills into urine when blood glucose exceeds the individual kidney threshold. It can also occur with SGLT2 medicines, pregnancy, or renal glycosuria. Kidney damage is evaluated with UACR, eGFR, blood pressure, and other clinical findings.
What is the most important routine urine test for diabetic kidneys?
The spot urine albumin-to-creatinine ratio, or UACR, is the recommended screening test, interpreted with blood creatinine and eGFR. A routine protein dipstick may miss smaller but clinically important albumin levels.
Do urine ketones always mean DKA?
No. Ketones can occur with fasting, vomiting, pregnancy, or low-carbohydrate intake. However, ketones in someone with diabetes who is ill—especially moderate or large ketones or ketones with vomiting, abdominal pain, breathing changes, or confusion—need urgent assessment.
Can urine pH show diabetic ketoacidosis?
No. Urine acidity is not the same as blood acidity. DKA evaluation uses the clinical picture plus blood ketones, electrolytes, bicarbonate, glucose, and blood acid-base testing.
Should every person with diabetes be tested regularly for a silent UTI?
No. Routine screening for asymptomatic bacteriuria is not recommended for most nonpregnant adults, including those with diabetes. Pregnant people should be screened with a urine culture, and special urinary or medical situations need individualized guidance.
Can a urine C-peptide result tell me to stop insulin?
No. UCPCR is a specialized test that may support diabetes classification or referral for genetic testing. Insulin changes require specialist interpretation of the full clinical picture and must never be made from a urine result alone.
Related Questions
- Can One Have Normal Sugar in Blood but High Sugar in Urine?
- Can Headache and Nausea Be Signs of Diabetic Ketoacidosis?
- Can Kidney Failure Cause Hallucinations or Forgetfulness?
Related Resources
- Blood Tests for Diabetes
- Diabetes and Kidney Disease
- Diabetes Complications and Warning Signs
- Dangerous Blood Sugar Levels
- Blood Sugar Levels by Time of Day
- Understanding Blood Glucose Readings
References
- American Diabetes Association: Chronic Kidney Disease and Risk Management—Standards of Care in Diabetes 2026.
- Sacks DB, et al. Guidelines and Recommendations for Laboratory Analysis in the Diagnosis and Management of Diabetes Mellitus. Diabetes Care. 2023;46(10):e151–e199.
- National Institute of Diabetes and Digestive and Kidney Diseases: Assess Urine Albumin.
- Centers for Disease Control and Prevention: Diabetic Ketoacidosis.
- National Institute of Diabetes and Digestive and Kidney Diseases: Hematuria—Blood in the Urine.
- U.S. Preventive Services Task Force: Screening for Asymptomatic Bacteriuria in Adults.
- Besser REJ, et al. Urinary C-Peptide Creatinine Ratio for Identifying HNF1A/HNF4A MODY From Long-Duration Type 1 Diabetes. Diabetes Care. 2011;34(2):286–291.