- Home
- Natural Remedies for Diabetes
- Vitamin D and Diabetes Benefits and Safety
Vitamin D and Diabetes: Deficiency, Testing, Supplements, and Evidence
Written by: Dr. Albana Greca Sejdini, MD, MMedSc
Medically reviewed by: Dr. Ruden Cakoni, MD, Endocrinologist
Last medically reviewed: July 2026
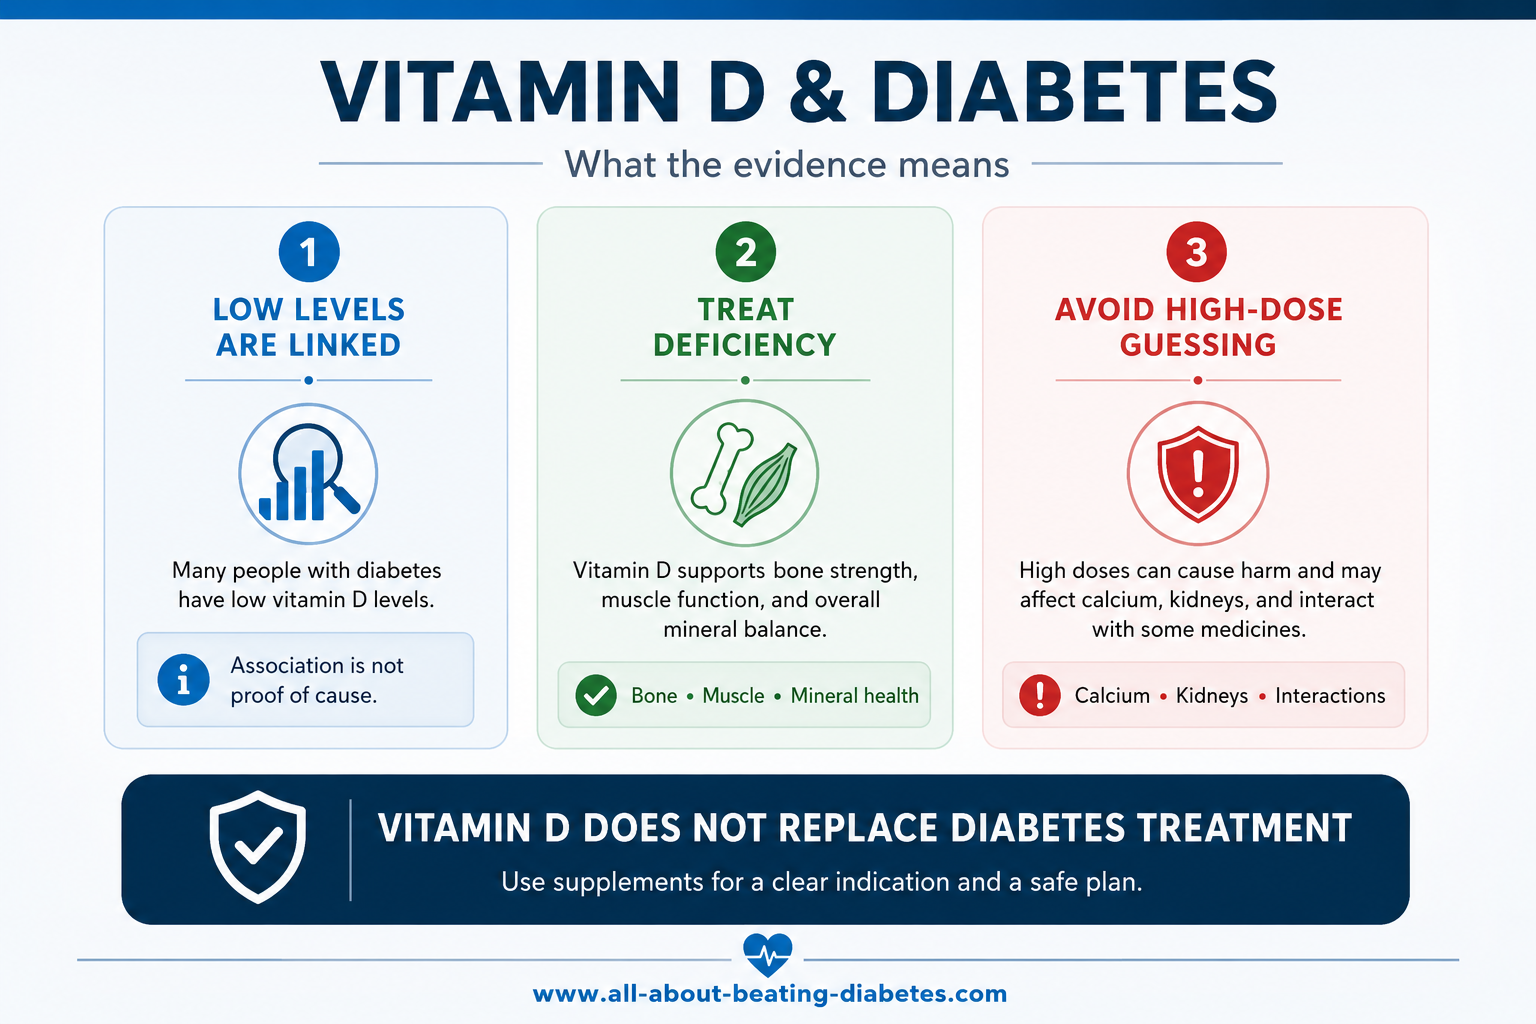
Vitamin D is essential for calcium absorption, bone mineralization, muscle function, and several immune and metabolic processes. Low vitamin D levels are common in people with obesity and chronic illness, including diabetes. That association is real, but it does not prove that vitamin D deficiency is a direct cause of diabetes.
What vitamin D does · The diabetes connection · Type 2 diabetes evidence · Prediabetes prevention · Type 1 diabetes · Diabetes complications · Deficiency symptoms · Who should be tested · Understanding 25(OH)D results · Daily intake and treatment · Food and sunlight · Toxicity and interactions
What Does Vitamin D Do?
Vitamin D is a fat-soluble vitamin and hormone precursor. The body can obtain it from food, supplements, and ultraviolet-B exposure to the skin.
Vitamin D first undergoes conversion in the liver to 25-hydroxyvitamin D [25(OH)D], the main form measured in blood. It is then converted primarily in the kidneys to the active hormone 1,25-dihydroxyvitamin D.
Its established roles include:
- supporting calcium and phosphate absorption;
- maintaining normal bone mineralization;
- preventing rickets in children and osteomalacia in adults;
- supporting muscle and neuromuscular function;
- contributing to immune and cellular regulation.
Vitamin D receptors are present in many tissues, including pancreatic beta cells, and vitamin D participates in pathways related to inflammation and glucose metabolism. Biological plausibility, however, is not the same as proof that supplementation improves diabetes outcomes.
Is Vitamin D Deficiency Linked to Diabetes?
Observational studies often find that people with lower 25(OH)D levels have more insulin resistance, prediabetes, type 2 diabetes, obesity, cardiovascular disease, and other chronic conditions.
Several explanations may contribute:
- vitamin D may have biological effects on insulin signaling and beta-cell function;
- people with obesity frequently have lower circulating 25(OH)D;
- physical inactivity and less outdoor activity may influence both metabolic health and vitamin D status;
- diet, age, chronic illness, kidney function, and socioeconomic factors may affect both;
- illness itself can alter behavior and nutrient status.
This makes cause and effect difficult to separate. An association between low vitamin D and diabetes does not prove that the deficiency caused the diabetes or that raising the level will reverse it.

Does Vitamin D Improve Type 2 Diabetes Control?
Clinical trials have produced mixed results. Some small studies and pooled analyses report modest improvements in insulin resistance, fasting glucose, or HbA1c—particularly among people who began with vitamin D deficiency. Other trials show no meaningful change.
The NIH Office of Dietary Supplements summarizes the trial evidence as showing limited benefit for diabetes management. In one reviewed meta-analysis, supplementation produced a small improvement in insulin resistance but no significant overall effect on fasting glucose, HbA1c, or fasting insulin.
Important limitations include:
- different definitions of deficiency;
- different vitamin D forms, doses, and schedules;
- short follow-up periods;
- variation in diabetes medicines and starting HbA1c;
- small studies and subgroup analyses;
- differences in weight, ethnicity, kidney function, and baseline status.
The practical conclusion is that confirmed deficiency should be treated for health reasons, but vitamin D should not be prescribed as a substitute for glucose-lowering therapy. An improved 25(OH)D result does not prove that diabetes treatment can be reduced.
Review established treatment options in Diabetes Medications: Benefits and Side Effects.
Can Vitamin D Prevent Type 2 Diabetes?
The answer depends on the population being studied.
People in the general population
In a 2025 randomized analysis of more than 22,000 older U.S. adults without diabetes, 2,000 IU of vitamin D3 daily did not significantly reduce new type 2 diabetes over a median of 5.3 years. When those results were combined with several earlier trials, the pooled reduction was modest.
Adults with high-risk prediabetes
A 2023 individual-participant meta-analysis of three trials in adults with prediabetes reported an approximately 15% relative reduction in progression to diabetes over about three years, with a modest absolute benefit.
Based on this evidence, the Endocrine Society’s 2024 guideline conditionally suggests empiric vitamin D supplementation, in addition to lifestyle modification, for adults with high-risk prediabetes. The trials mainly enrolled people meeting two or three glycemic criteria for prediabetes or those with impaired glucose tolerance.
Lifestyle intervention remains the foundation of prediabetes care. Vitamin D does not replace physical activity, nutrition changes, weight-management support when appropriate, or metformin for selected high-risk patients.
See the prediabetes guide and the insulin resistance guide.
Vitamin D and Type 1 Diabetes
Observational studies have explored vitamin D status, early-life supplementation, immune regulation, and type 1 diabetes risk. These findings have not established vitamin D as a method to prevent, reverse, or treat autoimmune beta-cell destruction.
For someone with established type 1 diabetes:
- vitamin D cannot replace basal, mealtime, or correction insulin;
- it does not prevent DKA;
- it has not been shown to regenerate functioning beta cells;
- deficiency should be evaluated and treated for the same bone and health reasons that apply to other people.
Stopping insulin because of a supplement can cause life-threatening ketoacidosis. Read the type 1 diabetes information guide.
Does Vitamin D Prevent Diabetes Complications?
Low 25(OH)D levels have been associated in observational studies with neuropathy, kidney disease, retinopathy, cardiovascular disease, poor wound healing, and other complications. These associations may reflect overall illness, kidney function, activity, nutrition, obesity, or other confounding factors.
Clinical trials have not established vitamin D supplements as a reliable way to prevent or treat:
- diabetic neuropathy;
- kidney disease;
- retinopathy;
- heart attack or stroke;
- diabetic foot ulcers;
- infection or impaired wound healing.
Treating a real deficiency may improve bone pain, muscle weakness, or osteomalacia. That is different from claiming that vitamin D treats a diabetes complication.
Evidence-based complication prevention includes individualized glucose management, blood-pressure and cholesterol treatment, kidney testing, eye examinations, foot care, physical activity, smoking cessation, and appropriate organ-protective medicines. See the diabetes complications guide.
What Are the Symptoms of Vitamin D Deficiency?
Mild vitamin D inadequacy often causes no obvious symptoms. When deficiency is severe or prolonged, it can impair bone mineralization and cause rickets in children or osteomalacia in adults.
Possible findings include:
- bone pain or tenderness;
- proximal muscle weakness, such as difficulty climbing stairs or rising from a chair;
- muscle aches or cramps;
- fragility fractures;
- low calcium symptoms in severe cases, including spasms or tingling.
Fatigue, low mood, hair loss, frequent infection, cognitive complaints, dental problems, and slow wound healing are nonspecific. They should not be used to diagnose vitamin D deficiency without appropriate assessment.
Symptoms can also result from anemia, thyroid disease, medication effects, kidney disease, neuropathy, depression, sleep disorders, infection, or uncontrolled glucose.
Should Everyone With Diabetes Be Tested?
No major guideline recommends routine 25(OH)D testing solely because a person has diabetes. The Endocrine Society advises against routine testing in generally healthy adults without another established indication.
Testing may be reasonable when there is concern about:
- bone pain, muscle weakness, fractures, osteomalacia, or osteoporosis;
- low blood calcium or phosphate;
- malabsorption, inflammatory bowel disease, celiac disease, or pancreatic disease;
- bariatric or gastric-bypass surgery;
- advanced kidney or liver disease;
- limited dietary intake or prolonged institutional living;
- medicines that alter vitamin D or calcium metabolism;
- treatment of a documented deficiency that requires follow-up;
- another condition for which the clinician needs vitamin D status.
Obesity and darker skin are associated with lower average 25(OH)D levels, but the 2024 Endocrine Society guideline does not recommend routine screening based on those characteristics alone in otherwise healthy adults.
Which vitamin D test is used?
The standard test is serum 25-hydroxyvitamin D [25(OH)D]. The active hormone, 1,25-dihydroxyvitamin D, is generally not a good routine measure of vitamin D stores because it is tightly regulated and may remain normal until deficiency is severe.
How Are Vitamin D Blood Levels Interpreted?
Thresholds remain an area of debate, and laboratories or professional groups may use different language. The U.S. Food and Nutrition Board uses the following general framework for bone and overall health:
| 25(OH)D | Equivalent | General interpretation |
|---|---|---|
| Below 12 ng/mL | Below 30 nmol/L | Associated with deficiency and risk of rickets or osteomalacia. |
| 12 to below 20 ng/mL | 30 to below 50 nmol/L | Generally considered inadequate for bone and overall health in healthy people. |
| 20 ng/mL or above | 50 nmol/L or above | Generally adequate for most healthy people. |
| Above 50 ng/mL | Above 125 nmol/L | Linked to potential adverse effects; higher is not automatically better. |
Unit conversion: 1 ng/mL equals 2.5 nmol/L.
These are reference categories, not universal diabetes treatment targets. The optimal level for preventing diabetes or a specific complication has not been established.
How Much Vitamin D Is Recommended?
General U.S. recommended dietary allowances assume minimal sun exposure:
| Group | Recommended intake |
|---|---|
| Infants 0–12 months | 400 IU (10 mcg) daily |
| Children and adults 1–70 years | 600 IU (15 mcg) daily |
| Adults older than 70 years | 800 IU (20 mcg) daily |
| Pregnancy and breastfeeding | 600 IU (15 mcg) daily under U.S. dietary reference values |
These amounts are general nutrition recommendations, not treatment doses for confirmed deficiency and not diabetes-treatment doses.
Treating confirmed deficiency
Deficiency treatment may require a higher dose for a limited period, followed by maintenance. The correct regimen depends on the starting level, age, body size, malabsorption, kidney and liver function, calcium, parathyroid hormone, medicines, pregnancy, and the reason for testing.
Do not copy a high-dose weekly or monthly regimen from another person. Adults with significant kidney disease may need specialist-selected forms of vitamin D or active analogues rather than ordinary self-treatment.
D2 or D3?
Vitamin D2 and D3 can both raise 25(OH)D. Vitamin D3 often raises and maintains levels more effectively in comparative studies, but product choice and dose should follow the treatment plan.
Food and Natural Sources of Vitamin D
Food sources
Few foods naturally contain substantial vitamin D. Useful sources include:
- fatty fish such as salmon, trout, sardines, mackerel, and tuna;
- fish-liver oils, used cautiously because vitamin A content may also be high;
- egg yolks and small amounts in liver and cheese;
- UV-exposed mushrooms;
- fortified milk or selected fortified plant drinks;
- fortified cereals, yogurt, margarine, or other foods, depending on the country.
Check the nutrition label because fortification varies. Choose unsweetened products when glucose and carbohydrate are concerns.
Sunlight
The skin can make vitamin D after UVB exposure, but there is no single safe number of minutes that works for everyone. Production varies with season, latitude, time of day, cloud cover, skin pigmentation, age, clothing, and sunscreen.
Do not deliberately seek sunburn, stop using sun protection, or use tanning beds to raise vitamin D. UV exposure increases skin-cancer and skin-aging risk. Food and an appropriately dosed supplement provide a more controllable approach when intake is inadequate.
Weight and vitamin D
People with obesity often have lower circulating 25(OH)D because more vitamin D is distributed into body tissues. Weight loss can raise measured levels in some people, but vitamin D supplements have not been shown to produce meaningful weight loss.
Use the diabetes meal-planning guide for a broader approach to nutrition.
Vitamin D Safety, Toxicity, and Interactions
Upper intake limit
The general tolerable upper intake level for adults and children aged 9 years or older is 4,000 IU (100 mcg) per day from all sources. This is not a recommended daily target. Clinicians may prescribe more for a limited period to treat deficiency, but that requires an appropriate plan.
Vitamin D toxicity
Excess supplement intake can cause hypercalcemia and hypercalciuria. Possible symptoms include:
- nausea, vomiting, constipation, or loss of appetite;
- muscle weakness;
- confusion or other neuropsychiatric changes;
- excessive thirst and frequent urination;
- dehydration;
- kidney stones or kidney injury;
- abnormal heart rhythm;
- soft-tissue and blood-vessel calcification in severe cases.
These symptoms can resemble uncontrolled diabetes. If someone taking high-dose vitamin D develops thirst, urination, weakness, vomiting, or confusion, checking only glucose is not enough; calcium, kidney function, and vitamin D exposure also require review.
Medicine interactions and special cautions
Discuss vitamin D with a clinician or pharmacist when using:
- thiazide diuretics, which can increase hypercalcemia risk when combined with vitamin D, particularly with kidney impairment or hyperparathyroidism;
- orlistat, which can reduce vitamin D absorption;
- long-term corticosteroids, which can impair vitamin D and calcium metabolism;
- medicines or conditions affecting fat absorption;
- large calcium supplements;
- multiple vitamin products that may duplicate the dose.
Kidney stones, high calcium, sarcoidosis or another granulomatous disease, hyperparathyroidism, advanced kidney disease, pregnancy, and childhood all require individualized advice.
A Practical Decision Guide
- Decide why vitamin D is being considered. Bone health, confirmed deficiency, high-risk prediabetes, and general wellness are different questions.
- Do not assume diabetes automatically requires a test. Review symptoms and risk factors.
- Use the correct test. Ask whether serum 25(OH)D is appropriate.
- Add all sources. Count vitamin D in multivitamins, calcium products, cod-liver oil, fortified food, and separate supplements.
- Review calcium, kidney function, and medicines.
- Agree on a dose and duration. Do not remain indefinitely on a deficiency-treatment dose without review.
- Repeat testing only when it will change management.
- Continue established diabetes care. Vitamin D does not replace glucose monitoring or treatment.
Most Asked Questions
Can vitamin D lower HbA1c?
Some trials report a small change, especially in people who are deficient, but the overall evidence is inconsistent. Vitamin D is not a reliable HbA1c-lowering treatment.
Can vitamin D reverse insulin resistance?
No. Correcting deficiency may support overall health, but vitamin D alone has not been shown to reverse the multiple causes of insulin resistance.
Should everyone with type 2 diabetes take vitamin D?
Not automatically. Ensure adequate intake and treat documented deficiency or another clinical indication. A diabetes diagnosis alone does not establish a universal supplement dose.
What is the best vitamin D level for diabetes?
No diabetes-specific optimal 25(OH)D target has been proven. Levels should be interpreted according to bone health, clinical context, laboratory method, and the reason for testing.
Can I take 5,000 or 10,000 IU daily?
Those amounts exceed the general adult upper intake level when taken routinely. They may occasionally be used under medical supervision for a defined indication, but should not be self-prescribed long term.
Does vitamin D help diabetic neuropathy?
Low levels and neuropathy may occur together, and small studies have explored supplementation. Evidence is not strong enough to use vitamin D as established neuropathy treatment unless deficiency is also present.
Related Questions
- Why Is HbA1c High When Finger-Prick Readings Look Normal?
- Fasting Glucose 159 but Two-Hour Glucose 109: Am I Diabetic?
- How Should GTT and Insulin Resistance Results Be Interpreted?
Related Resources
- Vitamins and Minerals for Diabetes
- What Is Insulin Resistance?
- Prediabetes: Symptoms, Testing, and Prevention
- Type 2 Diabetes Information
- Blood Tests for Diabetes
- Natural Cures for Diabetes? What the Evidence Shows
Medical disclaimer: This article provides general education and does not diagnose vitamin D deficiency, prescribe a supplement dose, or replace diabetes treatment. Do not start prolonged high-dose vitamin D or change insulin or medication without individualized medical advice.
References
- NIH Office of Dietary Supplements: Vitamin D Fact Sheet for Health Professionals
- Endocrine Society: Vitamin D for the Prevention of Disease Clinical Practice Guideline, 2024
- American Diabetes Association: Prevention or Delay of Diabetes—Standards of Care in Diabetes 2026
- American Diabetes Association: Comprehensive Medical Evaluation—2026
- Tobias and colleagues: Vitamin D Supplementation and Incident Type 2 Diabetes in the VITAL Trial, 2025
- Pittas and colleagues: Vitamin D and Risk for Type 2 Diabetes in People With Prediabetes—Systematic Review and Individual Participant Meta-analysis
- Pittas and colleagues: Vitamin D Supplementation and Prevention of Type 2 Diabetes—D2d Trial