- Home
- Diabetes Answers and Tools
- Sugar Level 250-400 mg/dl
Blood Sugar 250–400 mg/dL: What It Means and What To Do
A blood sugar reading of 250, 300, 350 or 400 mg/dL is significantly elevated. Whether you tested before breakfast, after eating or during illness, these readings need attention.
The immediate concern is not the number alone. Your symptoms, ketone levels, hydration, type of diabetes, medication history, pregnancy status and response to your prescribed treatment help determine how urgently you need medical care.

Yes. Blood sugar between 250 and 400 mg/dL (13.9–22.2 mmol/L) is very high. It can be associated with dehydration, ketones and, in some circumstances, diabetic ketoacidosis (DKA) or hyperosmolar hyperglycemic state (HHS).
If you have a high meter reading, wash and dry your hands and repeat the test. Check how you feel, drink water if it is safe for you, check ketones when indicated and follow your prescribed high-glucose or sick-day plan.
Seek emergency care if you experience vomiting, severe abdominal pain, deep or difficult breathing, confusion, fainting or suspected ketoacidosis. Do not wait for glucose to reach 400 mg/dL before seeking help.
- Moderate or large urine ketones or concerning blood ketone results.
- Persistent vomiting or inability to keep fluids down.
- Fruity-smelling breath or deep, rapid breathing.
- Confusion, fainting, extreme sleepiness or loss of consciousness.
- Chest pain, serious breathing difficulty or severe weakness.
- Significant dehydration or severe abdominal pain.
- Very high glucose during pregnancy or serious illness.
If these signs occur, seek emergency medical assistance.
This guide cannot determine your insulin dose or replace your personalized diabetes treatment plan. Do not double medication, stop prescribed treatment, or take an unplanned correction dose based on a webpage.
For further context, read Is My Blood Sugar Too High or Too Low?
On This Page
What Does a Blood Sugar Level of 250–400 mg/dL Mean?
A glucose result in this range means there is too much glucose in your bloodstream. Doctors call this hyperglycemia.
Many nonpregnant adults with diabetes have individualized goals close to 80–130 mg/dL before meals and below 180 mg/dL one to two hours after starting a meal. These are common management targets, not diagnostic thresholds for everyone.
A reading of 250–400 mg/dL is substantially above these goals, but a single glucose reading cannot tell you the type of diabetes, how much insulin you need, or whether you have developed DKA or HHS.
Your doctor considers:
- Whether diabetes is already diagnosed.
- Type 1, type 2, gestational or another form of diabetes.
- Fasting, post-meal or illness-related timing.
- Symptoms and hydration.
- Ketone results when indicated.
- Use of insulin and other diabetes medications.
- Pregnancy or other medical conditions.
- Whether the elevation is isolated or repeated.
- Recent changes in medicines, including steroids.
- Possible insulin pump, infusion-site or injection problems.
Compare different times of day in Blood Sugar Levels by Time of Day and read Is My Blood Sugar Normal?
Blood Sugar Conversion Table: 250–400 mg/dL to mmol/L
Some glucose meters report milligrams per deciliter (mg/dL), while others report millimoles per liter (mmol/L). These are different units for the same blood glucose concentration.
| Blood glucose (mg/dL) | Approximate mmol/L |
|---|---|
| 250 | 13.9 |
| 275 | 15.3 |
| 300 | 16.7 |
| 325 | 18.0 |
| 350 | 19.4 |
| 375 | 20.8 |
| 400 | 22.2 |
For glucose, divide mg/dL by approximately 18 to obtain mmol/L. For the reverse conversion, multiply mmol/L by approximately 18.
Use the interactive Blood Sugar Converter for other values.
Is Blood Sugar 250–400 mg/dL Dangerous?
Yes, especially when glucose stays high, continues rising or occurs with illness or warning symptoms.
The main immediate concerns include:
- Dehydration from increased urination.
- Ketone accumulation.
- Diabetic ketoacidosis (DKA).
- Hyperosmolar hyperglycemic state (HHS).
- Worsening infection or illness.
- Weakness, confusion and other serious complications.
Diabetic Ketoacidosis (DKA)
DKA occurs when insufficient effective insulin allows ketones to accumulate, causing metabolic acidosis. It is more common in type 1 diabetes, but it can occur with type 2 diabetes as well.
Illness, missed insulin, insulin pump delivery failure and certain medications may increase risk. DKA can occur at glucose values below 400 mg/dL, sometimes even without marked hyperglycemia.
Hyperosmolar Hyperglycemic State (HHS)
HHS typically involves extreme hyperglycemia, substantial dehydration and high blood osmolality. It occurs more often in people with type 2 diabetes, particularly older or medically vulnerable adults.
HHS usually develops with glucose much higher than 400 mg/dL. A meter reading alone cannot diagnose or exclude either HHS or DKA.
What Should You Do If Blood Sugar Is 250–400 mg/dL?
If you are awake, able to drink and do not have emergency symptoms, use the following steps alongside your own diabetes action plan.
1. Wash Your Hands and Check Again
Fruit, sugar, juice or food residue on your fingers can make a glucose meter display a falsely high value.
Wash your hands with soap and water, dry them well and repeat the test with a fresh strip. If you use a CGM and the sensor result does not fit your symptoms, follow your device instructions for confirmation with a finger-stick reading.
2. Think About the Timing and Possible Cause
Ask yourself:
- Was the reading before breakfast or after eating?
- Did I miss insulin or another diabetes medicine?
- Do I have a fever, infection or other illness?
- Did I start steroids or another new medicine?
- Could my insulin pump or injection device have malfunctioned?
- Have I been unusually stressed or inactive?
- Have I been drinking enough fluids?
- Has glucose remained high for several hours?
A reading after food may decline as treatment takes effect, but a result of 250–400 mg/dL still requires careful attention.
3. Drink Water If You Can Safely Do So
Elevated glucose may increase urination and fluid loss. Water can help reduce dehydration when you can drink safely and have no fluid restriction.
Rather than sugary beverages, choose water. Avoid regular soda, sweet tea, fruit juice and sugar-containing energy drinks while responding to an elevated glucose reading, unless you are treating hypoglycemia under a prescribed plan.
Do not force fluids if you are vomiting repeatedly, confused, unable to swallow safely or severely short of breath. Seek medical assistance.
4. Check Ketones When Indicated
Ketone testing is especially important for people at risk of ketoacidosis, including many people with type 1 diabetes, during illness or after missed insulin doses.
Follow your personal sick-day instructions for the glucose level at which to check ketones. If you use an SGLT2 inhibitor and have symptoms of DKA, seek assessment even when glucose is not extremely high.
5. Avoid Exercise If Ketones or Serious Symptoms Are Present
Physical activity may lower glucose under some circumstances, but exercise can worsen a dangerous situation when insulin deficiency and significant ketones are present.
Do not exercise if you have ketones, vomiting, abdominal pain, severe weakness, dehydration, chest pain, breathing difficulty or suspected insulin delivery failure.
6. Follow Your Prescribed Diabetes Action Plan
If your clinician has provided a correction insulin plan, sick-day plan or insulin pump troubleshooting instructions, follow them.
- Do not guess insulin doses from an online article.
- Do not take someone else's diabetes medication.
- Do not repeatedly correct glucose without considering active insulin.
- Do not stop prescribed treatment on your own.
- Contact your diabetes team if you do not know how to respond.
Learn more about safe insulin principles in Insulin Treatment for Diabetes.
When Should You Check Ketones?
Ketones may rise when the body has insufficient effective insulin and begins breaking down fat for energy. A significant accumulation can lead to DKA.
Ketones can be checked using urine strips or a blood ketone meter. Blood testing measures beta-hydroxybutyrate, the principal circulating ketone in DKA.
Check ketones according to your clinician's plan when you are ill, have missed insulin, have persistent high glucose, or develop nausea, vomiting, abdominal pain, fruity breath or unusual breathing.
Moderate or large urine ketones, significantly elevated blood ketones, or symptoms suggesting DKA require urgent medical assessment. Do not wait at home for severe symptoms to resolve.
When Should You Contact Your Doctor?
Contact your diabetes care team promptly when elevated glucose is persistent, repeated or difficult to manage.
- Glucose is repeatedly 250 mg/dL or higher.
- Glucose stays high after you follow your prescribed plan.
- You develop fever, infection or another illness.
- You have ketones or do not know how to interpret a ketone result.
- You miss insulin or suspect a pump or injection problem.
- Your medicine or insulin needs may have changed.
- You are eating less but glucose remains high.
- You have repeated morning hyperglycemia.
- You have started steroid treatment.
- You are pregnant or planning pregnancy.
- You have no written high-glucose or sick-day plan.
Doctor's note: Repeated high readings may indicate that your diabetes management plan needs review. Avoid changing doses without medical instructions or a pre-established adjustment plan.
When Should You Seek Emergency Medical Help?
Do not delay if high glucose is accompanied by symptoms suggesting DKA, HHS, severe dehydration or another serious medical condition.
- Moderate or large ketones with concerning symptoms.
- Persistent vomiting or inability to drink.
- Fruity-smelling breath.
- Deep, rapid or difficult breathing.
- Severe abdominal pain.
- Confusion, fainting, extreme sleepiness or unconsciousness.
- Chest pain or symptoms resembling a stroke.
- Severe dehydration.
- Glucose around 400 mg/dL that remains elevated.
- Glucose over 300 mg/dL that persists despite your established plan.
- Serious illness with high glucose during pregnancy or childhood.
A person can develop ketoacidosis before the meter reaches 400 mg/dL. Symptoms and ketone status matter more than waiting for a particular number.
Common Symptoms of Blood Sugar 250–400 mg/dL
Some people notice symptoms quickly. Others, including some people with long-standing type 2 diabetes, may have marked hyperglycemia without obvious symptoms.
- Frequent urination.
- Excessive thirst.
- Dry mouth.
- Blurred vision.
- Fatigue and weakness.
- Headaches.
- Difficulty concentrating.
- Nausea or abdominal discomfort.
- Slow wound healing.
- More frequent infections.
- Unexplained weight loss with persistent hyperglycemia.
Why Can Blood Sugar Rise to 250–400 mg/dL?
- Missed diabetes medication.
- Insufficient insulin for current needs.
- More carbohydrate than planned.
- Sweetened beverages.
- Illness or infection.
- Fever, pain or injury.
- Physical or emotional stress.
- Steroid medication such as prednisone.
- Other medicines that affect glucose regulation.
- Dehydration.
- Insulin pump obstruction or infusion-site failure.
- Expired insulin or insulin exposed to inappropriate temperatures.
- Incorrect injection technique.
- Dawn phenomenon.
- Progression of type 2 diabetes.
- Pregnancy-related insulin resistance.
The treatment response depends on the cause. This is why documenting the circumstances around high readings helps your doctor evaluate them.
Special Situations and Important Questions
Can Someone Without Diabetes Have Blood Sugar 250–400 mg/dL?
Yes. A person without a previous diabetes diagnosis can have very high glucose due to undiagnosed diabetes, illness, medications, pancreatic disorders, hormonal conditions or testing error.
If you do not have diagnosed diabetes and obtain a confirmed result of 250 mg/dL or higher, arrange prompt medical assessment. Seek emergency care if you also have concerning symptoms.
Can Blood Sugar 250–400 mg/dL Happen After Eating?
Yes. Glucose can rise substantially after food, particularly when insulin production or insulin action is insufficient. However, this range is still much higher than usual post-meal targets for many adults with diabetes.
Possible contributors include missed medication, meal carbohydrate content, illness, less activity, or incorrect insulin timing.
Write down the meal, test timing, medication and symptoms. Read Blood Sugar Levels After Eating.
Should You Take Extra Insulin?
Only follow a correction dose plan if your diabetes care team has already provided one.
Safe correction dosing depends on your individual insulin sensitivity, glucose target, active insulin, recent food, activity, ketones and clinical status.
Taking too much insulin or giving repeated corrections too close together can cause serious hypoglycemia.
For education on these concepts, see Insulin Bolus and Correction Calculator Guide. Do not use its educational examples as a prescription.
Should You Stop a Medicine That May Be Raising Glucose?
No. Do not stop prescribed medication without medical advice. Steroids and several other medicines may raise blood glucose, but stopping them suddenly can be unsafe.
Write down the medication name, dose and start date, monitor as instructed and contact the prescribing clinician about an appropriate plan.
What About SGLT2 Inhibitors?
SGLT2 inhibitors, including medicines such as empagliflozin and dapagliflozin, may be used for diabetes and certain heart or kidney conditions.
These medicines are associated with a rare risk of ketoacidosis, sometimes despite glucose that is not extremely elevated.
If you take an SGLT2 inhibitor and develop vomiting, abdominal pain, rapid breathing, unusual weakness or other symptoms of DKA, seek urgent medical assessment and check ketones if appropriate and available.
Follow your personalized sick-day instructions regarding withholding or restarting medications. Do not make unsupervised changes.
What If Your Reading Is 250–299, 300–399 or 400 mg/dL?
Blood Sugar 250–299 mg/dL
This is significantly elevated. Confirm the result, review the timing of meals and medicines, drink water if safe, check ketones when indicated and follow your prescribed plan.
If readings are repeated or do not improve, contact your care team. If you are sick or have DKA symptoms, seek urgent assessment.
Blood Sugar 300–399 mg/dL
This is markedly high and may become dangerous, especially if persistent or accompanied by dehydration or ketones.
Confirm the reading, follow your high-glucose action plan, check ketones when appropriate and seek prompt medical advice if glucose does not improve.
Vomiting, confusion, deep breathing, severe dehydration or other serious symptoms require emergency evaluation.
Blood Sugar 400 mg/dL
A reading around 400 mg/dL is high risk and should not be ignored.
Recheck correctly. If it remains around 400 mg/dL, follow your emergency or sick-day instructions and seek urgent medical assessment, particularly if you have no effective management plan or any concerning symptoms.
Blood Sugar 250–400 mg/dL in Children
Children with diabetes can develop dehydration and ketones, sometimes rapidly. Follow the child's specific diabetes sick-day plan.
Check ketones when indicated and seek urgent medical advice for persistent high glucose, missed insulin or possible pump problems.
- Vomiting or abdominal pain.
- Moderate or large ketones.
- Rapid or deep breathing.
- Fruity-smelling breath.
- Marked tiredness, confusion or dehydration.
- Persistent very high glucose with suspected insulin failure.
Do not delay emergency assessment for a child with suspected DKA.
Blood Sugar 250–400 mg/dL During Pregnancy
Very high glucose during pregnancy requires prompt contact with the pregnancy or diabetes care team. Pregnancy uses specific glucose targets and clinical safety protocols.
Seek emergency care for vomiting, ketones, abdominal pain, difficulty breathing, severe weakness, altered consciousness or reduced fetal movement.
How to Prevent Repeated Blood Sugar Readings of 250–400 mg/dL
Prevention depends on the reason glucose is rising. The goal is to identify patterns and make safe adjustments with your diabetes team, not to respond to every high reading by guessing a new treatment dose.
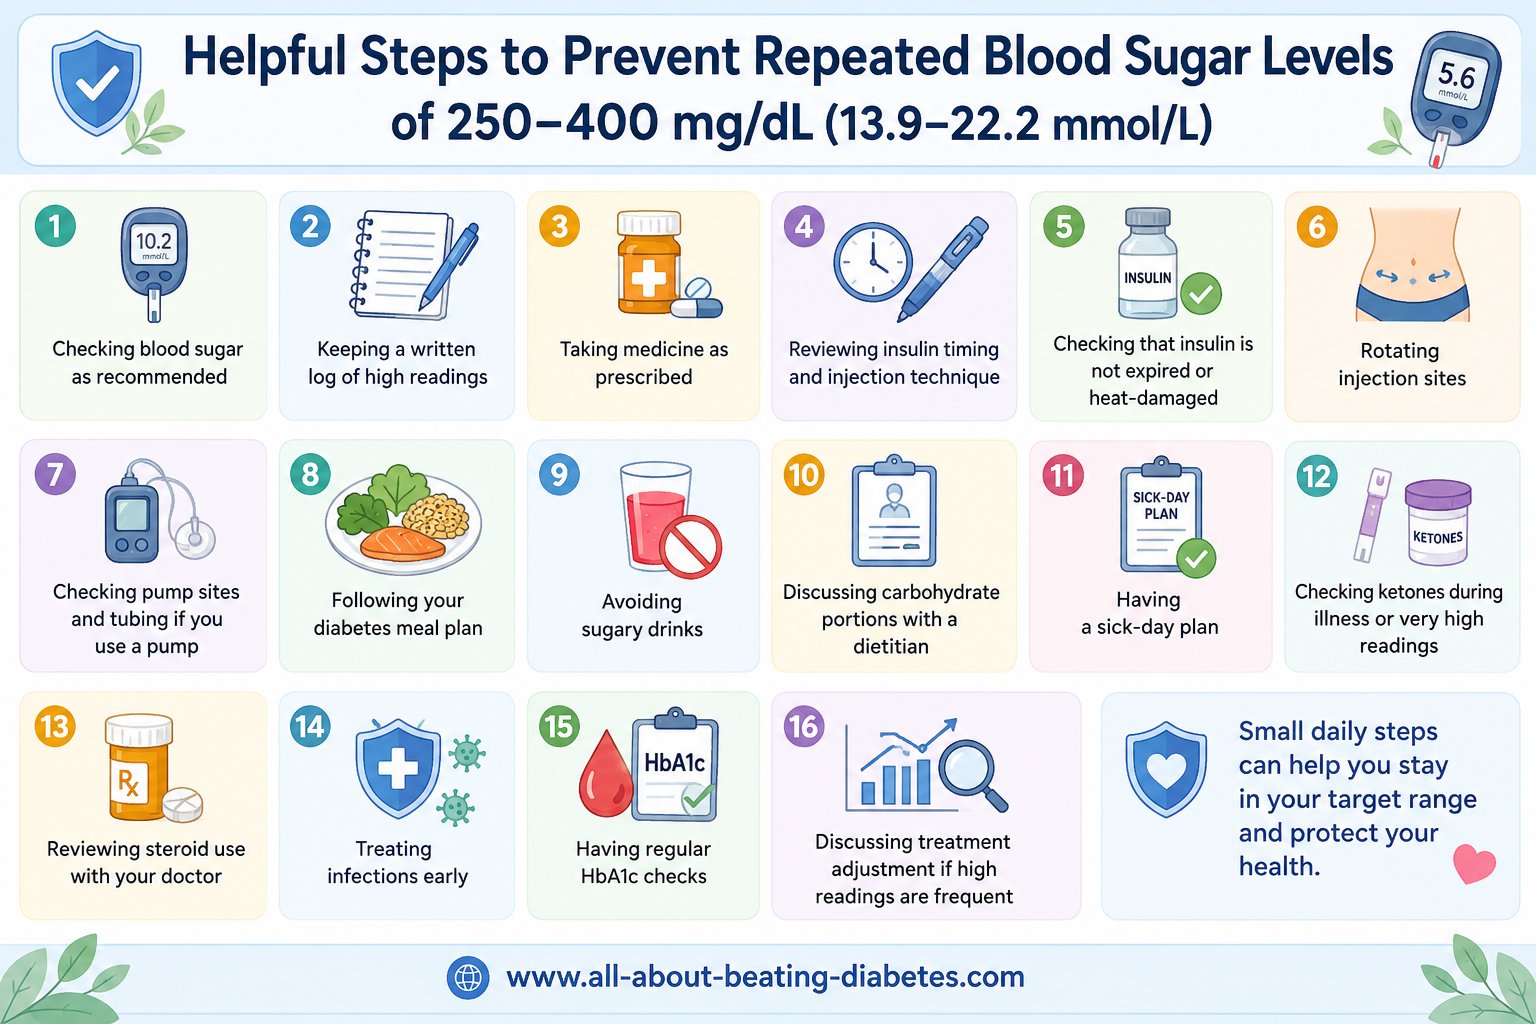
Practical Prevention Measures
- Take prescribed diabetes medicine consistently.
- Check glucose at the times recommended by your clinician.
- Keep a written log of readings and patterns.
- Discuss carbohydrate intake and meal timing.
- Maintain regular fluid intake when medically appropriate.
- Review insulin delivery supplies and techniques.
- Keep a personalized sick-day plan available.
- Review recurring high readings with your clinician.
- Take medications that affect glucose into account.
- Discuss exercise plans and ketone precautions.
- Attend scheduled diabetes follow-up visits.
One high reading is useful information. Repeated readings may indicate that your treatment plan needs reassessment.
HbA1c provides additional information about average glucose over the preceding two to three months. Use our HbA1c to Average Glucose Calculator.
What Should You Write Down Before Calling Your Doctor?
Having the following information available can help the clinician assess your situation.
- All recent glucose readings and their times.
- Whether readings were fasting, after eating or at bedtime.
- Food and drinks consumed recently.
- Diabetes medicines, doses and administration times.
- Any missed medication or insulin.
- Insulin type, dose and time of the last injection.
- Ketone results, if available.
- Symptoms such as thirst, nausea, vomiting or breathing changes.
- Recent illnesses, infection or fever.
- New medicines, particularly steroids.
- Pregnancy status, when relevant.
- Use of an insulin pump or CGM and possible device problems.
- Any treatment you have already taken for the high reading.
You can use our Blood Sugar Log Sheet to organize this information.
Most Asked Questions About Blood Sugar 250–400 mg/dL
Is 250 mg/dL blood sugar dangerous?
It is significantly elevated and needs attention. The urgency depends on symptoms, ketones, illness and how the reading responds to your prescribed plan.
What does a sugar level of 250 mean?
It means your glucose is above typical diabetes treatment targets. It may occur with missed medicine, infection, recent meals or other causes. It does not identify your diabetes type.
Is 300 mg/dL blood sugar an emergency?
It can become an emergency, particularly when persistent or associated with DKA symptoms, dehydration or significant ketones. Seek prompt medical guidance and emergency care for serious symptoms.
Is 400 mg/dL blood sugar dangerous?
Yes. A confirmed reading around 400 mg/dL warrants urgent medical assessment, especially if it remains high or you feel unwell.
Can glucose reach 400 without symptoms?
Yes. Some people have very high glucose without obvious symptoms. Lack of symptoms does not make a persistent reading safe.
Should I exercise if blood sugar is 250–400 mg/dL?
Do not exercise when ketones are present, DKA is suspected, or you are dehydrated or unwell. Follow your clinician's exercise precautions.
Should I drink water when blood sugar is high?
If you can drink safely and do not have fluid restrictions, water may help prevent dehydration. If you cannot keep fluids down, seek medical assistance.
Can stress raise blood sugar to 250–400 mg/dL?
Illness, stress hormones, pain, poor sleep and infection can contribute to marked hyperglycemia. Repeated high readings still require evaluation.
Can steroid medicines raise glucose this high?
Yes. Systemic steroids can substantially increase glucose. Do not stop prescribed steroids on your own; contact the prescribing clinician.
Can type 2 diabetes cause ketoacidosis?
Yes. Although DKA is more common with type 1 diabetes, it can occur with type 2 diabetes, especially during severe illness, insulin deficiency or certain medication use.
Can high glucose occur after eating?
Yes, but 250–400 mg/dL is above usual post-meal management goals for many adults with diabetes. Review the pattern with your diabetes team.
Should I take additional insulin to lower glucose?
Use a correction dose only according to your prescribed plan. Unplanned corrections may cause severe hypoglycemia, particularly when earlier insulin remains active.
What is 250–400 mg/dL in mmol/L?
Approximately 13.9–22.2 mmol/L.
Related Patient Questions
Learn why glucose may remain elevated despite usual treatment.
Understand the importance of symptoms and testing context.
Understand an elevated post-meal result.
Explore high after-meal values.
More Diabetes Tools and Guides
Urgent symptoms and glucose warning levels.
Basal and mealtime insulin education.
Understand meal and correction calculations.
Compare glucose readings at different times.
Convert mmol/L and mg/dL.
Record glucose, food, treatment and symptoms.
Explore longer-term glucose patterns.
Browse diabetes learning tools.
Medical Takeaway
When someone tells me their blood sugar is 250, 300 or 400 mg/dL, I do not judge the number in isolation.
I ask whether they have symptoms, whether they use insulin, whether treatment was missed, whether they are ill, and whether ketones could be present.
A reading of 250 mg/dL deserves attention. A confirmed reading around 400 mg/dL warrants urgent assessment. But ketoacidosis may develop at lower glucose values, which is why symptoms and ketone results matter.
If glucose is repeatedly high, do not consider it normal for you. Record your readings and discuss your treatment plan with your diabetes care team.
Confirm an unexpected result, recognize warning symptoms, follow your prescribed plan and seek medical help when necessary.
Dr. Albana Greca, MD, MMedSc