- Home
- Stress Alcohol Smoking Affect Blood Sugar
- How Does Smoking Affect Diabetes and Blood Sugar
Smoking and Diabetes: How Tobacco Affects Blood Sugar and Complications
If you smoke and have diabetes, I want to begin without blame. Nicotine dependence is not a lack of strength or character. It is a treatable medical condition that changes reward pathways in the brain and produces genuine withdrawal symptoms. Many people need several attempts before they stop permanently.
My role as a doctor is not to shame you. It is to help you understand the added risks, choose a realistic quit plan, manage cravings safely, and protect your blood sugar while your body adjusts. Even if you have smoked for many years or have tried to quit before, another attempt is worthwhile.

How Does Smoking Affect Blood Sugar?
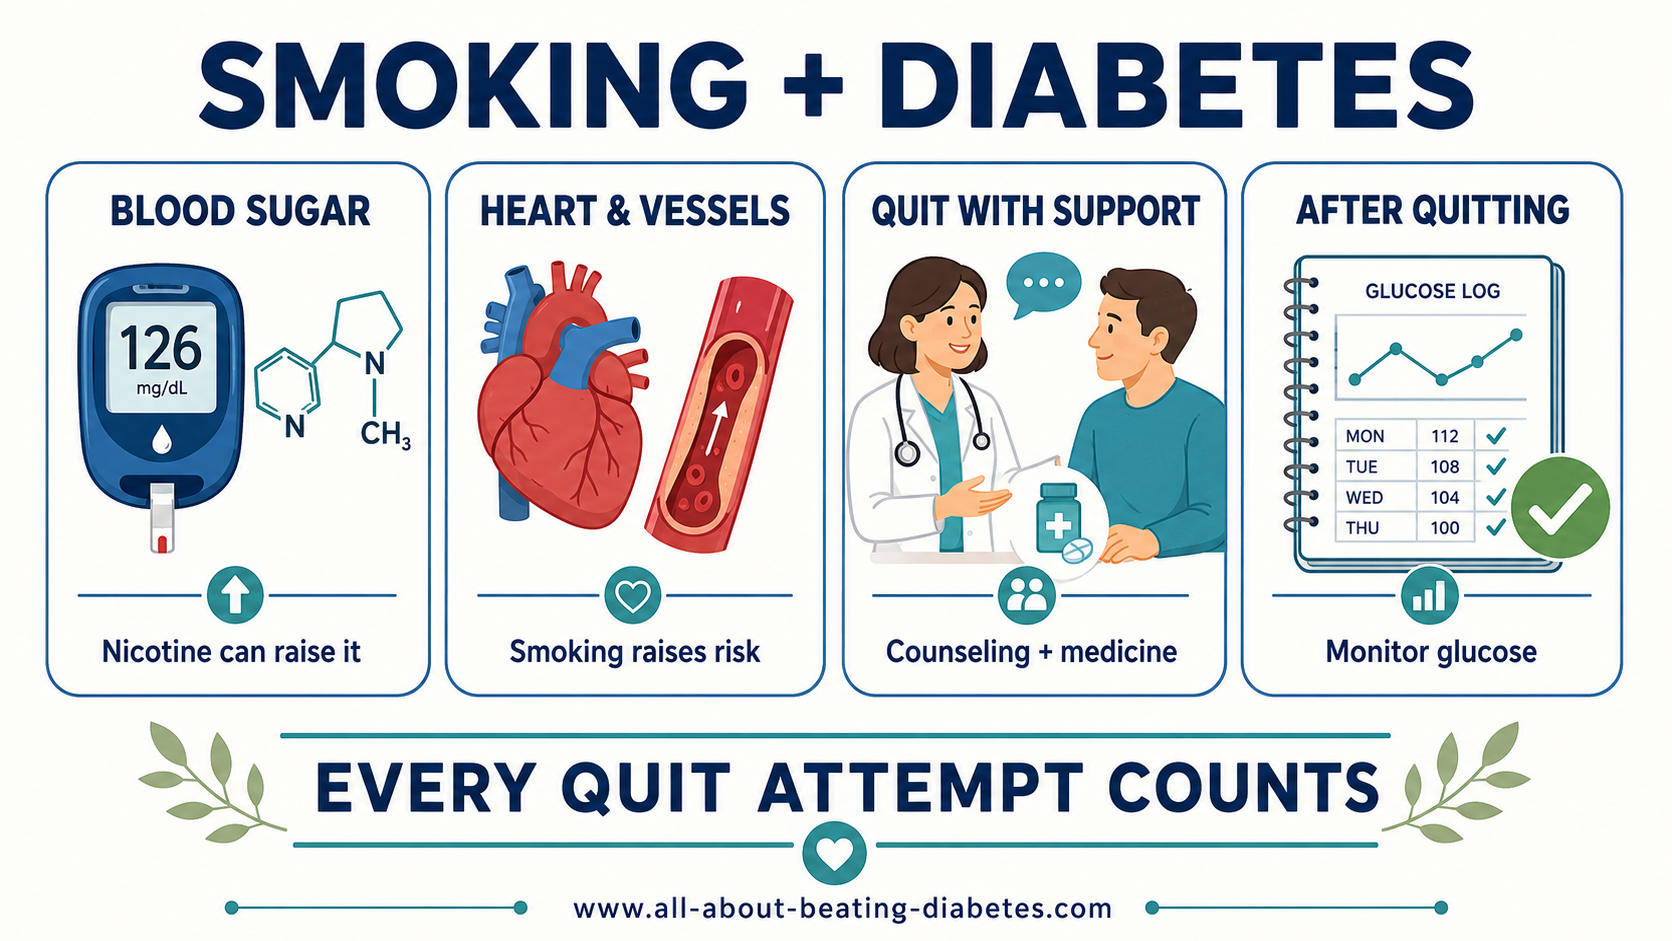
Nicotine can raise blood glucose and make the body less responsive to insulin. Tobacco smoke also promotes inflammation, oxidative stress, and blood-vessel damage. Together, these effects can make glucose more difficult to control.
Some people with diabetes who smoke require more insulin than they otherwise would. That does not mean you should increase insulin by yourself after a cigarette or reduce it automatically when you stop. Look for patterns in your glucose readings and make treatment changes with your clinician.
Smoking also affects routines. A cigarette may replace breakfast, accompany sugary coffee, reduce physical activity, disturb sleep, or become the response to stress. Each of these factors can influence glucose independently. My guide to how lifestyle affects blood sugar explains these connections in more detail.
Can Smoking Cause Type 2 Diabetes?
Smoking is a recognized modifiable risk factor for type 2 diabetes. According to the CDC, people who smoke have a 30%–40% higher risk of developing type 2 diabetes than people who do not smoke, and the risk rises with heavier smoking.
Nicotine, inflammation, increased abdominal fat, and impaired insulin action may all contribute. Smoking is not the only cause of type 2 diabetes—genetics, age, body composition, activity, sleep, medicines, and other health conditions also matter—but removing tobacco can lower an important preventable risk.
Why Are Smoking and Diabetes Especially Harmful Together?
Diabetes and tobacco smoke both damage blood vessels. When they occur together, their effects are not limited to glucose numbers; they increase the burden on nearly every organ supplied by large or small blood vessels.
| Area affected | How smoking adds risk when you have diabetes | What helps |
|---|---|---|
| Heart and brain | Smoking promotes artery narrowing, inflammation, clot formation, higher triglycerides, and lower HDL cholesterol, adding to the cardiovascular risk of diabetes. | Quit tobacco; manage glucose, blood pressure, cholesterol, activity, and prescribed medicines. |
| Legs and feet | Reduced circulation and slower healing increase the danger from unnoticed injuries, infection, ulcers, and amputation. | Inspect feet daily and seek prompt care for any wound, color change, heat, swelling, or drainage. |
| Kidneys | Smoking adds vascular stress and is associated with greater kidney-disease risk and progression. | Check blood pressure, kidney function, and urine albumin as advised. |
| Eyes | Tobacco exposure and diabetes both threaten small blood vessels and vision. | Attend regular dilated eye examinations and report sudden visual changes urgently. |
| Nerves | Poor circulation and vascular injury may worsen neuropathy risk, pain, numbness, and loss of protective sensation. | Manage glucose and vascular risks and have regular foot and nerve assessments. |
| Sexual health | Blood-vessel damage can contribute to erectile dysfunction and other sexual-health problems. | Discuss symptoms openly; effective treatments and cardiovascular evaluation are available. |
Learn more about short- and long-term diabetes complications, diabetic foot ulcers, diabetic kidney disease, and diabetic peripheral neuropathy.
What Happens After You Quit Smoking?
Your body starts recovering soon after the last cigarette. The exact timeline varies, especially when heart, lung, or vascular disease is already present, but the direction is positive at every age.
| Time after quitting | Typical health change |
|---|---|
| Within minutes | Heart rate begins to fall. |
| Within 24 hours | Nicotine in the blood falls to zero. |
| Within several days | Carbon monoxide falls to the level of someone who does not smoke. |
| Within 1–12 months | Coughing and shortness of breath generally decrease. |
| Within 1–2 years | The risk of heart attack falls sharply compared with continuing to smoke. |
| Over subsequent years | Risks of coronary heart disease, stroke, and several cancers continue to fall. |
For people with diabetes, glucose may also become easier to manage after quitting. Continue checking it because insulin or other medication requirements may change.
A Practical Quit Plan for People With Diabetes
- Choose a quit date. Pick a date within the next few weeks rather than waiting for a perfect, stress-free time.
- Tell your diabetes team. Ask how often to check glucose and whether any of your medicines require closer review after quitting.
- Select evidence-based support. Counseling plus an approved quit-smoking medicine generally provides the best chance of success.
- Remove triggers. Clear cigarettes, ashtrays, and lighters from your home and car. Plan a different response for coffee, meals, driving, stress, and social situations.
- Prepare for a lapse. One cigarette does not erase your progress. Stop again, identify the trigger, and adjust the plan instead of abandoning it.
Which Medicines Can Help You Stop Smoking?
Seven quit-smoking medicines are approved by the U.S. FDA for adults who smoke cigarettes. Availability differs by country. The right option depends on previous attempts, how much you smoke, kidney function, heart history, seizure risk, mental health, pregnancy, breastfeeding, medicines, and personal preference.
| Option | How it helps | Important considerations |
|---|---|---|
| Nicotine patch | Provides steady nicotine to reduce withdrawal without exposing you to cigarette smoke. | A clinician or pharmacist can help select a suitable strength. Vivid dreams or skin irritation may occur. |
| Nicotine gum or lozenge | Acts more quickly for sudden cravings. | Correct technique matters. These may be combined with a patch for stronger craving control. |
| Nicotine inhaler or nasal spray | Prescription, faster-acting nicotine replacement options. | May irritate the mouth, throat, or nose. Availability varies. |
| Varenicline | Reduces cravings and makes smoking less rewarding. | Prescription required. Nausea, sleep changes, or vivid dreams may occur; kidney function may affect prescribing. |
| Bupropion SR | Reduces withdrawal and cravings without nicotine. | Prescription required. It is unsuitable for some people, including those with certain seizure or eating-disorder histories. |
Nicotine replacement contains nicotine, so it is not completely risk-free. However, it avoids carbon monoxide and the many toxic chemicals produced by burning tobacco. For most adults who smoke, approved cessation treatment is much safer than continuing to smoke. Pregnancy, breastfeeding, recent serious heart problems, or complex medical conditions require individualized advice before using cessation medicine.
WHO guidance also recognizes cytisine as an effective cessation treatment where it is approved and available. Do not buy unregulated products online; discuss locally authorized options with your doctor or pharmacist.
How Should I Monitor Blood Sugar After Quitting?
CDC guidance notes that blood sugar may fall after smoking cessation. This can be a welcome change, but it deserves attention if you use insulin, a sulfonylurea, or another medicine that can cause hypoglycemia.
- Check glucose at the frequency recommended by your care team, especially during the first weeks.
- Record the time of cravings, meals, nicotine-replacement use, activity, and glucose readings.
- Keep a fast-acting carbohydrate treatment available if you are at risk of low glucose.
- Do not reduce insulin or tablets only because you have stopped smoking; adjust them with professional guidance.
- Contact your clinician if readings repeatedly fall below your target, rise unexpectedly, or become difficult to predict.
Use the blood sugar level chart as general education, but continue following your personal targets.
What Should I Expect From Nicotine Withdrawal?
Cravings, irritability, restlessness, anxiety, low mood, poor concentration, sleep changes, and increased appetite are common after stopping nicotine. Symptoms are often strongest early and usually improve with time. They are evidence of nicotine dependence—not evidence that you cannot quit.
When a craving begins, try the four Ds:
- Delay: wait several minutes before acting.
- Deep breathe: slow your breathing and relax your shoulders.
- Drink water: keep your hands and mouth occupied without added sugar.
- Do something different: walk briefly, call someone, brush your teeth, or leave the trigger situation.
If anxiety or depression becomes severe, persists, or includes thoughts of self-harm, seek professional or emergency mental-health support immediately. Quitting can affect mood whether or not medicine is used.
What If I Gain Weight After Quitting?
Some people gain weight because appetite and taste improve, metabolism changes slightly, or food replaces the hand-to-mouth habit of smoking. This concern is understandable, especially when weight affects type 2 diabetes.
Do not respond with a crash diet during the most difficult stage of withdrawal. Instead, use regular balanced meals, water, higher-fiber foods, planned lower-carbohydrate snacks, and safe daily activity. A short walk after meals can help both cravings and post-meal glucose. My pages on diabetes and weight gain and diabetes and exercise provide practical support.
A modest weight change does not cancel the major cardiovascular, vascular, respiratory, and cancer-related benefits of quitting. Once tobacco abstinence is more stable, your care team can help you pursue weight goals without undermining the quit attempt.
Are Vaping or Heated-Tobacco Products Safer for Diabetes?
No tobacco or nicotine product should be considered harmless. E-cigarette aerosol generally contains fewer toxic chemicals than cigarette smoke, but it can still expose the user to nicotine and other harmful substances. Long-term health effects remain uncertain, and the FDA has not approved e-cigarettes as quit-smoking medicines.
Using cigarettes and e-cigarettes together is not a safe compromise. Dual use may prolong nicotine dependence and does not provide the protection of completely stopping smoked tobacco. If an adult who smokes has switched completely to vaping, the next goal should be a plan to stop vaping rather than returning to cigarettes.
Does Secondhand Smoke Matter When You Have Diabetes?
Yes. There is no safe level of secondhand-smoke exposure. Even brief exposure can harm blood vessels, while ongoing exposure increases the risk of coronary heart disease and stroke. People with diabetes already have greater cardiovascular risk, making a smoke-free home and car particularly important.
Ask visitors to smoke outside, away from doors and windows. Opening a window, using a fan, or smoking in another room does not eliminate exposure. Read more about passive smoking and type 2 diabetes risk.
Doctor’s Note
My own family has experienced how difficult tobacco dependence can be when diabetes is already present. That experience taught me that criticism does not treat addiction. A patient needs clear information, suitable medication when appropriate, practical support, and the freedom to try again after a setback. If you smoke, I do not want you to wait until a complication frightens you. Tell your doctor honestly what you use and ask for a treatment plan. Quitting is one of the strongest steps you can take to protect your heart, kidneys, eyes, nerves, and feet.
Frequently Asked Questions
1. Does smoking raise blood sugar immediately?
Nicotine can raise blood glucose and interfere with insulin action, but the size and timing of the effect vary. Do not adjust diabetes medicine in response to a single cigarette or glucose reading. Review repeated patterns with your clinician.
2. Can smoking cause type 2 diabetes?
Smoking is a causal and modifiable risk factor. The CDC reports that people who smoke have a 30%–40% higher risk of type 2 diabetes than people who do not smoke. It is one contributor among several genetic, metabolic, and lifestyle factors.
3. Will my blood sugar improve after I quit?
It may become easier to manage, and glucose can fall after quitting. Monitor more closely during the transition, particularly if you use insulin or medicine that can cause hypoglycemia. Do not change doses without guidance.
4. Is nicotine replacement safe for people with diabetes?
For most adults who smoke, approved nicotine replacement is much safer than continued cigarette smoking because it avoids combustion toxins. It still contains nicotine and should be selected with a clinician or pharmacist when you have pregnancy, recent serious heart disease, or other complex conditions.
5. What is the best medicine to help me quit?
There is no single best medicine for everyone. Varenicline, bupropion SR, and nicotine-replacement products are evidence-based options. Previous quit attempts, kidney function, seizure risk, mental health, pregnancy, other medicines, cost, and preference affect the choice.
6. Is it better to quit suddenly or reduce gradually?
Both approaches can lead to quitting, but set a clear final quit date. Gradual reduction should be a structured bridge to complete cessation, not an open-ended substitute for it. Counseling and medicine can support either approach.
7. Is vaping a safe alternative if I have diabetes?
No vaping product is harmless, and e-cigarettes are not FDA-approved cessation medicines. Complete substitution exposes a person to fewer combustion toxins than continuing cigarettes, but the long-term effects remain uncertain and dual use is not protective.
8. What if I relapse and smoke again?
A lapse is not proof of failure. Stop again, identify the trigger, and contact your support person or clinician. Your treatment may need stronger craving control, a different medicine, more counseling, or a new plan for high-risk situations.
Related Questions
Related Resources
References
- American Diabetes Association. Facilitating Positive Health Behaviors and Well-being: Standards of Care in Diabetes—2026.
- Centers for Disease Control and Prevention. Diabetes and Smoking.
- Centers for Disease Control and Prevention. How to Quit Smoking.
- Centers for Disease Control and Prevention. Benefits of Quitting Smoking.
- U.S. Food and Drug Administration. FDA-Approved and FDA-Cleared Cessation Products.
- World Health Organization. Clinical Treatment Guideline for Tobacco Cessation in Adults.
- Centers for Disease Control and Prevention. Health Problems Caused by Secondhand Smoke.
Medical disclaimer: This article is for general education and does not replace individualized medical advice, diagnosis, or treatment. Discuss smoking-cessation medicines and changes in glucose or diabetes treatment with your doctor or pharmacist. Seek urgent care for symptoms of a heart attack, stroke, severe breathing difficulty, severe hypoglycemia, or a diabetes emergency.