- Home
- Diabetes Complications
- Can Type 2 Diabetes Cause Cataracts
Cataracts and Type 2 Diabetes: Symptoms, Risks, and Surgery
Type 2 diabetes can increase the risk of developing cataracts and may cause them to appear at a younger age. A cataract is a clouding of the eye’s natural lens. It usually develops gradually, but diabetes, smoking, steroid medicines, eye injuries, and long-term sun exposure can increase the risk or speed its progression.
Written by: Dr. Albana Greca Sejdini, MD, MMedSc, Family Physician
Medically reviewed by: Dr. Ruden Cakoni, MD, Endocrinologist
Last reviewed: July 2026
Quick Answer
People with diabetes are more likely to develop cataracts and may develop them earlier. Common symptoms include cloudy or blurred vision, glare, halos around lights, faded colors, poor night vision, and frequent changes in an eyeglass prescription. Cataracts are diagnosed during a comprehensive eye examination. Glasses and brighter lighting may help temporarily, but surgery is the only treatment that removes a cataract. People with diabetes can have successful cataract surgery, although diabetic retinopathy and macular edema must be assessed and monitored carefully.
On This Page
What Is a Cataract?
The natural lens sits behind the colored part of the eye, called the iris. It focuses light onto the retina at the back of the eye. A healthy lens is clear. With a cataract, proteins in the lens break down and clump together, making part or all of the lens cloudy.
Light no longer passes through the lens normally, so vision may become hazy, less detailed, and more sensitive to glare. Cataracts can affect one or both eyes, but they do not spread from one eye to the other and are not contagious.
Most cataracts are related to aging. Diabetes is an additional risk factor—it does not mean that every person with type 2 diabetes will develop a cataract.
Why Does Type 2 Diabetes Increase Cataract Risk?
Diabetes can affect the lens through several related processes. When glucose remains high, more glucose enters the lens. Some is converted to sorbitol, which can alter fluid balance and contribute to lens swelling and stress. Long-term hyperglycemia also promotes glycation and oxidative damage to lens proteins. These changes may speed clouding of the lens.
The risk is influenced by age, how long a person has had diabetes, glucose patterns, smoking, steroid exposure, family history, previous eye injury or surgery, and ultraviolet exposure. Better diabetes management may reduce or delay eye complications, but it cannot guarantee that an age-related cataract will never form.
The National Eye Institute identifies diabetes as a cataract risk factor, while the National Institute of Diabetes and Digestive and Kidney Diseases emphasizes controlling glucose, blood pressure, and cholesterol as part of protecting vision.
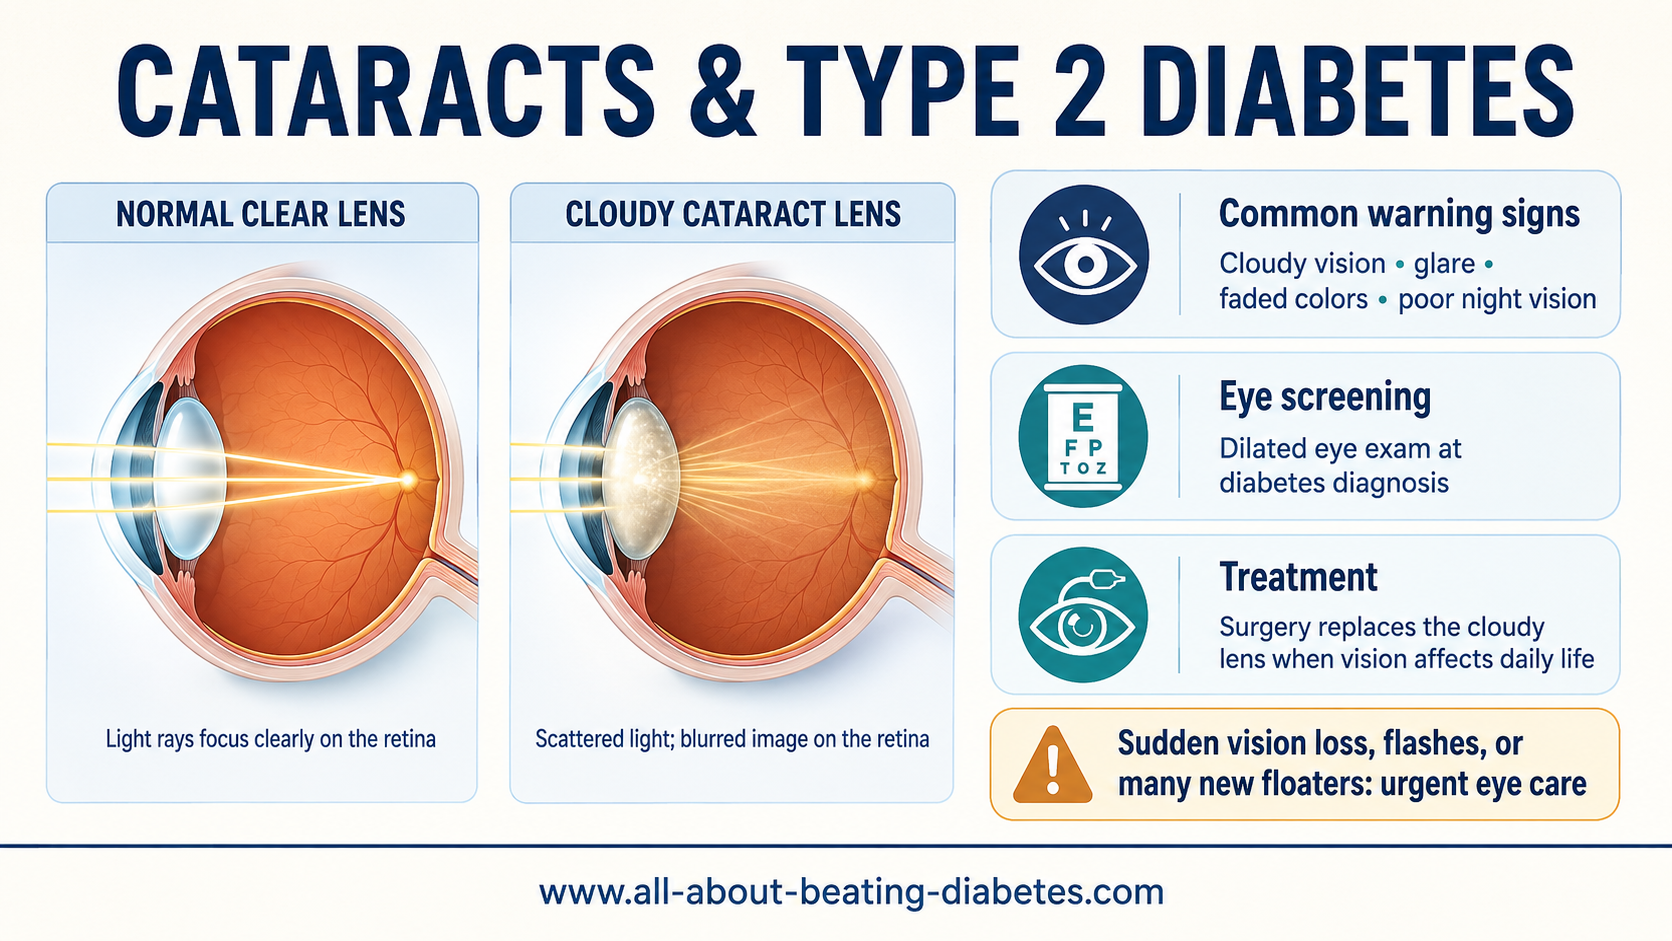

Symptoms of Cataracts in People With Diabetes
Cataracts often develop slowly. There may be no obvious symptoms when the cloudy area is small. As it grows, you may notice:
- Cloudy, blurry, or hazy vision
- Colors looking faded, dull, or yellowed
- Difficulty seeing in dim light or driving at night
- Headlights, lamps, or sunlight appearing uncomfortably bright
- Halos around lights
- Double vision in one eye
- Frequent changes in glasses or contact-lens prescriptions
- Reduced contrast, making steps, faces, or similarly colored objects harder to distinguish
These symptoms are not specific to cataracts. Glucose changes, diabetic retinopathy, diabetic macular edema, glaucoma, dry eye, retinal detachment, medication effects, and other eye conditions can also alter vision. An eye examination is needed to identify the cause.
Urgent Eye Warning
A cataract usually causes gradual, painless vision changes. Seek urgent eye care for sudden vision loss, a curtain or shadow over vision, new flashes of light, many new floaters, severe eye pain, marked redness, eye injury, or sudden distortion. These symptoms may indicate another condition that should not wait for a routine appointment.
Cataract, Temporary Glucose Blur, or Diabetic Retinopathy?
Many patients assume every episode of blurry vision is a cataract. The pattern of symptoms can provide clues, but it cannot replace an eye examination.
| Problem | Part of the Eye | Typical Pattern | Next Step |
|---|---|---|---|
| Cataract | Natural lens | Usually gradual clouding, glare, halos, faded colors, and poor night vision | Comprehensive eye examination; surgery when daily life is affected |
| Temporary glucose-related blur | Fluid balance in focusing tissues | May fluctuate over days or weeks while glucose is high or treatment is changing | Check glucose and contact the diabetes team; persistent or new blur still needs an eye examination |
| Diabetic retinopathy or macular edema | Retinal blood vessels and macula | May have no early symptoms; later blur, distortion, floaters, dark areas, or vision loss | Dilated retinal examination and treatment when indicated |
| Glaucoma | Optic nerve | Often silent until peripheral vision is damaged; sudden painful forms are emergencies | Eye-pressure and optic-nerve assessment |
Read more in our overview of diabetic eye problems and our guide to diabetic retinopathy treatment.
How Are Cataracts Diagnosed?
An ophthalmologist or optometrist can diagnose a cataract during a comprehensive eye examination. Depending on your symptoms and findings, the examination may include:
- Visual-acuity testing to measure how clearly you see at different distances
- Refraction to determine whether a new glasses prescription improves vision
- Slit-lamp examination to examine the cornea, iris, and lens under magnification
- Dilated retinal examination to look for diabetic retinopathy, macular disease, retinal tears, and other causes of vision loss
- Eye-pressure measurement to help assess glaucoma risk
- Optical coherence tomography, or OCT, when the eye specialist needs a detailed image of the macula, especially before surgery or when diabetic macular edema is suspected
A retinal photograph alone is designed mainly to screen the retina and may not provide every part of a full cataract or glaucoma assessment. Ask what type of examination you received and when an in-person dilated examination is appropriate.
How Often Should People With Type 2 Diabetes Have Eye Exams?
The ADA Standards of Care—2026 recommend an initial dilated, comprehensive eye examination when type 2 diabetes is diagnosed. This is important because glucose may have been elevated for years before the diagnosis.
- If one or more annual examinations show no retinopathy and glucose indicators are within the goal range, screening every one to two years may be considered.
- If any diabetic retinopathy is present, examinations should occur at least annually.
- Progressing or sight-threatening disease requires more frequent ophthalmology follow-up.
- Cataract symptoms, pregnancy with preexisting diabetes, new vision changes, or eye surgery may also require a different schedule.
These intervals primarily address diabetic retinopathy screening. Your eye specialist may recommend a different schedule to monitor a cataract, glaucoma, macular edema, or another condition.
How Are Cataracts Treated?
Early or Mild Cataracts
A new glasses prescription, brighter reading lights, reduced glare, magnification, and anti-glare sunglasses may improve function temporarily. These measures do not remove the cataract, but surgery is not automatically required as soon as a cataract is found.
No food, vitamin, herb, eye drop, or supplement has been proven to dissolve an established cataract. Products promoted as a “natural cataract cure” should not delay a proper eye examination.
When Surgery Is Considered
Cataract surgery is usually considered when vision interferes with activities that matter to you, such as reading, driving, working, seeing medication labels, recognizing faces, or moving safely. Surgery may also be recommended when the cloudy lens prevents the eye specialist from examining or treating the retina.
During surgery, the cloudy natural lens is removed and replaced with a clear artificial intraocular lens, or IOL. The National Eye Institute states that surgery is the only way to remove a cataract and that about nine out of ten people see better afterward. The expected improvement depends on the health of the retina, macula, optic nerve, cornea, and other eye structures.
Is Cataract Surgery Safe With Type 2 Diabetes?
Yes. Many people with type 2 diabetes have successful cataract surgery. Diabetes does, however, require careful planning because diabetic retinopathy, diabetic macular edema, infection risk, inflammation, and healing can affect the result.
Before surgery, the ophthalmologist may assess the retina and macula carefully, sometimes using OCT. Active diabetic macular edema or advanced retinopathy may need treatment before, during, or after cataract surgery. A 2024 systematic review found evidence of increased diabetic-retinopathy progression after surgery, supporting close retinal follow-up during the following year.
Before Surgery
- Tell the eye surgeon about all diabetes medicines, insulin, blood thinners, steroid medicines, allergies, and previous eye treatments.
- Ask how to take diabetes medicine and what to eat or drink on the day of surgery. Do not guess or skip medicine without instructions.
- Share recent glucose patterns and HbA1c results. There is no single HbA1c cutoff that applies to every patient or surgical center.
- Ask whether diabetic retinopathy or macular edema is present and whether it should be treated first.
- Discuss the most suitable IOL. Some premium lenses may be less suitable when retinal disease, contrast loss, or future retinal treatment is a concern.
On the Day of Surgery
The surgical team should provide individualized instructions about fasting and medication. Glucose may need checking before and after the procedure. Very high or very low glucose, an active infection, or another acute medical problem may require adjustment or postponement for safety.
Do not try to lower glucose rapidly by taking extra insulin unless you have been given a specific correction plan. Both severe hyperglycemia and hypoglycemia can be dangerous around surgery.
Care and Warning Signs After Cataract Surgery
Use prescribed eye drops exactly as directed, protect the eye, keep follow-up visits, and follow restrictions on rubbing the eye, bending, lifting, swimming, and driving. Recovery instructions vary according to the operation and your eye health.
Contact the eye surgeon immediately for:
- New or worsening vision loss
- Severe or increasing eye pain
- Marked redness or discharge
- Flashes of light, a sudden increase in floaters, or a curtain over vision
- Increasing distortion or a dark area in central vision
- Nausea or vomiting with eye pain
These symptoms can indicate infection, retinal detachment, high eye pressure, macular edema, or another complication. They should not wait for the next scheduled visit.
Months or years after surgery, some people develop clouding behind the artificial lens, called posterior capsule opacification or “secondary cataract.” It is not the original cataract growing back. It can usually be treated with a short laser procedure.
Can Cataracts Be Prevented?
No strategy can guarantee prevention because aging and genetics remain important. These steps may help protect overall eye health and reduce avoidable risk:
- Work with your diabetes team to manage glucose safely and avoid prolonged hyperglycemia.
- Manage blood pressure and cholesterol.
- Do not smoke; ask for support to quit if needed.
- Wear sunglasses that block UVA and UVB and use a brimmed hat in strong sunlight.
- Use protective eyewear during work, sports, or activities that could injure the eye.
- Use steroid tablets, injections, inhalers, creams, and eye drops only as prescribed; do not stop necessary steroids abruptly.
- Attend recommended dilated eye examinations even when vision seems normal.
- Choose a balanced eating pattern rather than relying on antioxidant supplements advertised as cataract cures.
Doctor’s Note
When a patient with type 2 diabetes reports blurry vision, I do not assume the cause is a cataract. I consider temporary glucose-related blur, diabetic retinopathy, macular edema, glaucoma, medication effects, and other eye conditions. A cataract is often treatable, but the best surgical result depends on understanding the health of the whole eye before the operation.
Most Asked Questions
Can type 2 diabetes cause cataracts?
Diabetes is an important cataract risk factor. It can contribute to cataracts developing earlier, but aging and other risk factors also matter.
Can lowering blood sugar reverse a cataract?
No. Improving glucose may clear temporary glucose-related blur, but it does not dissolve a cataract that has already formed. Surgery is the only treatment that removes the cloudy lens.
What blood sugar or HbA1c is required before cataract surgery?
There is no universal number suitable for every patient or surgical center. The surgeon and diabetes clinician consider glucose stability, hypoglycemia risk, infection, symptoms, the urgency of surgery, and other medical conditions. Follow their specific medication and fasting instructions.
Can cataracts come back after surgery?
The removed natural lens does not grow back. Posterior capsule opacification can later make vision cloudy, but it is different from a recurrent cataract and is usually treated with laser.
Will cataract surgery also treat diabetic retinopathy?
No. Cataract surgery replaces the cloudy lens. Diabetic retinopathy and macular edema affect the retina and may require injections, laser treatment, or other retinal care.
Related Questions
- Why Do I Have Blurry Vision With Type 2 Diabetes?
- Can Diabetes Cause Eye Problems, Headache, and Nausea?
- How Can I Reduce the Risk of Diabetes Complications?
Related Resources
- Diabetic Eye Problems: Symptoms and Screening
- Diabetic Retinopathy Treatment Options
- Diabetes Complications and Prevention
- Type 2 Diabetes: Symptoms, Tests, and Treatment
References
- American Diabetes Association Professional Practice Committee. Retinopathy, Neuropathy, and Foot Care: Standards of Care in Diabetes—2026.
- National Eye Institute. Cataracts.
- National Eye Institute. Causes of Cataracts.
- National Eye Institute. Cataract Surgery.
- National Institute of Diabetes and Digestive and Kidney Diseases. Diabetic Eye Disease.
- Incidence and Progression of Diabetic Retinopathy After Cataract Surgery: A Systematic Review and Meta-Analysis.
Medical Disclaimer: Educational only—not personal medical advice. Do not diagnose the cause of vision changes or change diabetes medicine, eye drops, or surgery plans without guidance from your doctor or qualified eye-care professional.