A low glycemic load diet is not a list of “good” and “bad” carbohydrates. It is a practical way to consider both carbohydrate quality and the amount you eat. Used alongside a balanced plate, carbohydrate awareness, and your personal glucose readings, it can help you make calmer, more sustainable meal choices.

What Do Glycemic Index and Glycemic Load Mean?
Glycemic index (GI) ranks carbohydrate-containing foods by their average blood glucose response under standardized testing conditions. On the glucose scale, a GI of 55 or less is low, 56–69 is medium, and 70 or more is high. GI does not measure how much sugar a food contains, and it does not consider your usual portion.
Glycemic load (GL) adds the amount of available carbohydrate in the serving. In simple terms, GI describes the tested carbohydrate’s relative response, while GL brings portion size into the estimate.
If you want the broader background first, read my guide to carbohydrates, GI, and blood sugar.
How Do I Calculate Glycemic Load?
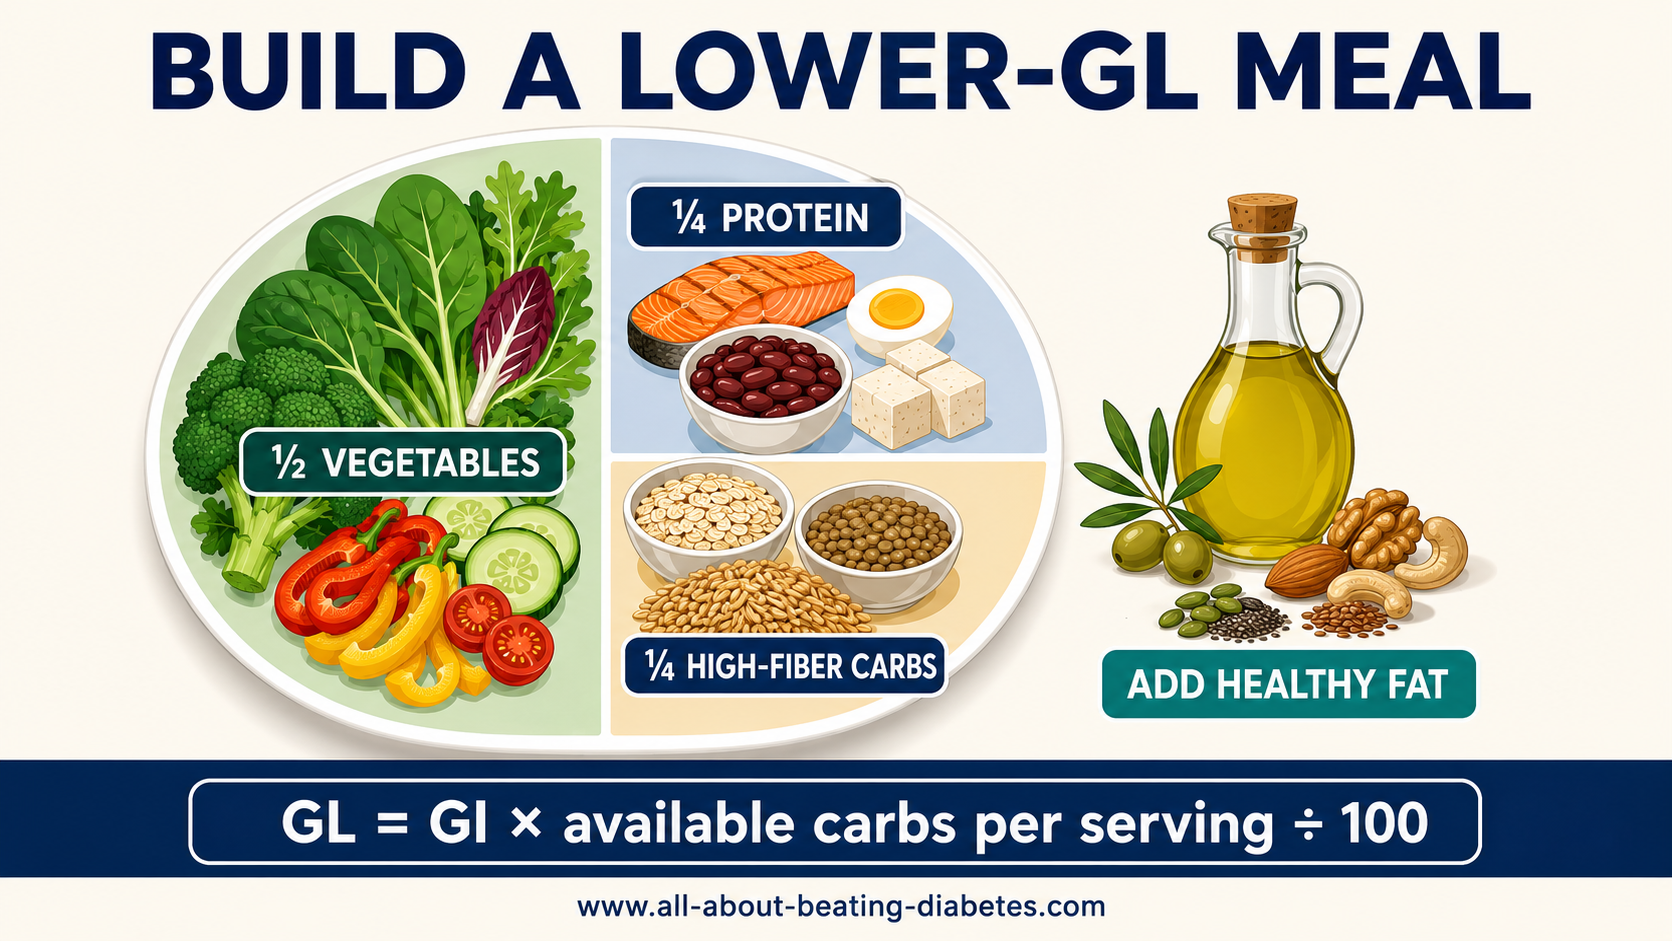
Worked example: If a food has a tested GI of 50 and your serving contains 20 grams of available carbohydrate, its calculated GL is 50 × 20 ÷ 100 = 10.
Use a GI value for the closest tested food, brand, variety, and preparation method. Use the available carbohydrate in the portion you will actually eat—not automatically the amount in 100 grams of food. Food-label conventions differ by country, so be clear about whether fiber is already excluded from the carbohydrate figure.
Reducing a portion lowers its calculated GL when the GI stays the same. However, it is not accurate to promise that eating half a portion will produce a glucose curve exactly half as high. Your response also depends on the rest of the meal, activity, medications, sleep, stress, illness, and your own physiology.
For serving examples, see the glycemic load chart. Remember that breads, cereals, rice, and potatoes can vary widely by variety and processing—even when the label says “whole grain.”
Can a Low Glycemic Load Diet Help Diabetes?
It may help, but the expected benefit is modest and it should support—not replace—your overall treatment plan. A 2021 systematic review of 29 randomized trial comparisons involving 1,617 people with type 1 or type 2 diabetes found that lower-GI/GL dietary patterns reduced HbA1c by an average of about 0.31 percentage points compared with higher-GI/GL control diets. Small improvements were also reported in several cardiometabolic measures.
The American Diabetes Association’s 2026 Standards emphasize individualized meal plans, nutrient quality, total calories, and metabolic goals. They encourage non-starchy vegetables, whole fruits, legumes, lean proteins, whole grains, nuts, seeds, and low-fat dairy or suitable alternatives while limiting sugary drinks, sweets, refined grains, and highly processed foods.
For weight management, a low-GL label alone is not enough. Calories, food quality, portions, activity, medicines, sleep, and long-term consistency all matter. A 2022 review found that lower-GI/GL diets were not clearly superior for weight loss across all adults with excess weight, although a small benefit appeared in the subgroup with obesity.
How to Plan a Low Glycemic Load Diet in Five Steps
- Start with non-starchy vegetables. Fill about half a 9-inch plate with vegetables such as leafy greens, broccoli, cauliflower, peppers, green beans, mushrooms, or tomatoes.
- Add a protein source. Use about one quarter of the plate for fish, chicken, eggs, tofu, unsweetened yogurt, beans, or lentils. Beans and lentils provide both carbohydrate and protein, so their portion may span both sections.
- Choose one main carbohydrate portion. Fill about one quarter with intact or minimally processed grains, legumes, starchy vegetables, fruit, or unsweetened dairy. Start with the portion advised in your meal plan.
- Add a small amount of unsaturated fat. Nuts, seeds, avocado, or olive oil can support meal satisfaction. They still contain calories, so more is not automatically better.
- Check your personal response. If you monitor glucose, compare similar meals and portions. Record the food, amount, timing, activity, and medication so you can discuss useful patterns with your healthcare team.
The diabetes plate method is a good starting point when you do not want to calculate every meal. If you use insulin or need tighter carbohydrate consistency, combine the plate method with your prescribed carbohydrate plan.
Lower-GL Choices and Practical Swaps
Exact GI and GL values depend on the tested product and serving. The table below is therefore a decision guide—not a promise that every version of a food has the same number.
| Food group | Choose more often | Watch the portion or frequency | Simple strategy |
|---|---|---|---|
| Vegetables | Leafy greens, broccoli, cauliflower, peppers, green beans | Large portions of potatoes, fries, mashed potato | Make non-starchy vegetables half the plate |
| Legumes | Lentils, chickpeas, kidney beans, split peas | Sweetened canned bean dishes | Replace part of the rice or pasta with legumes |
| Grains | Barley, steel-cut or rolled oats, quinoa, intact grains | Large bowls of refined cereal, instant rice, white bread | Choose less processed forms and measure the serving |
| Fruit | Whole apples, pears, citrus, berries | Juice, dried fruit, oversized fruit portions | Choose whole fruit and pair it with yogurt or nuts |
| Dairy or alternatives | Plain yogurt, milk, unsweetened fortified alternatives | Sweetened yogurt, flavored milk, sugary drinks | Check both total carbohydrate and added sugar |
| Snacks | Nuts, seeds, vegetables with hummus, fruit with protein | Cookies, candy, chips, sweet drinks | Pre-portion snacks instead of eating from the package |
Do not assume that “brown,” “whole-grain,” or “natural” always means low GI. The 2021 international GI tables found wide variation among breads, breakfast cereals, and rice products because varieties and manufacturing methods differ. For more examples, review my glycemic index food guide and low-GI fruit guide.
One-Day Lower-GL Sample Menu
This example shows the structure of a balanced day; it is not a calorie prescription and does not provide insulin doses. Adjust portions, foods, and timing with your dietitian or diabetes care team.
Water or an unsweetened drink is the simplest beverage choice. Snacks are not mandatory; whether you need one depends on hunger, activity, medicines, glucose patterns, and your individualized plan.
Why GI and GL Are Guides, Not Perfect Predictions
- Values vary: variety, ripeness, processing, cooking, cooling, and storage can change a food’s response.
- Mixed meals are different: GI tests usually evaluate a food under controlled conditions, while real meals contain protein, fat, fiber, acids, and several carbohydrates.
- People respond differently: glucose changes can vary with diabetes type, insulin sensitivity, medications, activity, stress, sleep, and illness.
- Low GL does not always mean nutritious: a highly processed food can have a modest GL yet still be high in saturated fat, sodium, or calories.
- High GI does not mean forbidden: a nutritious higher-GI food may still fit in a smaller portion within a balanced meal.
Use GI and GL to make comparisons, then let your glucose data, nutrition needs, food preferences, and clinical plan guide the final decision.
Diabetes Medication and Hypoglycemia Safety
Continue counting carbohydrate if that is part of your insulin plan. GL cannot tell you the correct mealtime insulin dose. The ADA recommends tailoring education about carbohydrate, fat, and protein to the individual’s insulin plan, and keeping carbohydrate timing and amount consistent when using fixed insulin doses.
If your glucose falls below your personal target or you develop symptoms of hypoglycemia, follow your prescribed low-blood-sugar treatment plan. A low-GL food is generally not the right first treatment for an acute low because it may not raise glucose quickly enough.
Frequently Asked Questions
What is the difference between a low-GI diet and a low-GL diet?
A low-GI diet emphasizes foods that produce a slower average glucose response in standardized testing. A low-GL diet considers both GI and the available carbohydrate in the portion. In practice, both approaches should also consider overall nutrition quality and the full meal.
Is glycemic load more useful than glycemic index?
GL can be more practical because it includes portion size, but neither number is perfect. GI helps compare carbohydrate quality; GL adds the carbohydrate dose. Your personal glucose readings and treatment plan remain more important than either number alone.
What is considered a low glycemic load?
A calculated GL of 10 or less per serving is generally called low, 11–19 medium, and 20 or more high. These cutoffs apply to a defined serving, not automatically to an entire meal or day.
Do I need to calculate the GL of every food?
No. Most people can use the plate method, choose minimally processed high-fiber carbohydrates, and watch portions. Calculations may be useful when comparing two similar foods or investigating repeated post-meal glucose patterns.
Can I eat rice, bread, or potatoes on a low-GL diet?
Often yes. Choose a smaller portion, select a tested lower-GI variety when available, and eat it with non-starchy vegetables and protein. Your glucose response may help you decide which type and portion work best.
Are all whole grains low GI?
No. GI values for whole-grain breads and cereals vary widely because milling, flake size, cooking, and manufacturing affect digestion. Intact or minimally processed grains are often a better starting point, but check a reliable tested value when an exact GI matters.
Will a low glycemic load diet make me lose weight?
Not automatically. It may help some people build more filling meals, but weight change also depends on calories, portions, activity, medicines, sleep, health conditions, and long-term adherence. Evidence does not show a universal weight-loss advantage.
Can a low-GL diet replace diabetes medication?
No. Nutrition can support blood sugar management, but it should not replace prescribed medication. If your readings improve, your clinician can decide whether treatment needs adjustment.
Related Questions and Resources
References
- American Diabetes Association Professional Practice Committee. Facilitating Positive Health Behaviors and Well-being to Improve Health Outcomes: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl 1):S89–S131.
- Chiavaroli L, et al. Effect of low glycaemic index or load dietary patterns on glycaemic control and cardiometabolic risk factors in diabetes: systematic review and meta-analysis of randomized controlled trials. BMJ. 2021;374:n1651.
- Atkinson FS, Brand-Miller JC, Foster-Powell K, et al. International tables of glycemic index and glycemic load values 2021: a systematic review. American Journal of Clinical Nutrition. 2021;114(5):1625–1632.
- Perin L, et al. Low glycaemic index and glycaemic load diets in adults with excess weight: systematic review and meta-analysis of randomized clinical trials. Journal of Human Nutrition and Dietetics. 2022.
- Centers for Disease Control and Prevention. Diabetes Meal Planning. Updated May 2024.
- University of Georgia Cooperative Extension. Glycemic Index and Glycemic Load. Published May 2025.